
Achilles Tendinopathy / Tendinitis
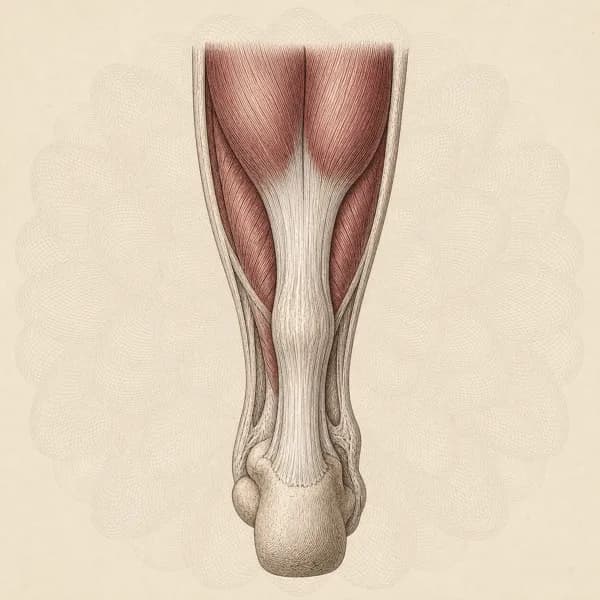
Achilles tendinopathy, often called Achilles tendinitis, is pain and stiffness in the large tendon at the back of the ankle. It can affect the middle of the tendon or the point where it attaches to the heel, and the two are managed differently. It is often stiffest first thing in the morning and at the start of activity.
Key points
- What usually helps
- Exercise that loads the tendon, such as heel drops and slow, heavy calf work.
- What you can do now
- Start with still calf raise holds. Use the 24-hour rule to set the dose.
- How long it takes
- Gains often build over the first 12 weeks; full recovery can take a year or longer.
- When to see a doctor first
- Some signs need medical care the same day. Check the list before you start treatment.
Symptoms
Does this sound like you?
- Pain and stiffness in the Achilles tendon, the thick cord at the back of the ankle
- Marked stiffness first thing in the morning
- Pain when you start activity that may ease as you warm up
- The tendon is tender to touch and may feel thicker
- Pain with calf raises
Often alongside it
- Calf weakness
- Walking differently to protect the tendon
- Other aches from moving differently to protect the tendon
- Not being able to run as far or as often
- Swelling around tendon
It comes on gradually, and morning stiffness is a main feature. Pain at the start of activity may ease as you warm up, but it is worse afterward.
Before using this comparison, check when these symptoms need a doctor first.
When to see a doctor first
Get seen today
A sudden pop or the feeling of being kicked in the back of the ankle, then difficulty pushing off or rising onto the toes
Same-day medical assessment for a possible Achilles tendon rupture; avoid walking on it until it has been checked
New Achilles pain after starting a fluoroquinolone antibiotic (such as ciprofloxacin or levofloxacin)
Contact the prescribing doctor or a pharmacist the same day before continuing exercise
Calf swelling, warmth, or tenderness, especially after a long trip, surgery, or time in a boot
Same-day medical assessment to rule out a blood clot (DVT)
Check with your doctor
Pain in both Achilles tendons or heels with morning back stiffness or swollen joints
See your family doctor to check for an inflammatory arthritis
Treatment
How it is treated
Main approach. Exercise is the core of care and can reduce pain and improve function over several months. It includes slow lowering exercises such as heel drops (eccentric loading) and heavy, slow strength training (heavy slow resistance). For pain in the middle of the tendon (mid-portion), trials show no clear advantage of one loading method over another.
Alongside it. Shockwave therapy may help some persistent cases when combined with an exercise program, though the evidence is mixed.
Managing it over time. Managing training load and building calf strength and ankle mobility may lower the chance of the tendon flaring again.
A typical rehabilitation progression
Three phases, from settling symptoms to returning to full activity.
Recovery from Achilles tendinopathy is usually staged: calm the symptoms first, then rebuild the strength and capacity of the area, then return to your full activities. The phases below show how that can progress.
Phase 1Easing Pain With Still Calf Holds (Weeks 1 to 4)
Bring morning stiffness and first-step pain down to a workable level, and start a steady, predictable load on the tendon without irritating it. Holding a calf raise still (an hold) loads the tendon heavily without the repeated lengthening and shortening that often provokes Achilles pain early on. A pain-monitoring model from Silbernagel's research guides how much to do: symptoms during and after loading can reach up to 5 out of 10, provided they settle within 24 hours and do not rise from week to week.
Example exercises
- Holding a calf raise on both feet, still, at roughly two-thirds of full height (isometric hold), 5 sets of 45 seconds, once a day
- Seated calf raise, held still, 5 sets of 30 to 45 seconds, useful when standing holds flare pain where the tendon attaches to the heel (insertional pain)
- Slow double-leg calf raises on flat ground, 3 sets of 15, 3 seconds up and 3 seconds down
- Seated calf raise with the knee bent to roughly 90 degrees, for the lower calf muscle (soleus), 3 sets of 15
- Running volume reduced by 30 to 50 percent, with steepest uphill or speed work paused
Possible progression milestones
Possible milestones, adapted to the person rather than treated as fixed cut-offs: morning stiffness settling quickly over several days, the still calf holds (isometric holds) feeling comfortable, and no symptom rise 24 hours after loading sessions.
Phase 2Heavy, Slow Strength Work or Heel Drops (Weeks 4 to 12)
Rebuild how much load the tendon can handle. For pain in the middle of the tendon (mid-portion), the choice is between Alfredson's heel-drop program (3 sets of 15 twice a day off a step, with the knee straight and with it bent, seven days a week) and heavy, slow strength training (heavy slow resistance) as tested by Beyer and colleagues in a 2015 trial: 3 sets, 3 times per week, 3 seconds up and 3 seconds down, progressing from a weight you can lift 15 times toward one you can lift only 6 times across the block. Both programs improved outcomes in that trial, with no clear difference between them at 52 weeks. For pain where the tendon attaches to the heel (insertional), the heel stays on flat ground or a slight lift rather than dropping below level, in line with current clinical guidance on limiting pressure of the tendon against the heel bone early in rehabilitation (Silbernagel et al., 2020).
Example exercises
- Pain in the middle of the tendon: Alfredson heel drops off a step, knee straight and knee bent, 3 sets of 15 twice a day
- Alternative: heavy, slow standing calf raise in a Smith machine or with a barbell, 3 sets of 6 to 15 repetitions, 3 times per week with a rest day in between
- Heavy, slow seated calf raise for the lower calf muscle (soleus), 3 sets of 6 to 15 repetitions
- Pain where the tendon meets the heel: calf raises from the floor or a slight lift only, same speed and sets, without letting the heel drop so far that the ankle bends fully up (end-range )
- Running kept up or gradually rebuilt, using the 24-hour rule (symptoms settle within 24 hours) to decide each step
Possible progression milestones
Possible milestones, adapted to the person rather than treated as fixed cut-offs: full-range single-leg calf raises with low pain, a solid set of consecutive single-leg raises on the affected side, and loading sessions tolerated over several weeks without a 24-hour flare.
Phase 3Rebuilding Spring and Returning to Sport (Months 3 to 6+)
Restore the spring-like behaviour (the stretch-shortening cycle) the Achilles needs for running, changing direction and jumping. This follows the later stages of a 2015 return-to-sport framework by Silbernagel and Crossley: move on to hopping and jumping drills () only once heavy strength work is comfortable, and rebuild running and sport volume gradually rather than in a single jump.
Example exercises
- Small, springy hops on both feet (pogo hops) on a soft surface, 3 sets of 20, progressing to firm ground
- Single-leg hops in place, then for distance, then with change of direction
- A-skips (skipping with a high knee drive), bounding (long, springing strides), and controlled accelerations
- Running volume rebuilt in small weekly steps, with hills and speed work reintroduced last
- Sport-specific demands such as cutting for soccer, repeated sprints, or jump-intensive training reintroduced in graded blocks
Possible progression milestones
Possible milestones, adapted to the person rather than treated as fixed cut-offs: scores on an Achilles questionnaire (VISA-A) trending upward when used, single-leg hopping close to the unaffected side, and full training or running volume sustained over several weeks without a 24-hour symptom flare.
What you can do now
- Start with still calf raise holds. Rise onto both toes to about two-thirds of full height and hold still for 45 seconds; do 5 holds once a day. Holding still loads the tendon without the repeated movement that often irritates it early on.If standing holds flare pain where the tendon meets the heel, do them sitting instead, 5 holds of 30 to 45 seconds.
- Use the 24-hour rule to set the dose. Pain during and after exercise or running can reach up to 5 out of 10, as long as it settles within 24 hours and does not creep up from week to week. A flare the morning after is information to adjust the dose, not a sign you have failed.Morning stiffness that lasts noticeably longer than usual after a session is a sign to dial the loading back.
- Cut back running rather than stopping. Complete rest can leave the tendon less able to cope with load, and symptoms often return when running starts again. Reduce your running by 30 to 50 percent, pause steep hills and speed work, and keep running while the 24-hour rule holds.These limits come from one trial program in people with Achilles tendinopathy; they are example limits, not proof that running is safe for every cause of pain. A sudden pop or the feeling of being kicked in the back of the ankle, then trouble pushing off or rising onto your toes, needs a same-day medical assessment; avoid walking on it until it has been checked.
- For heel pain, keep raises on flat ground. When the pain sits where the tendon attaches to the heel (insertional), dropping the heel off a step or stretching hard pinches the tendon against the heel bone. Do your calf raises on flat ground or a slight lift, and avoid aggressive calf stretching early on.
- Pick a routine you will keep up. Consistency usually matters more than intensity, so choose a version of calf raises you will keep doing several times a week for months. Meaningful change usually takes about 3 months of consistent loading.
What I use in clinic
- Heel-drop program (eccentric exercise). Can reduce pain and improve function when done consistently for 12 weeks or more.
- Heavy, slow strength training (heavy slow resistance). In a randomised trial, results showed no clear difference from the heel-drop program at one year, and people attended more of their sessions (Beyer et al., 2015).
Recovery
How long it takes
Recovery is slow and requires patience. Pain and function usually improve gradually over the first 12 weeks of loading, when the gains in these studies tended to level off (Murphy and colleagues, 2018), but full recovery often takes a year or longer. Some people keep mild symptoms while returning to the activities they want.
Many people improve with a well-dosed loading program. A smaller group who still have significant symptoms after at least 6 months of good non-surgical care go on to discuss other options, including surgery, with a physician.
What changes the timeline
- Research has not found a factor that reliably predicts recovery for one person; the studies are few and low quality
- How long symptoms have lasted, and what a scan shows (tendon thickness, or damage in one spot), do not reliably predict outcomes
- Whether the pain is in the middle of the tendon (mid-portion) or where it attaches to the heel (insertional) changes how the exercises are set
- How easily the tendon flares at the start, and how training is managed alongside rehab
- Worry about the tendon and confidence with loading may influence recovery
How I track it. I track how long your morning stiffness lasts, your pain, and how many single-leg heel raises you can do
Similar conditions
Conditions that can feel similar
- Insertional vs Mid-portion Achilles Tendinopathy
- Insertional pain sits right at the heel bone. It often flares when the ankle bends up a long way toward the shin, or with uphill running, because the tendon is pressed against the heel bone (calcaneus). Mid-portion pain sits 2 to 6 cm above the heel, in the soft part of the tendon. The difference matters because insertional cases tolerate less upward ankle bend during exercises, so heel drops below the level of a step are typically avoided early on.
- Partial or Complete Achilles Rupture
- A rupture is usually a sudden event with an audible snap or a sense of being kicked in the back of the ankle, immediate weakness pushing off, and a positive Thompson test, where squeezing the calf does not make the foot point down. Tendinopathy builds over weeks, eases with a warm-up, and keeps push-off strength.
- Retrocalcaneal Bursitis or Haglund's Deformity
- Pain sits at the back of the heel itself rather than in the tendon. A visible bony bump at the upper back edge of the heel bone, pain when both sides of the tendon are squeezed just above the heel (rather than when the tendon itself is pressed), and pain made much worse by the back of a shoe pressing on the heel all point away from the tendon as the main problem.
- Posterior Ankle Impingement
- Pain is deep at the back of the ankle rather than along the tendon. It peaks when the foot is forced into a fully pointed position (forced plantarflexion), such as rising to full height in a calf raise, dancing en pointe, or pushing off in a sprint. Holding a calf raise does not reliably bring it on, while a test that pushes the foot fully into the pointed position does.
- Posterior Tibial Tendinopathy
- Pain and swelling run behind and below the inner ankle bone rather than at the Achilles. The arch often feels tired or flattened, and when you rise onto your toes on one leg the heel does not tip inward as it should. Pushing the foot down against resistance, which classically hurts an Achilles tendinopathy, is often comfortable here, and the reverse is also true.
- Sural Nerve Irritation
- Sharp, burning or tingling pain that follows the outer edge of the Achilles down into the foot, often with a consistent tender spot over the nerve rather than the tendon. Calf raises typically do not bring on the pain; light tapping over the nerve, or stretching it, does.
Questions
What patients ask me most
How long does Achilles tendinopathy take to get better?
Meaningful change usually takes 3 months of consistent loading, and full return to running or jumping often sits in the 6 to 12 month range depending on how long symptoms were present before starting rehab. The Silbernagel and Crossley JOSPT 2015 return-to-sport framework sets expectations around months, not weeks, because the collagen in a tendon rebuilds slowly. Patience is part of the treatment.
Should I stop running with Achilles tendinopathy?
Often no. Complete rest can detrain the tendon, and symptoms often return when running resumes. The Silbernagel pain-monitoring model allows continued running provided pain stays at or below about 5 out of 10 during the run, settles within 24 hours, and does not creep up week over week. If all three hold, running can often continue alongside the rehab. These limits come from one trial program in people with Achilles tendinopathy. These are example monitoring limits, not proof that running is safe for every cause of pain.
Do eccentric heel drops still work, or is heavy slow resistance better?
Both can help. Alfredson's 1998 study of 3 sets of 15 heel drops twice daily for 12 weeks was small, but it shaped how tendon rehab is done. Beyer and colleagues (AJSM 2015) compared heavy, slow strength training (heavy slow resistance) with heel-drop (eccentric) training at 12 and 52 weeks. Both improved, with no statistically significant difference between them; satisfaction tended to be higher with heavy slow resistance at 12 weeks, but that difference was not statistically significant either. I typically pick based on equipment access, schedule, and what the person will actually do three times a week.
Why is my Achilles worst in the morning?
Morning stiffness is a common feature of tendinopathy. During sleep the tendon sits in a shortened, unloaded position, and your first steps put load back through tissue that has not warmed up. Stiffness that eases within several minutes, and a warm-up period where the tendon feels better during activity, are typical. Stiffness that lasts noticeably longer than usual the morning after a session, or builds through the day, can be a sign that loading needs to be dialled back.
What is the difference between insertional and mid-portion Achilles tendinopathy?
Mid-portion pain sits in the soft belly of the tendon 2 to 6 cm above the heel. Insertional pain sits right where the tendon meets the heel bone. The difference matters because an insertional tendon gets pinched against the heel bone when the ankle bends up a long way, so heel drops off a step are typically avoided early on and calf raises on flat ground or a slightly raised surface are used instead. Mid-portion cases tolerate, and often benefit from, heel drops off the edge of a step.
Are cortisone injections a good idea for Achilles tendinopathy?
I do not treat an Achilles injection as a routine first step. Injection into the tendon itself raises particular concern about weakening it, and the technique and the rehabilitation afterwards matter. One placebo-controlled trial in selected adults with long-standing mid-portion pain found more improvement at six months when an ultrasound-guided injection around the tendon was added to exercise, with no severe side effects in that group (Johannsen et al., JAMA Network Open 2022). That trial does not cover insertional pain, partial tears, or every loading program. If an injection is being considered, a sports medicine physician should discuss whether that evidence applies to you and explain the risks. Progressive loading stays at the centre of the plan either way.
When should I worry about an Achilles rupture versus tendinopathy?
A rupture is usually a sudden event, often with a pop or a sensation of being struck in the calf, followed by immediate difficulty pushing off or rising onto the toes. Inability to perform even a small single-leg heel raise, or a positive Thompson test (squeezing the calf while lying face-down fails to move the foot), warrants urgent assessment rather than rehab planning. Tendinopathy, by contrast, builds gradually and preserves most strength.
Does ultrasound or MRI change the treatment plan for Achilles pain?
In most cases, no. Imaging often shows tendon thickening, new small blood vessels (neovascularisation), or changes in one spot, and these match poorly with symptoms and with how recovery goes. Two Achilles tendons that look identical on ultrasound can behave completely differently. I flag it to your family doctor or specialist and refer you for imaging when a partial tear, bursitis, or a bone problem is genuinely possible, not as a routine confirmation of tendinopathy.
The science
The Science of Achilles Tendinopathy / Tendinitis
Achilles is a failed healing response characterized by changes rather than acute inflammation. The condition involves disorganized , increased ground substance, and within the tendon. This represents a chronic overuse injury where the cumulative load on the tendon exceeds its adaptive capacity.
Two distinct types require different treatment approaches: Mid-portion Achilles tendinopathy (MAT) occurs 2 to 6 cm above the heel insertion and is primarily a tensile overload condition. Insertional Achilles tendinopathy (IAT) affects the tendon's attachment to the and involves both tensile and compressive forces, as the tendon can be compressed against the heel bone during movements.
The involves a breakdown in the normal collagen structure, leading to painful, thickened tissue with reduced mechanical properties. Unlike acute inflammation (), this degenerative process (tendinosis) requires specific loading strategies to stimulate proper tissue remodeling rather than anti-inflammatory treatments.
Contributing factors
Achilles typically develops from a combination of training load mismanagement and poor . Your Achilles tendon has to handle forces up to 8-12 times your body weight during activities like running and jumping, making it incredibly sensitive to changes in load. The classic pattern I see is someone who increases their training volume or intensity too quickly, or returns to activity after a break without gradually building up their tendon capacity.
Running mechanics significantly influence Achilles tendon loading. A or midfoot strike pattern generally loads the Achilles more than heel striking, which can be problematic if your tendon isn't adapted to higher loads. (excessive foot flattening) creates a whipping action in the tendon that can contribute to overload, particularly at the insertion point. Tight calf muscles or poor ankle flexibility force your Achilles to work harder during push-off and limit your ability to absorb impact forces effectively.
Footwear and training surface changes can trigger Achilles problems even in experienced athletes. Switching to more minimalist shoes or zero-drop footwear significantly increases the load on your Achilles. Running on hills, particularly uphill running which requires more power, or sudden increases in or jumping activities can overload the tendon. Age compounds these factors because the tendon naturally becomes less elastic and has reduced blood supply, making it more vulnerable to developing the changes characteristic of tendinopathy rather than healing normally from micro-damage.
Research
What the studies show
Heavy heel-drop training for pain in the middle of the Achilles tendon: a review of 7 trials
Across 7 randomised trials, heavy heel-drop training (heavy eccentric calf training) appeared better than letting the condition run its course and than traditional physiotherapy for pain and function, but was not clearly better than other exercise programs, and any difference was unlikely to matter in practice. The authors stress that the trials were small and had design weaknesses, so these estimates remain uncertain.
Supports loading exercise as a first treatment for pain in the middle of the Achilles tendon, while showing that no single loading program is clearly better, so the exercise can be matched to the person.
Murphy MC, Travers MJ, Chivers P, et al. Efficacy of heavy eccentric calf training for treating mid-portion Achilles tendinopathy: a systematic review and meta-analysis. Br J Sports Med. 2019;53(17):1070-1077. PMID: 30636702.
Heavy, slow strength training versus heel drops for Achilles tendinopathy: a randomised trial
In 58 people, heavy, slow strength training and traditional heel-drop (eccentric) exercises both improved outcomes, with no clear difference between them at 52 weeks. Both groups had clear, lasting improvements in Achilles symptoms and function and in pain during activity. The heavy, slow group tended toward greater satisfaction at 12 weeks and did more of their planned training across the program.
Shows that more than one loading program can help, so the choice can be based on what you prefer and will keep doing.
Beyer R, Kongsgaard M, Hougs Kjær B, et al. Heavy slow resistance versus eccentric training as treatment for Achilles tendinopathy: a randomized controlled trial. Am J Sports Med. 2015;43(7):1704-1711. PMID: 26018970.
Related Conditions
Conditions I commonly see alongside, or confused with, this one.
Plantar Fasciitis & Heel Spurs
Both involve posterior chain; Achilles stiffness is major risk factor for plantar fasciitis
Sever's Disease
Both involve Achilles tendon attachment issues, though in different age groups
Shin Splints
Both are common running injuries; Achilles dysfunction can contribute to shin splints
Ankle Sprains
Ankle instability affects Achilles tendon loading and mechanics
Peroneal Tendinopathy
Getting back to it
Physiotherapy for Achilles tendinopathy / tendinitis, built around the activity you want back.
