
Groin Strains
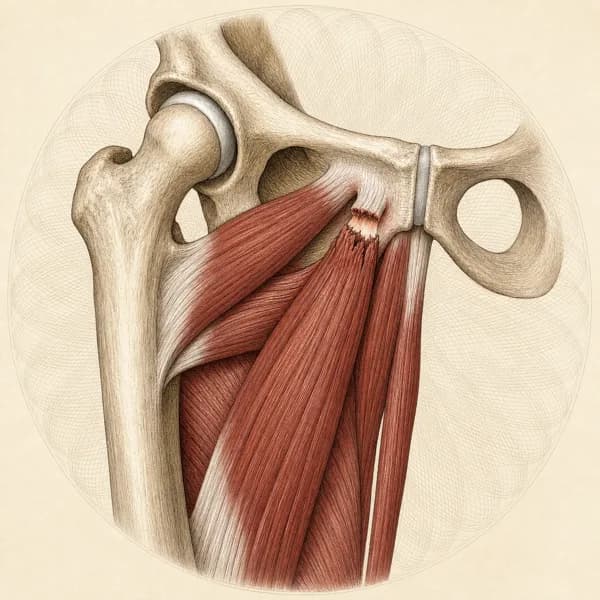
A groin strain usually involves the inner-thigh adductor muscles or their tendons. It can happen during sprinting, kicking or changing direction, with pain when squeezing the legs together or pushing off. Longer-standing groin pain can have several causes, so assessment helps distinguish a strain from problems around the hip, tendons or groin canal.
Key points
- What usually helps
- Active loading started early and strength work built up step by step, rather than long rest.
- What you can do now
- Rest for the first two or three days. Use ice and compression if they help.
- How long it takes
- Small to moderate strains: about 3 weeks to full training. Long-standing groin pain often takes several months.
- When to see a doctor first
- Some signs need emergency care. Check the list before you start treatment.
Symptoms
Does this sound like you?
- Sudden sharp pain in the inner thigh or groin
- Difficulty speeding up or kicking
- Pain when bringing the leg in towards the other leg (adduction)
- Tenderness along the inner thigh muscles (adductors)
- Pain when squeezing your knees together
Often alongside it
- Possible bruising in the inner thigh with larger tears
- Muscle spasm and tensing up to protect the area
- Difficulty walking or running normally
- Pain with coughing or sneezing (in severe cases)
- Stiffness after resting
It starts suddenly during an explosive movement or a kick. Pain gets worse with activities that bring the leg inward or need you to speed up. Morning stiffness eases with gentle movement. Long-standing cases may develop pain that creeps in gradually during or after sport.Book an assessment for groin strains
When to see a doctor first
Go to emergency
A limping child or teenager with sudden hip, thigh or knee pain, who cannot put weight on the leg, whose leg looks deformed, or who has a fever and feels unwell
Go to emergency now
A suspected slipped growth plate at the hip (SCFE)
Do not let the child walk on the leg, and seek emergency assessment today. In a teenager this can show up as a limp with hip, groin, thigh or knee pain, even when they can still walk
A groin lump with sudden severe pain, vomiting, or difficulty passing stool or wind
Go to emergency now. This can be a trapped (strangulated) hernia, which needs emergency assessment
Sudden severe testicular pain
Go to emergency now. Do not treat it as a groin strain
Get seen today
Groin or hip pain in a runner that builds with each run, or pain when hopping on that leg
Possible stress fracture of the hip (femoral neck). Stop running and all impact exercise, keep weight off the leg, and get medical assessment today. If you cannot put weight on the leg or the pain is severe, go to emergency. An early X-ray can look normal
Groin pain with fever, a hot or swollen hip, or you cannot put weight on the leg
Possible infection or fracture. Get medical assessment today, or go to emergency if you feel unwell or cannot bear weight. Infection is possible even without a fever
Check with your doctor
Sudden severe pain with an audible pop and you could not carry on
Possible complete tear, or the tendon pulled off the bone (avulsion). See a doctor within 1 to 2 days to decide whether imaging and a surgical opinion are needed
Extensive bruising spreading down the thigh within 24 hours
Possible high-grade tear. Medical assessment in the next few days
A child or teenager with a new limp that has no clear explanation
Get a prompt medical assessment before starting exercises. A hip problem can be felt only in the groin, thigh or knee
Pain with coughing, sneezing, or bearing down, or a lump in the groin
May be pain from the groin crease area (inguinal-related groin pain) or a hernia rather than a muscle strain. See your family doctor
No improvement after 2 weeks of appropriate rehabilitation
I flag it to your family doctor or a sports medicine physician, who can arrange imaging if it would change the plan
Treatment
How it is treated
Main approach. Strength training that builds up step by step, with a focus on lengthening the muscle under control (eccentric work), and active loading started early can support a faster, longer-lasting return to sport than long rest. Each step up is guided by meeting set checks of what you can do (functional criteria).
Alongside it. For long-standing groin pain from the inner thigh muscles (adductors), active strengthening combined with hands-on treatment (manual therapy) has some supporting evidence, though the quality of that evidence is moderate at best.
Managing it over time. In a trial of male soccer players, a program built on the Copenhagen adduction exercise (a side-lying inner thigh exercise), done three times a week in preseason and once a week in season, lowered the risk of reporting groin problems by 41% (Harøy et al., 2019).
A typical rehabilitation progression
Three phases, from settling symptoms to returning to full activity.
Recovery from groin strains is usually staged: calm the symptoms first, then rebuild the strength and capacity of the area, then return to your full activities. The phases below show how that can progress.
Phase 1Protect, Load Gently and Start Pain-Free Squeeze Holds (Days 1 to 14)
Thorborg's 2023 paper on clinical concepts (Journal of Athletic Training) and the earlier Hölmich program both build inner thigh () rehab on exercise and load management rather than long rest. Pain-free squeezes that do not move the joint ( adduction) within the first few days set the base for the whole program. This phase is about keeping the tissue active while it knits, not resting it completely. The time ranges in these phase titles are examples: the size of the injury and meeting each phase's milestones decide when you move on.
Example exercises
- Lying on your back with knees bent, squeezing a ball between the knees (short-lever squeeze), 5 sets of 20 seconds at less than full effort, twice daily
- Ball squeeze with the legs straight (long-lever squeeze), same dose, once the bent-knee squeeze is comfortable day to day
- Lying on your side, lifting the bottom leg (side-lying hip adduction) through a short pain-free range, 2 sets of 8 to 10
- Stationary bike or a light walk to keep up fitness, if pain-free
- Ice after session if it helps symptoms, compression shorts if tolerated
Possible progression milestones
Straight-leg squeeze hold at moderate effort without pain, walking fully pain-free, and tenderness over the main inner thigh muscle (adductor longus) clearly reduced.
Phase 2Strength Through Range and the Copenhagen Progression (Weeks 2 to 6)
The (a side-lying exercise with the top leg supported on a bench or by a partner) is a central exercise for rebuilding what the inner thigh muscles can handle. In a trial of male soccer players, Harøy and colleagues (2019) found that teams doing it three times a week in preseason and once a week in season had a 41 percent lower risk of players reporting groin problems. The Hölmich program (Lancet 1999) is the older cousin and still the backbone for long-standing cases. Range, load and lengthening () work all progress together.
Example exercises
- Copenhagen adduction exercise, starting with the support at the knee (short lever) and progressing to support at the ankle (long lever), 3 sets of 6 to 10 per side, 2 to 3 sessions per week
- Lying on your side, lifting the bottom leg (side-lying hip adduction) with a light ankle weight, 3 sets of 8 to 12
- Standing, pulling the leg in toward the other leg against a cable or band (hip adduction), 3 sets of 10
- Side lunge with one foot on a sliding disc, focusing on control as the inner thigh lengthens (eccentric control), 3 sets of 6 to 8 per side
- Low-intensity jogging introduced when single-leg hopping is symptom-free
Possible progression milestones
Long-lever Copenhagen adduction for 3 sets of 8 without pain, single-leg hops forward and sideways equal on both sides and pain-free, and straight-line running at sprint pace managed.
Phase 3Sport-Specific Reloading and Return to Play (Weeks 6 to 12 or longer)
The approach from Serner and colleagues (2020), based on meeting set criteria, drives this phase: do not return by the calendar, return by meeting checks for strength, hopping and the demands of your sport. Kicking, changing direction (cutting) and sprinting demand different qualities and are brought in deliberately.
Example exercises
- Accelerations and decelerations at progressing speeds, including change-of-direction drills
- Controlled kicking progression starting with short-range passing, building to long kicks
- Heavy inner thigh exercises against resistance (hip adduction), 4 sets of 6, working toward inner thigh strength that matches the demands of your sport
- Sport-specific intervals and small-sided drills before full training
- Keeping the Copenhagen adduction exercise going twice a week for the long term, for prevention
Possible progression milestones
Strength testing and progressively harder running, cutting or kicking tasks show readiness for the demands of the person's sport, without meaningful symptoms during or after training. A sustainable maintenance plan is in place, with adductor exercises selected for the sport and the person's tolerance.
What you can do now
- Rest for the first two or three days. While it is acutely painful, rest for the first two or three days, then start gentle, pain-free movement. After that point, pain-free loading is better than continued rest.If you felt a pop and could not carry on, or bruising spreads down the thigh within 24 hours, follow the warning signs on this page before you start loading.
- Use ice and compression if they help. Ice for 15 to 20 minutes every 2 to 3 hours for the first 2 days, and after exercise sessions later on if it helps. Compression shorts can be worn if they feel comfortable.Put a towel between the ice and your skin to protect it.
- Start gentle squeeze holds. From around day 3 to 7, lie on your back with your knees bent and squeeze a ball or pillow between them without moving the legs. Hold for 20 seconds, 5 times, twice a day, well below full effort, to keep the inner thigh muscles working while they heal.Stay well below the point where it hurts, and do not progress if the pain increases.
- Keep fit on a bike or walking. A stationary bike or a light walk keeps up your fitness while the strain heals, as long as it is pain-free.
- Build back up one step at a time. Move from walking to jogging to sprinting to sport-specific movements, meeting each milestone before you move on. Light jogging comes in once hopping on the injured leg is free of symptoms.Keep pain at 3 out of 10 or less during activity, with no increase the next day. Being pain-free is not enough on its own: returning while still weak is a common reason groin strains come back.
What I use in clinic
- Progressive Lengthening Strength Work (Copenhagen Protocol). Lowered the risk of reporting groin problems by 41% in male soccer players in one trial (three times a week in preseason, once a week in season), and builds inner thigh (adductor) strength for rehab.
- Step-by-Step Rehab Based on Set Criteria. In a program where athletes moved on only when they met set criteria, those with small to moderate inner thigh (adductor) injuries returned to full team training after about 3 weeks, and those who were pain-free on examination before returning had fewer reinjuries.
- Exercise with Hands-On Treatment. For long-standing groin pain, active exercise combined with hands-on treatment (manual therapy) has moderate supporting evidence.
Recovery
How long it takes
With small to moderate strains, return to full training takes about 3 weeks. With complete tears, or where the tendon has pulled off the bone (avulsions), it is usually within about 3 months. Long-standing inner thigh (adductor) pain often takes several months.
Most new (acute) strains heal with the right rehabilitation. Returning before strength and pain-free function are back raises the chance of a reinjury. Long-standing cases often involve strength loss that takes longer to rebuild.
What changes the timeline
- Size of the tear on examination or imaging
- A previous groin injury
- Meeting return-to-sport criteria, including being pain-free, before returning
- Inner thigh (adductor) strength compared with the other side and with the outer hip muscles (abductors)
- What your sport asks of you: sports with kicking and sudden changes of direction often need longer rehab
How I track it. I track how much the pain gets in the way of the tasks that matter to you, how well you move when I test those tasks in clinic, and how confident you feel in daily activities
Similar conditions
Conditions that can feel similar
- Sports Hernia (Athletic Pubalgia)
- Deep groin pain near the groin crease (the inguinal canal), pain with coughing or sneezing, and tenderness over the back wall of the inguinal canal
- Hip Labral Tear
- Clicking or catching, pain on a hip test that bends the hip and lets the knee fall out to the side (FABER), and groin pain when the hip bends and turns
- Osteitis Pubis
- Tenderness in the middle of the pubic bone, gradual onset, and pain spreading to both sides of the groin
- Iliopsoas Strain
- Pain when lifting the leg (hip flexion) and when the muscle is stretched, and tenderness at the front of the hip joint
Questions
What patients ask me most
How long before I am back playing?
It depends on the size of the tear. In a rehab study of male athletes with new inner thigh (adductor) injuries who progressed by meeting set criteria (Serner et al., Orthop J Sports Med 2020), those with small to moderate injuries on MRI returned to full team training after about 3 weeks, and most with a complete tear returned within 3 months. The criteria matter more than the calendar. Returning when pain-free but still weak is a common reason groin strains come back.
Is this a pulled muscle or a sports hernia?
Different problems, and they need different plans. A classic adductor strain is tender right where the main inner thigh muscle attaches to the pelvis (the adductor longus origin), and squeezing the legs together against resistance brings on the pain. What is often called a sports hernia (inguinal-related groin pain in the Doha classification) sits deeper, around the groin crease (the inguinal canal), often flares with coughing, sneezing or sit-ups, and is not clearly brought on by a simple squeeze test. A true hernia, a lump that bulges with coughing or straining, is a different problem again and needs your family doctor's assessment. Serner et al. (BJSM 2016) showed that examination matches imaging well for adductor injuries but misses more with other causes of groin pain, which is why history and exam have to work together.
Should I rest or should I train?
Rest the first two or three days while things are acutely painful. After that, pain-free loading beats continued rest. The Hölmich protocol showed decades ago that active training returned athletes with long-standing adductor pain to sport at a much higher rate than passive physiotherapy (treatment done to you rather than exercise), and the same early-loading pattern shows up across more recent guidelines.
What is the Copenhagen adduction exercise and do I have to do it?
It is a side-lying exercise, with the top leg supported by a partner or a bench, that loads the inner thigh muscles (adductors) with the leg held long, as they lengthen under control (eccentric work). In a trial of male footballers (Harøy et al., BJSM 2019), teams that did it three times a week in preseason and once a week in season had a 41 percent lower risk of players reporting groin problems over the season. I build it into almost every groin rehab and leave it in as long-term prevention for anyone in sports with kicking or sudden changes of direction.
Why does it still hurt weeks later?
Usually one of three things: the load was increased too fast, the loading plan was too light (light bands for a kicking athlete is not enough), or the problem is not just an adductor strain. Pain lasting beyond six to eight weeks is a reason to re-examine, and sometimes to refer you through your doctor for imaging. Long-standing cases often combine adductor-related groin pain with a second problem, such as pain from the pubic bone, which changes the program.
Do I need an MRI?
Not for most new adductor strains. The diagnosis is made from your history and examination, and imaging rarely changes the plan in the first few weeks. I cannot order imaging myself, so I flag it to your family doctor or a sports medicine physician and refer you when imaging would change the plan: a high-grade injury with extensive bruising, when a tendon or piece of bone may have pulled away (an avulsion), when symptoms fail to settle with appropriate loading, or when the history points to the groin crease (inguinal) area or the pubic bone rather than a pure adductor strain.
Can I prevent this happening again?
You can lower the risk. Two common contributors to it coming back are incomplete rehab (returning before strength and equal hops on both legs are back) and dropping adductor loading during the season. Keep the Copenhagen adduction exercise in at least once a week through the season, keep your inner thigh strength up (in one study of professional ice hockey players, adductor strength below 80 percent of outer hip (abductor) strength was linked to more strains), and warm up properly before kicking sessions.
The science
The Science of Groin Strains
Groin strains involve injury to the muscle group, which includes the adductor longus, magnus, brevis, gracilis, and pectineus. The adductor longus is most frequently injured (62-90% of cases), typically at the where muscle fibers transition to tendon.
These injuries occur during high-velocity movements when the muscle undergoes (lengthening under load). The mechanism typically involves forceful hip adduction against an force, or sudden acceleration during sprinting. Sports like soccer, hockey, and football place athletes at highest risk due to the rapid direction changes, kicking motions, and explosive movements required.
When the adductor muscle-tendon complex is overloaded beyond its capacity, microscopic tears develop in the muscle fibers. In acute strains, this creates immediate pain and functional limitation. With ongoing overload, longer-standing changes can develop, such as a problem at the tendon attachment () or bone marrow edema. A substantial tear or needs assessment to decide whether rehabilitation or a surgical opinion is appropriate; some complete tears are managed without surgery.
According to the 2014 Doha Agreement classification system, groin strains fall under "adductor-related groin pain", characterized by tenderness over the adductor muscles and pain provoked by resisted adduction testing. This classification helps distinguish adductor strains from other groin pain causes like hip joint , inguinal canal issues, or pubic .
Contributing factors
The muscles work primarily to pull your leg toward the midline, but their role extends far beyond this simple action. During running and cutting movements, they act as powerful stabilizers of the pelvis and hip, controlling rotation and preventing excessive . When you sprint, the adductors work eccentrically to decelerate your leg during the swing phase, absorbing enormous forces.
The greatest injury risk occurs during movements that combine hip extension, abduction, and external rotation while the adductors are contracting. Think of the final moments of a kick in soccer, or the push-off phase in skating: your leg is extended and spread wide while the adductors are trying to bring it back. This creates high tensile loads at the .
Strength balance matters. In a study of professional ice hockey players (Tyler et al., American Journal of Sports Medicine, 2001), players whose adductor strength was below 80% of their hip abductor strength were much more likely to strain the adductors. Previous injuries create scar tissue that is less elastic than healthy muscle, making reinjury more likely if rehabilitation is incomplete. Fatigue compounds the problem: tired muscles lose their ability to absorb energy efficiently, transferring more stress to the tendon attachment points.
Kicking mechanics in soccer players show that peak adductor activation occurs during the follow-through phase when the leg is decelerating from high velocity. Ice hockey players face similar forces during crossover skating and rapid directional changes. These sport-specific movement patterns help explain why adductor strains made up 23% of muscle injuries in professional European football (Ekstrand et al., American Journal of Sports Medicine, 2011).
Research
What the studies show
Copenhagen adduction exercise program and groin problems in football (soccer)
In this trial, where whole teams were randomly assigned (cluster-randomised), teams doing a one-exercise program based on the Copenhagen adduction exercise (three times a week in preseason, once a week in season) had fewer groin problems: on average through the season, 13.5% of their players had groin problems, compared with 21.3% in the control teams. Players' risk of reporting groin problems was 41% lower than in the control teams.
Supports keeping the Copenhagen adduction exercise in the program for players in sports with kicking and sudden changes of direction.
Harøy J, Clarsen B, Wiger EG, et al. The Adductor Strengthening Programme prevents groin problems among male football players: a cluster-randomised controlled trial. Br J Sports Med. 2019;53(3):150-157. PMID: 29891614.
Non-surgical treatment of long-standing inner thigh (adductor) groin pain: a review of the research
The review found the best-supported non-surgical options for long-standing adductor-related groin pain were active strengthening combined with hands-on treatment (manual therapy), compression clothing, and prolotherapy injections (a type of injection meant to stimulate healing), each with only moderate-quality evidence.
Supports an exercise-based plan for longstanding groin pain, with realistic expectations about the strength of the evidence.
Bisciotti GN, Chamari K, Cena E, et al. The conservative treatment of longstanding adductor-related groin pain syndrome: a critical and systematic review. Biol Sport. 2021;38(1):45-63. PMID: 33795914.
Related Conditions
Conditions I commonly see alongside, or confused with, this one.
Femoroacetabular Impingement (FAI)
Both cause groin/hip flexor pain; FAI can predispose to muscle strains
Hamstring Strains
Both are common sports injuries affecting hip/thigh muscles with similar mechanisms
Proximal Hamstring Tendinopathy
Both affect proximal thigh muscles; can have overlapping symptoms in posterior hip
Sacroiliac (SI) Joint Dysfunction
Adductor muscle imbalances can affect pelvic stability and SI joint function
Hip Osteoarthritis
Getting back to it
Physiotherapy for groin strains, built around the activity you want back.
