
Tennis Elbow
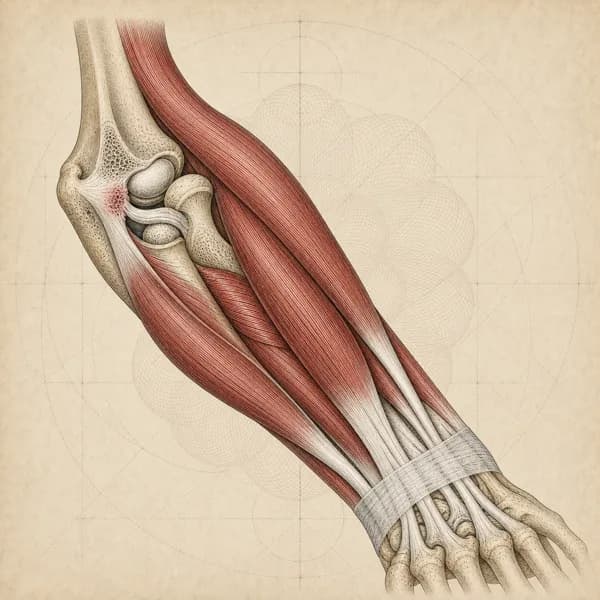
Tennis elbow (lateral epicondylalgia) is pain on the outside of the elbow, where the tendons that lift the wrist attach to the bone. Most people who have it do not play tennis; symptoms are often linked to gripping, lifting and wrist use. Shaking hands, lifting a cup or turning a door handle can hurt.
Key points
- What usually helps
- Strengthening the muscles that lift the wrist, built up gradually, while managing how much load the arm takes.
- What you can do now
- Ease the grip load across your day. Set up your mouse and desk.
- How long it takes
- Meaningful change within 6 to 12 weeks for many; recovery commonly takes 3 to 6 months.
- When to see a doctor first
- Some signs need medical care the same day. Check the list before you start treatment.
Symptoms
Does this sound like you?
- Pain and tenderness over the bony bump on the outside of the elbow (the lateral epicondyle)
- A weaker grip, especially with the palm facing down
- Pain when you lift the back of the hand, or turn the palm up, against resistance (resisted wrist extension or supination)
- Pain during gripping activities (handshake, turning doorknob)
- Difficulty lifting objects, especially with the elbow straight
Often alongside it
- Pain radiating down the forearm toward the wrist
- Morning stiffness in the elbow and forearm
- Difficulty with simple tasks requiring grip (opening jars, using tools)
- Shoulder and neck tension from using the arm differently
- Occasional burning along the outer forearm
Pain comes on gradually over weeks to months. It is typically worse after repetitive tasks and with sustained gripping. It often improves with rest but returns quickly when activity starts again. Morning stiffness is common.
Before using this comparison, check when these symptoms need a doctor first.
When to see a doctor first
Get seen today
Sudden inability to straighten the fingers or lift the wrist
Same-day medical assessment for a nerve problem in the forearm
Severe swelling, deformity, or pain that started with a fall or a blow
Go to emergency or urgent care to rule out a fracture, dislocation, or tendon rupture
Check with your doctor
Weakness that keeps getting worse, especially with numbness or tingling
See your family doctor before starting physiotherapy, to check for a pinched nerve in the neck or arm
Catching, locking, or giving way of the elbow
See your family doctor, who can arrange imaging to check for a loose fragment or ligament injury
No improvement or worsening after 3 months of appropriate treatment
I flag it to your family doctor, who can arrange imaging or a specialist opinion and discuss injection or surgery if needed
Treatment
How it is treated
Main approach. Strengthening exercises for the muscles that lift the wrist (the wrist extensors), built up gradually and including slow lowering work (eccentric exercise), are the core of care in current guidance. Combined with managing how much load the arm takes, they can help reduce pain and improve grip over roughly 12 weeks.
Alongside it. Hands-on treatment (manual therapy), such as soft tissue work and joint mobilization, can give short-term pain relief when combined with exercise. Adjusting daily activities helps limit flare-ups during rehab.
Managing it over time. Adjusting your workstation and the way you grip may lower the load on the tendon, especially holding the wrist bent back or the palm turned down for long spells (sustained wrist extension and pronation). Ongoing strengthening helps the tendon keep up with the demands of work and sport.
A typical rehabilitation progression
Three phases, from settling symptoms to returning to full activity.
Recovery from tennis elbow is usually staged: calm the symptoms first, then rebuild the strength and capacity of the area, then return to your full activities. The phases below show how that can progress.
Phase 1Settle the Tendon and Start Loading (Weeks 1 to 3)
Calm the worst of the symptoms, load the tendon on the outside of the elbow (the extensor tendon) at a level it can tolerate, and use the 24-hour symptom rule (how the elbow responds over the next day) to guide progress. Holding the muscle tight without moving the wrist ( exercise) offers short-term pain relief and a safe way to start loading. Changes to daily activities come first in this phase, because cutting the heaviest loads of the day matters more than any single exercise.
Example exercises
- Wrist extension holds without moving (isometric): elbow bent to about 90 degrees, forearm supported, pushing the back of the hand up against a light weight or band for 5 sets of 30 to 45 seconds, at a pain level no higher than 3 out of 10
- Gentle stretch for the muscles on the palm side of the forearm (wrist flexor stretch), 3 holds of 30 seconds, 2 to 3 times per day
- Grip squeezes with a soft ball at less than full effort, 3 sets of 10, without bending the wrist fully back while gripping
- Shoulder blade setting and rows with a light band, 3 sets of 10, to build support further up the arm at the shoulder
- Workstation or tool changes: a vertical mouse, or the mouse moved closer to the keyboard, chair and desk height checked, and short breaks every 20 to 30 minutes during gripping tasks
Possible progression milestones
Possible milestones, adapted to the person rather than treated as fixed cut-offs: the wrist holds feel comfortable, no more than mild next-day soreness after sessions over several days in a row, and grip on everyday tasks such as carrying a coffee mug or opening a door no longer provoking sharp pain.
Phase 2Building Up the Muscles That Lift the Wrist (Weeks 3 to 8)
Build the tendon's tolerance with heavier, slower exercises. In a randomised trial (Tyler and colleagues, 2010), adding the Tyler exercise to standard physiotherapy improved pain and function; it uses a flexible rubber bar to slowly lower the wrist against resistance ( wrist extension), with the other hand helping it back to the start. Peterson and colleagues (2014) found slow lowering training (eccentric) reduced pain somewhat faster than lifting training (). Some discomfort during these exercises, up to 5 out of 10, is acceptable provided it settles within 24 hours.
Example exercises
- Tyler exercise with a flexible rubber bar (Flexbar), 3 sets of 15 once daily, moving to a stiffer bar as tolerated
- Heavy slow resistance wrist lifts with a dumbbell (lifting the back of the hand), 3 seconds up and 3 seconds down, 3 sets of 10 to 15, 3 times per week
- Turning the palm up and down (supination and ) holding a light hammer or weighted lever, 3 sets of 10 to 12 each direction
- Grip work that builds up over time, using a grip trainer or towel squeezes with the wrist gradually more bent back, 3 sets of 10
- Continued shoulder blade and strengthening, 2 to 3 sets of 10 to 12, so the forearm does not take extra load to make up for the shoulder
Possible progression milestones
Possible milestones, adapted to the person rather than treated as fixed cut-offs: pain-free grip strength closer to the unaffected side, heavier sessions settling without a 24-hour flare over several weeks, and scores on a tennis elbow pain and function questionnaire (PRTEE) clearly falling from where they started.
Phase 3Return to Full Work, Sport, and Heavier Loading (Weeks 8 to 16+)
Rebuild the specific demands of your work and sport. For office workers this means long spells of gripping, mouse and keyboard work. For trades and gym users it means tool use, carrying, and overhead or pushing loads. For racquet sports it means a gradual return with attention to technique, often with a coach reviewing the backhand.
Example exercises
- Heavy carries with both hands, then one hand (farmer carries, suitcase carries), over gradually longer distances
- Pull-ups, rows and deadlift variations worked into the week, focusing on how long you can hold a grip rather than how hard you can squeeze
- A return to your sport, such as mini-tennis and controlled rallying before full match play, or for trades a step-by-step return to hammering and long spells of tool use
- Ongoing Tyler exercise or heavy slow resistance wrist work 2 times per week to keep up strength during the return to sport
- A second look at your workstation set-up once symptoms are under control, to check that the daily load really has changed
Possible progression milestones
Possible milestones, adapted to the person rather than treated as fixed cut-offs: low pain during full work or sport demands, grip strength close to the other side, and a sustained return to full duties without a 24-hour symptom flare.
What you can do now
- Ease the grip load across your day. Flare-ups often come from the total gripping across a day rather than one bad movement, so use thicker handles, grip with the whole hand rather than pinching with the fingertips, and break up long spells of gripping. A tennis elbow strap (counterforce brace) can ease pain during a heavy task you cannot avoid, but it does not build the tendon's tolerance, so use it alongside the exercises, not instead of them.If the elbow flares in the evening after a fine day at work, ease the whole day's grip load rather than hunting for one bad task. Make grip changes gradually, so another part of the arm does not take over the work.
- Set up your mouse and desk. A vertical mouse, a pointer speed and mouse position that avoid repeated large wrist movements, and the right keyboard and chair height reduce how long the wrist stays bent back. Take a short break every 20 to 30 minutes during computer or gripping work.
- Start with wrist holds. With the elbow bent to about 90 degrees and the forearm supported, push the back of the hand up against a light weight or band without letting it move, and hold for 30 to 45 seconds, 5 times. Holding still like this (isometric exercise) offers short-term pain relief and is a safe way to start loading the tendon.Keep the pain during the holds at 3 out of 10 or less.
- Add slow lowering exercises next. Once the holds feel comfortable, slowly lowering a weight with the wrist (eccentric exercise) builds the tendon's tolerance to load; use your other hand to bring the weight back up, so the sore side only does the lowering. One version uses a flexible rubber bar (the Tyler exercise).Some discomfort during the exercise, 3 to 4 out of 10, is acceptable. Sharp pain, or pain lasting more than 24 hours, means the load was too much, so make it lighter.
- Judge the load by the next morning. If the elbow is no worse, or calmer, over a few mornings, the load is probably about right, and morning stiffness that eases quickly with movement is usually not a sign you overdid it. Spread heavy tasks through the week rather than bunching them together.Do not stop the exercises in the quieter middle weeks, when the pain has settled but strength has not caught up yet.
What I use in clinic
- Slow lowering exercises (eccentric strengthening). Exercise is the mainstay of care in the 2022 clinical practice guideline for tennis elbow (JOSPT). Adding the Tyler exercise, slow lowering with a flexible rubber bar, to standard physiotherapy improved pain and function in a randomised trial, and one trial found lowering (eccentric) training reduced pain somewhat faster than lifting (concentric) training, though trials comparing exercise types are mixed.
- Hands-on treatment (manual therapy). Some evidence for short-term pain relief when combined with exercise. Includes gentle elbow and wrist joint movement (mobilization) and soft tissue work for the muscles on the back of the forearm (the extensors).
- Activity and load changes. An essential part of care, supported by clinical consensus and biomechanical research; the practical steps are under What you can do now.
- Dry Needling. Emerging evidence for pain relief and better function, particularly when needling tender, irritable spots (active trigger points) in the forearm extensor muscles whose pain pattern matches your symptoms.
- Ongoing strength training. Continuing to build strength after the early phase can improve load tolerance for work and sport; evidence on preventing recurrence is limited.
- Education. Understanding the condition and how much daily activity to do can help people stay with a strengthening program through the slower middle weeks.
Recovery
How long it takes
Most people notice meaningful change within 6 to 12 weeks of consistent strengthening exercise, and recovery commonly takes 3 to 6 months. Cases that have lasted longer before treatment tend to take longer.
Many cases improve on their own over a year or so. In the BMJ trial by Bisset and colleagues (2006), physiotherapy improved symptoms faster than waiting in the first six weeks, and by one year most people in both groups reported a good outcome. A structured program mainly shortens the time spent limited by pain.
What changes the timeline
- How long you have had symptoms (a longer history is linked with slower recovery)
- How much tendon change a scan shows (more severe changes may need longer treatment)
- The demands of your work, and whether you can change aggravating activities during rehab
- Keeping up the strengthening program as it builds up
- A neck or shoulder problem at the same time (these need treating too)
- Grip strength at the start (a weaker grip is linked with slower recovery)
- Worry and stress, including fear of movement (kinesiophobia) and expecting the worst about the pain (catastrophizing)
- Earlier treatments that did not work, or several cortisone injections (may point to a more complex case)
How I track it. I measure grip strength with a grip meter (dynamometer), comparing both sides. I check your pain with specific tests, such as lifting the back of the hand against resistance or gently stretching the forearm muscles (Mill's test), and track the key activities that were hard at the start. Tracking your pain during and 24 hours after specific tasks helps guide how fast the load goes up
Similar conditions
Conditions that can feel similar
- Radial Tunnel Syndrome
- Pain sits 4 to 6 cm below the bony bump on the outer elbow rather than directly on it. It is brought on by turning the palm up, or lifting the middle finger, against resistance. There is typically no pain at the bump itself when the back of the hand is lifted against resistance.
- Cervical Radiculopathy (C6 or C7)
- Pain mainly in the neck that spreads into the arm along the strip of skin one nerve root supplies (a dermatome). Turning and tilting the head toward the sore side with gentle downward pressure brings on the arm symptoms (Spurling's test), and there may be numbness or weakness in that nerve's area, rather than one tender spot at the outer elbow.
- Posterolateral Rotatory Instability
- The elbow feels as if it gives way, and you feel it might slip when it straightens with the palm turned up. Pushing up out of a chair with your arms brings this on (chair push-up test), as can a specific instability test (pivot shift). There is often a history of elbow dislocation or a significant injury.
- Radiocapitellar Osteoarthritis or Osteochondritis Dissecans
- Catching or locking in the joint, with pain deeper inside the joint rather than where the tendon attaches. Osteochondritis dissecans (damage to the cartilage and the bone just beneath it) is more common in teenagers. The changes show on imaging.
- Plica or Snapping Triceps
- A snapping or clicking at the outer or back of the elbow that happens each time it bends and straightens. The tender spot is at the back of the outer elbow rather than where the forearm tendons attach, and symptoms come more from movement than from load.
- Referred Pain from Rotator Cuff or Cervical Facet
- A spread-out ache in the elbow and forearm without one tender point. Tests of the shoulder or neck bring on the symptoms, while loading the elbow does not, and the pain does not reliably follow gripping or lifting the back of the hand against resistance.
Commonly confused with
Side-by-side comparisons for patterns that often get mistaken for tennis elbow.
Questions
What patients ask me most
Is tennis elbow actually caused by tennis?
Usually not. Only a small share of people with tennis elbow play racquet sports. The name stuck because tennis was one of the first activities formally associated with it, but it is more often linked to forceful or repeated gripping at work, trades and tool use, and sudden spikes in gym training or yard work. Computer work can aggravate it for some people. What seems to matter is that the load was more than the tendon was ready for at the time, not which activity it was.
How long does tennis elbow take to heal?
With a well-structured loading program, most people notice meaningful change by 6 to 12 weeks, and recovery commonly takes 3 to 6 months. The JOSPT 2022 Clinical Practice Guideline on lateral elbow tendinopathy (Lucado et al.) supports exercise as the mainstay of care. Longer symptom duration before starting rehab has been linked to slower recovery in some studies, although many cases also settle on their own over a year or so.
Should I get a cortisone shot for tennis elbow?
I would steer you away from it in most cases. Bisset and colleagues in the BMJ (2006) randomised patients to physiotherapy, corticosteroid injection, or wait-and-see. Injections did best at 6 weeks, but most of those early successes did not last, and long-term outcomes were poorer than with physiotherapy. Coombes et al. in JAMA (2013) found the same pattern, with lower complete recovery at one year after corticosteroid than after a placebo injection.
Does a tennis elbow strap actually work?
Counterforce braces can give short-term pain relief during specific tasks by shifting where the load is taken, away from the irritated spot where the tendon attaches. They are not a treatment in themselves. I use them as a bridge while the loading program builds tendon capacity, not as a substitute for exercise. A strap on its own does not build the tendon's tolerance, so I pair it with the loading program.
Is it okay to keep using my computer and working while I have tennis elbow?
Most people need to, and complete rest is not usually needed anyway. What matters is reducing peak load spikes. That can mean a vertical mouse, adjusting pointer speed and mouse position so you can use it comfortably without repeated large wrist movements, keyboard and chair height changes, micro-breaks every 20 to 30 minutes, and tempo changes on high-grip tasks. If your elbow is less irritable by the morning, yesterday's load was acceptable.
Why does my elbow hurt when I shake someone's hand or lift a coffee cup?
The main tendon involved (extensor carpi radialis brevis) is loaded whenever the muscles that lift the back of the hand (the wrist extensors) work to steady the hand during a grip. A handshake, a full coffee mug, or a kettle all demand exactly that pattern, and they happen with the elbow fairly straight, which concentrates load at the bony bump on the outer elbow. It is a classic pattern, not a sign of serious damage.
When should I consider imaging or surgery for tennis elbow?
Imaging is usually unnecessary up front because the diagnosis is clinical. When symptoms fail to respond to 3 months of appropriate loading, when a partial tear is suspected, or when the story does not fit tendinopathy, I flag it to your family doctor or specialist and refer you for ultrasound or MRI, because then the result could change the plan. Surgery is a last-resort conversation, typically only after 6 to 12 months of well-delivered conservative care has not produced meaningful change.
Will my tennis elbow come back after it heals?
Recurrence is a real risk if the loading pattern that caused it has not changed. The tendon can rebuild its capacity, but if your mouse, tool, or training setup still exceeds what that capacity tolerates, symptoms tend to return. I treat the final phase of rehab (heavier strengthening, and changes at work or in sport) as prevention more than rehab.
The science
The Science of Tennis Elbow
Lateral (tennis elbow) is a affecting the common extensor tendon origin at the , primarily involving the extensor carpi radialis brevis (ECRB) tendon. Despite the name, only a small share of cases occur in tennis players. The condition is characterized by a failed healing response resulting in angiofibroblastic degeneration rather than acute inflammation.
The begins with repetitive mechanical overload of the wrist extensors exceeding the tendon's adaptive capacity. This leads to microtears, disorganized structure, increased ground substance, , and neurogenic inflammation. Histologically, the tissue shows angiofibroblastic hyperplasia with absence of inflammatory cells, confirming this is tendinosis rather than .
The ECRB is particularly vulnerable due to its anatomical position and biomechanical demands. It originates from a small area on the lateral epicondyle and must generate force across both the elbow and wrist joints. During gripping and wrist extension activities, the ECRB experiences high tensile loads, especially with the elbow extended and forearm , the position used during much computer work and manual labor.
Neurogenic occurs in chronic cases, with elevated substance P and calcitonin gene-related peptide in the affected tendons. This contributes to pain amplification and may explain why some cases become recalcitrant to treatment. The condition often coexists with and shoulder dysfunction, as neural and biomechanical factors from proximal regions can perpetuate or exacerbate symptoms.
Risk factors include age 40-50 years (peak incidence), occupations requiring repetitive gripping and wrist extension (construction, manual labor, computer work), poor wrist posture, inadequate forearm strength, and sudden increases in hand-intensive activities. Similar to golfer's elbow (medial epicondylalgia), this represents failed tendon healing, though it affects the lateral rather than medial elbow and involves different muscle groups.
Contributing factors
The biomechanical drivers of tennis elbow center on repetitive of the wrist extensors during gripping and wrist stabilization tasks. When you grip an object, your wrist extensors must contract to prevent wrist flexion and maintain functional hand position. This creates tensile stress at the , particularly when gripping with the elbow extended and forearm .
Computer work can add load for some people. During mouse use, the wrist extensors hold the wrist position against the weight of the hand while performing fine motor control, and long periods with the wrist held extended keep those muscles working. Keyboard use with the wrists propped on pads can do the same. This is a plausible loading mechanism rather than proof that ordinary computer work damages the tendon; many people use a computer all day without elbow pain, and how the tendon responds depends on the total load, recovery, and general health.
Manual labor and tool use create even higher loads. Using a screwdriver requires forceful gripping combined with wrist stabilization against rotational torque. Hammering involves rapid eccentric loading as the tool decelerates after impact. Painting with a brush or roller demands sustained of wrist extensors to control the implement. Carrying shopping bags with handles or lifting objects with a pronated grip (palm down) maximizes stress on the lateral extensors compared to supinated (palm up) grips.
Sports reveal why tennis players get this injury despite representing a minority of cases. During the backhand stroke, especially with poor technique using excessive wrist extension and late contact point, massive eccentric forces load the wrist extensors at ball impact. One-handed backhands create even higher demands than two-handed technique. However, any racquet sport, weightlifting with poor wrist position, or golf can create similar loading patterns.
Poor proximal mechanics amplify distal loading. Weak scapular stabilizers cause compensatory wrist extension during reaching tasks. Limited rotation forces the wrist and forearm to generate movement that should come from the trunk. dysfunction can alter motor control of the forearm muscles through neural mechanisms. Even something as simple as lifting with your elbow locked out rather than slightly bent can increase the load on the lateral epicondyle.
Grip technique and tool design can matter. Larger diameter grips distribute pressure over more surface area, reducing tendon stress compared to thin handles. Powered tools reduce sustained muscle contraction compared to manual tools. Ergonomic modifications like vertical computer mice minimize forearm pronation, while proper desk height prevents excessive wrist extension during typing.
Research
What the studies show
Adding slow lowering exercises for the wrist to standard physiotherapy improved pain and function
A randomised trial (Tyler, Thomas, Nicholas and McHugh, 2010, Journal of Shoulder and Elbow Surgery) studied people with long-standing tennis elbow. Adding one slow lowering exercise for the wrist (eccentric wrist extension), done with a flexible rubber bar, to standard physiotherapy improved pain and function clearly more than standard physiotherapy alone. Broader reviews of exercise for tennis elbow also favour gradually built-up loading over passive treatment or waiting to see, though the size of the benefit varies between trials.
Supports slow lowering exercises as part of a program that builds up gradually. The size of the benefit varies between trials, so steady, well-judged progress matters more than any one exercise.
Tyler TF, Thomas GC, Nicholas SJ, et al. (2010). Addition of isolated wrist extensor eccentric exercise to standard treatment for chronic lateral epicondylosis: a prospective randomized trial. J Shoulder Elbow Surg. PMID: 20579907.
Cortisone injections gave short-term relief but worse results at one year than physiotherapy
A randomised trial (Coombes, Bisset, Brooks, Khan and Vicenzino, 2013, JAMA) found that a cortisone (corticosteroid) injection gave better short-term relief, but clearly fewer people had fully recovered at one year, and more had a recurrence, than with a placebo injection or physiotherapy. This matches earlier work by Bisset and colleagues (BMJ, 2006): the injection did better than physiotherapy and waiting to see at six weeks, but led to worse results and more recurrences by 52 weeks.
Injections can give short-term relief, but they did not improve one-year outcomes and were followed by more recurrences. If one is considered, it belongs alongside a loading program, not in place of it.
Coombes BK, Bisset L, Brooks P, et al. (2013). Effect of corticosteroid injection, physiotherapy, or both on clinical outcomes in patients with unilateral lateral epicondylalgia: a randomized controlled trial. JAMA. PMID: 23385272. Bisset L, Beller E, Jull G, et al. (2006). Mobilisation with movement and exercise, corticosteroid injection, or wait and see for tennis elbow: randomised trial. BMJ. PMID: 17012266.
Related Conditions
Conditions I commonly see alongside, or confused with, this one.
Golfer's Elbow
Both are elbow tendinopathies affecting opposite sides of the joint
Repetitive Strain Injuries
Tennis elbow is a type of repetitive strain injury from overuse
Carpal Tunnel Syndrome
Both can result from poor wrist/forearm ergonomics and repetitive motions
Neck Pain & Stiffness
Cervical radiculopathy can mimic lateral elbow pain symptoms
Shoulder Impingement Syndrome
Shoulder dysfunction can alter elbow mechanics and contribute to lateral epicondylitis
De Quervain's Tenosynovitis
Getting back to it
Physiotherapy for tennis elbow, built around the activity you want back.
