
Sacroiliac (SI) Joint Dysfunction
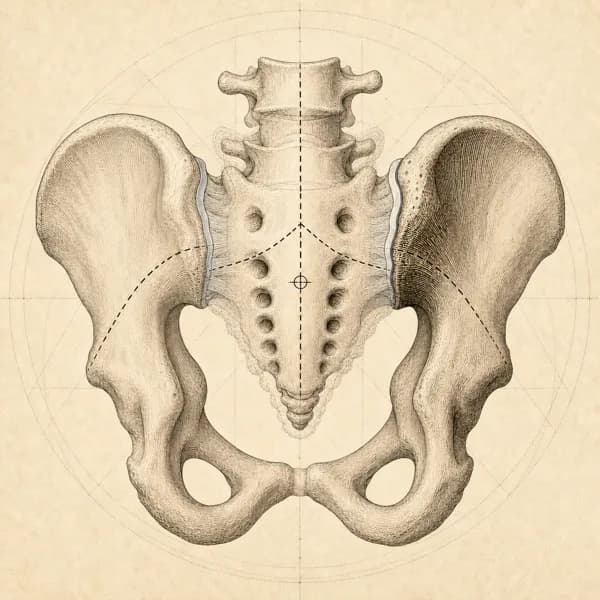
Sacroiliac (SI) joint-related pain is pain thought to arise from the joint or nearby ligaments where the spine meets the pelvis. It may be felt below the belt line or in the buttock and aggravated by turning in bed or stairs. Similar symptoms can come from the back or hip, so assessment matters.
Key points
- What usually helps
- Strengthening the trunk and buttock muscles, with hands-on treatment where it helps.
- What you can do now
- Roll in bed as one unit. Keep walks short and even at first.
- How long it takes
- Many people improve over 6 to 8 weeks; some take longer.
- When to see a doctor first
- Some signs need emergency care. Check the list before you start treatment.
Symptoms
Does this sound like you?
- Pain on one side of the lower back, typically below the lowest lumbar vertebra (L5) and around the bony bump at the back of the pelvis (the posterior superior iliac spine)
- Pain that may spread to the buttock, groin or back of the thigh
- Pain when changing position, like rolling in bed or getting up from sitting, or when climbing stairs
- Pain that is often worse on one side
- Morning stiffness that improves with movement
Often alongside it
- A feeling that the pelvis is unstable or 'giving way'
- Difficulty with single-leg activities like putting on pants
- Pain with long periods of sitting or standing
- Poor sleep because it is hard to get comfortable
- Changes in how you move that affect the way you walk
I often see patients who can pinpoint their pain to a specific area just below their belt line on one side. Many describe difficulty with activities that involve standing on one leg or changing position. The pain pattern can be confusing because the pain is often felt away from the joint itself.
Before using this comparison, check when these symptoms need a doctor first.
When to see a doctor first
Go to emergency
With back pain: new trouble starting to pass urine or feeling it pass, new loss of bladder or bowel control, new numbness between the legs or around the back passage, new loss of genital sensation or sexual function, or severe or rapidly worsening weakness in both legs
Possible cauda equina syndrome. Go to emergency now
Get seen today
Numbness that keeps spreading, a new foot drop (the foot catches or slaps when you walk), or weakness in one leg that is getting worse
Possible nerve compression. Same-day medical assessment
Severe pain with fever or feeling unwell
Possible infection or inflammatory condition. Same-day medical assessment
Check with your doctor
No improvement after 8 to 10 weeks of appropriate treatment
I flag it to your family doctor, who can arrange imaging or a referral to look for other causes or discuss an injection
Treatment
How it is treated
Main approach. Strengthening the trunk and buttock (gluteal) muscles, with hands-on treatment where it helps, can improve pain and function in SI joint pain. The research behind any one approach is limited.
Alongside it. Hands-on treatment may ease pain for a short time and make movement easier, while trunk and hip strengthening builds the support around the joint.
Managing it over time. Strengthening the trunk muscles (core) and learning better ways to move support the stability of the pelvis and how forces pass through it, which can help reduce the risk of SI joint dysfunction.
A typical rehabilitation progression
Three phases, from settling symptoms to returning to full activity.
Recovery from sacroiliac joint dysfunction is usually staged: calm the symptoms first, then rebuild the strength and capacity of the area, then return to your full activities. The phases below show how that can progress.
Phase 1Foundation: Settle Symptoms and Rebuild Muscle Support
The relies heavily on the deep trunk and buttock muscles (glutes) to hold it steady (force closure). Early rehabilitation cuts down what sets the pain off, introduces gentle exercises to switch on the glutes, and teaches ways of moving that take load off the joint during daily tasks.
Example exercises
- Bridge on both legs (lying on your back, lifting the hips), 2 sets of 8 to 10, keeping the pelvis even
- Lying on your back with knees bent, slow belly breathing (diaphragmatic breathing) with a gentle tightening of the stomach muscles, 5 to 10 breaths, several times a day
- Clamshells (lying on your side with knees bent, opening the top knee) with a light band, 2 sets of 10 to 12 per side
- Rolling in bed with the shoulders and hips turning together (log-rolling), and getting in and out of bed with a hip hinge, to reduce uneven twisting of the pelvis
- Short walking intervals (5 to 10 minutes), avoiding long strides and uneven terrain in the first 1 to 2 weeks
Possible progression milestones
Standing on one leg for 30 seconds without bringing on pain, rolling in bed without a spike in symptoms, and sitting for 30 to 45 minutes without a meaningful flare.
Phase 2Progressive Loading: Build Hip, Trunk and One-Sided Strength
The second phase rebuilds the strength needed for real-world demands, especially tasks that load one side more than the other, like stairs, step-ups and single-leg tasks. A diagonal chain of muscles across the back (the posterior oblique sling) links the large back muscle on one side (latissimus dorsi) to the main buttock muscle on the other (gluteus maximus) through the tough connective tissue of the lower back (thoracolumbar ). Switching on this chain plays a direct role in SI joint stability.
Example exercises
- Single-leg bridge and hip thrust (lifting the hips with the upper back on a bench), 3 sets of 6 to 10
- Hip hinge progressions (bending forward from the hips): kettlebell deadlift, then split-stance and single-leg Romanian deadlift
- Step-ups onto a box, 3 sets of 6 to 10 per side, progressed in height and load
- Side plank, and the Pallof press (holding a band or cable straight out in front while resisting its pull to twist you), for trunk control sideways and against twisting
- Split squat and lunge variations, initially slow and controlled, then progressing to walking lunges
Possible progression milestones
Single-leg step-ups and split squats without bringing on SI pain, walking 30 to 45 minutes comfortably, and a full workday without symptoms building up.
Phase 3Return to Function: Impact, Turning and Preventing It Coming Back
The final phase brings back impact, turning and the specific demands of your sport or job. The priority is building enough reserve that minor flares do not derail what you can do, and setting up a maintenance plan that keeps the hips and trunk loaded.
Example exercises
- Trap-bar or standard deadlift, with the load built up gradually, 3 to 4 sets of 3 to 6
- Goblet squat (holding a weight at the chest) and front squat, to working depth and load, matched to your goals
- Carrying weights in both hands, or in one hand like a suitcase (loaded and suitcase carries), 3 to 4 rounds of 30 to 40 metres
- Return to running through a walk-run progression, with early focus on flat, even terrain
- Turning exercises with a cable (chops and lifts, diagonal pulls across the body) at moderate load, 3 sets of 8 to 10 per side
Possible progression milestones
Back to work, sport and home demands with minimal or no symptoms, confidence managing minor flares on your own, and a written maintenance plan that keeps buttock and trunk training going.
What you can do now
- Roll in bed as one unit. Turning in bed and getting up are common triggers. Roll with your shoulders and hips turning together (log rolling), and get in and out of bed by hinging at the hips.
- Keep walks short and even at first. Short walks of 5 to 10 minutes keep you moving while the joint settles. For the first week or two, avoid long strides and uneven ground.
- Favour two-legged exercises for now. Exercises that load one side more than the other, like single-leg deadlifts, lunges and step-ups, sometimes flare SI pain early on. Start with bridging, hip hinges on both legs and trunk work, then bring single-leg work back step by step as symptoms settle.
- Change position often. Long periods of sitting or standing can aggravate SI joint pain. Avoid staying in one position for a long time, and use supportive seating when you can.
- Try a pelvic belt for flare-prone tasks. A sacroiliac or pelvic support belt can reduce symptoms during activities that reliably flare the joint, particularly in pregnancy and soon after the birth. Use it as a short-term tool while your buttock and trunk muscles get stronger, not as a long-term solution.
What I use in clinic
- Manual Therapy and Joint Mobilization. Hands-on treatment may reduce pain and disability, mostly when it is combined with targeted exercise.
- Targeted Exercise Therapy. Exercise built around trunk and hip strength can improve function in SI joint pain.
- Control and Stability Training. Exercises for the deep trunk muscles and pelvis help control load through the pelvis during daily tasks and sport. Strengthening the deep abdominal and pelvic floor muscles helps them hold the joint firmly (force closure) and improves its stability. The focus is on quality over quantity, without holding your breath.
- Kinesio Taping. Combined with exercise and hands-on joint mobilization, stretchy tape applied to the skin (kinesio taping) may help reduce pain.
- Movement Pattern Correction. Correcting changes in the way you walk, and other compensating movements, improves long-term outcomes.
Recovery
How long it takes
Many people improve over 6 to 8 weeks of appropriate treatment, although some take longer.
Many people with SI joint pain improve with a combination of hands-on treatment and hip and trunk strengthening built up gradually.
What changes the timeline
- How long the pain has been present before treatment starts
- Keeping up the home exercise program, which matters for keeping your gains
- Working on contributing factors, such as hip mobility, may help
- SI joint pain related to pregnancy may need a modified approach but generally responds well
How I track it. I track your pain during specific activities like standing on one leg and changing position, improvements in everyday tasks, and how much less you rely on compensating movements
Similar conditions
Conditions that can feel similar
- Lumbar Facet-Mediated Pain
- Pain in the middle of the lower back or just beside the spine, worse with bending backward and twisting, eased by bending forward. The pain typically does not spread below the knee. Tenderness is more central, along the muscles beside the lower spine, than at the bony bump at the back of the pelvis (the PSIS).
- Lumbar Radiculopathy
- Leg pain following the strip of skin supplied by one nerve root (a dermatome), usually going below the knee, often with pain on nerve tension tests (straight leg raise or slump) and sometimes weakness in the muscles that nerve supplies. Aggravated by bending forward and sitting rather than by standing on one leg.
- Hip Joint Pathology (Osteoarthritis or Labral Tear)
- Groin or front of thigh pain, with turning the hip inward reduced and painful. Hip tests (FADIR or FABER) bring on the groin pain. Aggravated by turning on a weight-bearing leg rather than by tests that stress the SI joint.
- Proximal Hamstring Tendinopathy
- Pain at the sitting bone (ischial tuberosity), worse sitting on firm surfaces, bending the hip deeply and lunging. Testing the hamstring against resistance while it is lengthened, and pressing where it attaches, bring it on.
- Inflammatory Sacroiliitis (Axial Spondyloarthritis)
- Gradual onset under age 40, morning stiffness over 30 to 60 minutes, improvement with exercise but not rest, and frequent night waking. Often buttock pain that switches between sides, raised inflammation markers on blood tests, or a positive HLA-B27 gene test. It needs a medical referral rather than managing movement and load alone.
- Piriformis / Deep Gluteal Syndrome
- Pain deeper in the middle of the buttock rather than at the bony bump at the back of the pelvis, often spreading like sciatica into the back of the thigh and sometimes below the knee. Pressing deep in the buttock, and a test that bends, crosses and turns the hip inward, bring it on, not the group of SI joint tests.
Questions
What patients ask me most
How is SI joint pain actually diagnosed?
From the history and examination, by looking at several tests that try to bring on the pain (distraction, thigh thrust, compression, sacral thrust) together, alongside an examination of the back and hips, rather than relying on a single test. Laslett and colleagues (Manual Therapy 2005) found that combinations of these tests matched diagnostic injections (numbing injections into the joint) better than single tests. A 2021 meta-analysis (Saueressig et al., JOSPT) rated the evidence as very low certainty: a positive group of tests is not enough to confirm the SI joint as the source, while a negative group makes it much less likely. Positive tests also do not by themselves predict how well rehabilitation will go. Imaging rarely confirms the source, so the history and exam usually drive the working diagnosis.
Is my SI joint actually out of place?
Almost certainly not in the way that is often described. The SI joint moves only around 2 to 4 millimetres and 2 to 4 degrees, and no reliable hands-on test detects small changes in position. What people feel as "out" is typically changed movement, muscles guarding the area, and tenderness, all of which respond to load and training rather than to repeated adjustment.
Why does pregnancy make SI pain so common?
Hormonal changes loosen the ligaments around the pelvis, and the growing baby shifts the body's centre of mass forward, which together load the SI joint differently. Pelvic girdle pain is common in pregnancy. Most cases settle after the birth, particularly when glute and trunk strength is rebuilt with a graded program.
How long does SI joint pain usually take to settle?
Many people improve over 6 to 8 weeks with a combination of hands-on treatment and graded strengthening of the deep trunk and buttock (gluteal) muscles, although some take longer. It is not uncommon for it to come back in the first year, particularly when load drops off, which is why a maintenance program matters as much as the initial rehab.
Is a pelvic support belt a good idea?
Short-term, yes, for many people. A sacroiliac or pelvic belt can reduce symptoms during activities that reliably flare the joint, particularly in pregnancy and soon after the birth. It is a tool for the early phase rather than a long-term solution. Over time, the belt is standing in for the firm hold the glutes and trunk muscles give the joint (force closure).
Can I run or lift with SI joint pain?
Often yes, with targeted changes. Exercises that load one side more than the other, like single-leg deadlifts, lunges and step-ups, sometimes flare SI symptoms early on, so in the first phase I often shift the program toward hinging at the hips on both legs, bridging and trunk work. As symptoms settle, single-leg and impact loading come back in step by step.
Do I need an SI joint injection or surgery?
Surgery (SI joint fusion) is uncommon and reserved for carefully selected persistent cases, after specialist assessment and failure of appropriate nonsurgical care. Selection involves more than imaging and may include diagnostic injections. Diagnostic and therapeutic injections are sometimes used when the diagnosis is unclear or symptoms are severe, but they sit alongside, not instead of, structured rehabilitation.
The science
The Science of Sacroiliac (SI) Joint Dysfunction
SI-joint-related pain refers to pain thought to arise from the , between the sacrum and the pelvis (ilium), or from the ligaments around it. It can be difficult to tell apart from pain coming from the lower back or the hip, and routine examination does not reliably show that the pelvis is out of position. The joint normally allows only small amounts of movement (around 2 to 4 millimetres and 2 to 4 degrees) but plays an important role in transferring forces between your spine and legs.
The SI joint is surrounded by some of the strongest ligaments in the body, which can become either too loose (hypermobile) or too tight (hypomobile), both of which can cause pain and dysfunction. The joint surfaces are irregular and interlocking, designed more for stability than mobility, which makes them vulnerable to dysfunction when normal mechanics are disturbed.
Muscle function around the pelvis may contribute to SI joint problems. When muscles like the deep abdominals, , gluteus maximus, or latissimus dorsi don't function properly, it alters the force distribution across the joint and can lead to compensatory stress patterns.
The joint is richly innervated with pain receptors, which explains why SI dysfunction can be extremely painful. The pain pattern often involves the posterior pelvis but can refer to the groin, hip, thigh, and even down to the foot, making diagnosis challenging.
Contributing factors
Your functions as part of the closed that includes your , pelvis, and hip joints. Despite moving only a few millimetres and a few degrees, the SI joint must transmit substantial forces between your lower extremities and spine. During normal walking, ground reaction forces approaching 1.2 times body weight must transfer through the SI joint, while running can generate forces exceeding 2.5 times body weight through this relatively small articulation.
The joint's movement pattern involves complex coordinated motions of nutation (sacrum tilting forward) and counter-nutation (sacrum tilting backward) that must synchronize with hip and spine movements. During the loading phase of gait, the sacrum nutates slightly, creating tension in the long posterior SI ligaments and enhancing joint stability through the "self-bracing" mechanism. When this coordination is disrupted, whether through muscle dysfunction, pregnancy-related , or post-traumatic changes, abnormal stresses develop that exceed the joint's capacity to distribute loads evenly across its surfaces.
Form closure refers to the passive stability provided by the joint's irregular interlocking surfaces and surrounding ligamentous structures, while force closure describes the active stability created by muscular compression forces. Passive form closure alone provides only part of the required SI joint stability during functional activities, with the remainder coming from force closure generated by muscle activation. This explains why muscle weakness or inhibition frequently leads to SI joint pain even when the joint structure itself remains intact.
The posterior oblique sling, consisting of the latissimus dorsi and opposite gluteus maximus connected through the thoracolumbar , generates compressive forces across the SI joint during gait. EMG studies demonstrate that proper activation of this sling increases SI joint compression, enhancing stability through force closure. The anterior oblique sling (internal oblique and opposite muscles) provides similar stabilization, particularly during rotational activities. Research shows that individuals with SI joint dysfunction can demonstrate altered and reduced activation of these muscle slings compared to pain-free controls, highlighting the critical role of muscle coordination in maintaining joint health.
Leg length discrepancy, whether structural or functional, creates asymmetrical loading patterns that stress the SI joint. A leg length difference creates uneven loading between the limbs during walking, with larger discrepancies producing greater ground reaction force asymmetries. Over thousands of steps per day, this accumulated asymmetrical loading can lead to progressive SI joint dysfunction. The body attempts to compensate through pelvic rotation and lateral tilting, but these compensations often create secondary problems in the lumbar spine and hip joints.
Pregnancy represents a unique biomechanical challenge for the SI joint. Hormonal changes, particularly increased relaxin levels, cause increased laxity in the SI joint ligaments during the third trimester. Combined with the anterior shift in center of gravity from the growing fetus and an average weight gain of 11-16kg, this creates a perfect storm for SI joint dysfunction. Research indicates that pregnancy-related pelvic girdle pain, which involves the SI joints, is common during pregnancy, with the condition often persisting postpartum if proper rehabilitation doesn't restore force closure mechanisms.
Single-leg loading activities dramatically amplify SI joint stresses. When you stand on one leg, your pelvis wants to drop on the unsupported side, a movement that must be resisted by the and supported by SI joint stability mechanisms. Single-leg stance increases SI joint shear forces compared to double-leg standing. This explains why activities like climbing stairs, running, or simply standing on one leg to put on pants frequently reproduce SI joint pain in symptomatic individuals.
Asymmetrical movement patterns in sports create rotational forces that challenge SI joint stability. Sports involving asymmetrical loading, such as golf, tennis, baseball, and hockey, generate high rotational torques through the pelvis. In golfers, the lead-side SI joint (left side for right-handed golfers) is exposed to high rotational loading during the downswing phase. Without adequate force closure from the stabilizing muscle slings, these repetitive rotational forces can lead to progressive joint irritation and dysfunction.
Research
What the studies show
Trunk stability exercises, with or without a hands-on technique done while moving, reduced pain and disability in a small trial
In a 2024 randomised trial of 39 people with SI joint dysfunction (Yan et al., Frontiers in Physiology), both trunk (core) stability exercises alone and the same exercises combined with a hands-on technique done while the person moves (Mulligan mobilization with movement) reduced pain and disability over the treatment period. The combined group gained more on some measures of how far the trunk could move than the control group and the exercise-only group.
Supports exercise as the base of treatment, with hands-on mobilization as a possible add-on. The trial was small and had no mobilization-only group, so it cannot show which part made the difference.
Yan H, Zhao P, Guo X, Zhou X. The effects of Core Stability Exercises and Mulligan's mobilization with movement techniques on sacroiliac joint dysfunction. Front Physiol. 2024;15:1337754. PMID: 38699145.
Related Conditions
Conditions I commonly see alongside, or confused with, this one.
Getting back to it
Physiotherapy for sacroiliac (SI) joint dysfunction, built around the activity you want back.
