
IT Band Syndrome
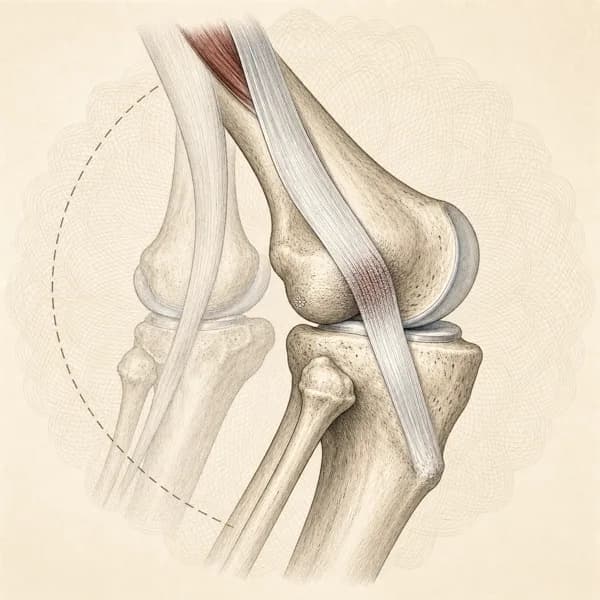
IT band syndrome commonly causes pain on the outside of the knee during running or cycling. The iliotibial band is a thick strip of tissue along the outer thigh. Pain may start after a certain distance or worsen downhill, but assessment is needed to distinguish it from other causes of outer-knee pain.
Key points
- What usually helps
- Strengthening the side of the hip, with changes to training and to how you run.
- What you can do now
- Run less, but keep running. Avoid downhills and sloped roads for now.
- How long it takes
- Some runners improve over several weeks; others need longer.
- When to see a doctor first
- Some signs need medical care the same day. Check the list before you start treatment.
Symptoms
Does this sound like you?
- Sharp pain on the outside of the knee
- Pain worse with running, especially downhill
- Pain that starts at about the same distance or time into a run
- Tenderness over the bony bump on the outside of the knee (the lateral femoral epicondyle)
- Pain when the knee is slightly bent, around 30 degrees
Often alongside it
- Hip tightness or pain
- A snapping feeling at the hip
- Other injuries from moving differently to protect the knee
- A change in the way you run
- Calf tightness
The pain comes on at a predictable point in a run. It is sharp and can force you to stop. It settles with rest but comes back with activity.
Before using this comparison, check when these symptoms need a doctor first.
When to see a doctor first
Get seen today
A hot, red, swollen knee or a fever
Same-day medical assessment to rule out infection
Pain that started with a fall or twist, or you cannot put weight on the leg
Possible fracture or ligament injury. Same-day medical assessment
Check with your doctor
Knee swelling, locking or giving way
Not typical of IT band syndrome. See your family doctor or a sports medicine physician to check for a meniscus or ligament injury
Numbness, tingling or weakness in the lower leg or foot
See your family doctor before starting physiotherapy to check the nerves and lower back
Treatment
How it is treated
Main approach. Strengthening the muscles on the side of the hip (abductors), together with changes to training and to how you run, can reduce pain and support a return to running. The research is limited, and recovery times vary.
Alongside it. Adjusting how much you run and taking slightly quicker steps (cadence) can reduce strain on the IT band, while other types of training (cross-training) keep up your running fitness.
Managing it over time. Regular hip strengthening and building up training gradually may help reduce the risk of IT band syndrome in recreational and competitive runners.
A typical rehabilitation progression
Three phases, from settling symptoms to returning to full activity.
Recovery from IT band syndrome is usually staged: calm the symptoms first, then rebuild the strength and capacity of the area, then return to your full activities. The phases below show how that can progress.
Phase 1Calm the Outer Knee and Build Hip Strength (Weeks 1 to 3)
Settle the irritation at the outer knee, adjust how much you run, and rebuild the hip muscles that move the leg out to the side and extend it ( and extensors). Fairclough's anatomy research showed the problem is squeezing (compression) rather than rubbing (friction), which matters because stretching the band itself adds little. The work happens at the hip and in how much you run.
Example exercises
- Side-lying hip abduction (lifting the top leg while lying on your side), 3 sets of 12 to 15 per side, keeping the pelvis still
- Clamshells with resistance band, 3 sets of 12 to 15 per side
- Glute bridge and single-leg bridge, 3 sets of 10 to 12
- Copenhagen side plank (with the top leg supported on a bench) or a side plank lifting the top leg, holding longer as you progress
- Running cut by roughly 50 percent, avoiding downhill routes and steeply sloped roads (cambers)
Possible progression milestones
Outer knee pain at or below 3 out of 10 during adjusted runs, daily walking and stairs without a flare-up, and completing the strength program 3 times a week for two weeks in a row.
Phase 2Loaded Hip Work and Running Form (Weeks 3 to 6)
Move from single-muscle exercises to loaded hip and single-leg exercises with the foot on the ground (closed-chain), and start working on running form. Noehren and colleagues (2014) and other research on syndrome support the view that hip strength tested without movement is not the whole picture: control during movement and resistance to tiring also matter, which is why the loading steps up here.
Example exercises
- Step-ups and step-downs, keeping the hip from dropping, 3 sets of 8 to 10 per side
- Split squat, or split squat with the back foot raised on a bench, 3 sets of 8 per side, adding load over time
- Single-leg Romanian deadlift (hinging forward at the hip on one leg), 3 sets of 8 per side
- Hip thrust or barbell glute bridge to strengthen the muscles that extend the hip, 3 sets of 8 to 10
- Taking slightly quicker steps on easy runs, 5 to 10 percent above your usual step rate (cadence)
Possible progression milestones
A pain-free single-leg squat and step-down with the hip and knee staying in line, increasing loads handled without a flare-up over the next 24 hours, and running a steady 30 minutes at an easy pace with pain 2 out of 10 or less.
Phase 3Return to Full Training and Terrain (Weeks 6 to 10+)
Rebuild how much you run and bring back hills, intervals and varied terrain. Relapses often happen in this phase when running jumps up too fast, so weekly increases are kept small, with about 10 percent as a rough guide rather than a fixed rule.
Example exercises
- Graded return-to-run progression, increasing running gradually and adjusting each step to symptoms and recovery, counting changes in speed, hills and terrain as well as distance
- Reintroduction of gentle downhill running, starting with short, mild gradients before longer or steeper sections
- Faster-paced interval work once easy running is consistently pain-free
- Continued hip strengthening twice weekly as maintenance
- Jumping and landing drills () and single-leg hops, 2 to 3 sets of 6 to 8, added where your sport or event needs them
Possible progression milestones
Back to your target weekly running with pain 2 out of 10 or less, downhill and faster running without symptoms returning, and a maintenance plan of 2 strength sessions a week that you can keep up.
What you can do now
- Run less, but keep running. Complete rest often feels good short term, but symptoms tend to return within the first few runs because nothing has changed in what the knee can handle. Cutting back how much you run, by roughly half at first, lets many runners keep running while rehab progresses.When you build back up, keep weekly increases small, with about 10 percent as a rough guide. Knee swelling, locking or giving way is not typical of IT band syndrome, so see your family doctor or a sports medicine physician to check for a meniscus or ligament injury.
- Avoid downhills and sloped roads for now. Downhill running bends the knee into the range where the tissue under the IT band is squeezed most, and asks more of the hip muscles. Leave out hard downhill running and steeply sloped roads (cambers) early on, and bring them back gradually once strength and running form are holding up.
- Strengthen the side of your hip. Exercises such as side-lying leg lifts, clamshells and bridges build the hip muscles that move the leg out to the side, turn it outward and extend it. Strengthening without adjusting training tends to stall, and adjusting training without strengthening tends to lead to relapse.
- Take slightly quicker steps. Taking slightly quicker steps, around 5 to 10 percent above your usual step rate (cadence), tends to shorten your stride and lower the peak load on the outside of the knee. It is a useful add-on rather than a fix on its own.
- Use foam rolling for comfort only. Rolling can feel good and may briefly reduce sensitivity, but it does not meaningfully lengthen the band. Spend most of your effort on hip strengthening and adjusting your running.
What I use in clinic
- Hip Strengthening. Strengthening the hip reduces strain on the IT band, with the focus on moving well. Weakness of the muscles on the side of the hip (abductors) is reported in a substantial proportion of cases, though findings across studies are mixed.
- Running Retraining. Changes to your step rate (cadence) and running form reduce strain on the IT band.
Recovery
How long it takes
Some runners improve over several weeks, while others need longer. Return to running and return to full training are separate milestones, guided by symptoms and tolerance.
It tends to come back if the factors behind it are not addressed.
What changes the timeline
- How long you have had symptoms
- How well training is adjusted
- How weak the hip muscles are
- How you run (running mechanics)
How I track it. I track how far you can run without pain, how your hip strength improves, and how you do on simple movement tests
Similar conditions
Conditions that can feel similar
- Lateral Meniscus Tear
- Tenderness along the joint line rather than near the bony bump on the outside of the knee (the lateral femoral epicondyle), catching or locking, and often a twist with weight on the leg. IT band syndrome does not cause true locking or swelling inside the joint (effusion).
- Patellofemoral Pain
- Pain around or behind the kneecap rather than on the outside of the knee, worse with stairs and long sitting. IT band pain sits on the outside, near the bony bump, and is brought on more reliably by how long you run than by sitting.
- Lateral Collateral Ligament Sprain
- An injury that forces the knee outward (varus), tenderness along the LCL rather than where the IT band attaches, and pain when the knee is pushed outward on testing. IT band syndrome typically has no sudden injury.
- Biceps Femoris Tendinopathy
- Tenderness where the outer hamstring attaches, at the top of the thin outer shin bone (the fibular head), rather than at the lateral epicondyle. Bending the knee against resistance is painful, and it is often brought on by sprinting or sudden acceleration rather than by steady running mileage.
- Proximal Tibiofibular Joint Dysfunction
- Pain at the top of the thin outer shin bone (the fibular head), possibly with clicking or a sense of instability, often after a twisting fall or impact. Moving the top of that bone by hand brings on the pain, which is not a feature of IT band syndrome.
- Referred Pain from the Lumbar Spine
- Pain on the outside of the thigh or knee, with a history of back symptoms. Moving the spine brings it on, and it is not clearly linked to load the way running-related IT band pain is. A brief check of the spine is worth doing whenever outer knee pain does not fit the usual pattern.
Questions
What patients ask me most
Is foam rolling the IT band actually useful?
The premise is dated. Fairclough and colleagues' anatomical work (Journal of Anatomy 2006, Journal of Science and Medicine in Sport 2007) showed the IT band is a thickened part of the sheet of tissue that wraps the thigh (the fascia lata), firmly attached along the thigh bone. It is not a rope that slides back and forth over the bony bump at the knee (the epicondyle), so the classic 'friction' explanation does not hold. Rolling can feel good and may briefly reduce sensitivity, but it does not meaningfully lengthen the band. Strengthening the hip and adjusting how much you run is where the real change happens.
Why does my ITB hurt at a predictable distance into a run?
It is a problem of load over time. The muscles on the side of the hip (abductors) tire over a long run, control of the pelvis drifts, and the tissue on the outside of the knee under the IT band gets squeezed more and more. Pain often shows up at a consistent distance because that is when capacity runs out. Noehren and colleagues (JOSPT 2014) found the picture is not always simple hip weakness when strength is tested without movement, but how well the muscles resist tiring and how you run still matter clinically.
Should I stop running entirely?
Not usually. Complete rest often feels good short-term, then symptoms return within the first few runs because nothing has changed in what the knee can handle or how you run. The usual approach is running less, avoiding downhill running and steeply sloped roads (cambers) early on, and pairing adjusted running with a structured hip and trunk strengthening program. Many runners can keep running at reduced load while rehab progresses.
How long does ITB syndrome take to resolve?
Some runners improve over several weeks when hip strengthening, load management, and running-form work are addressed together, while others need longer. Getting back to running and getting back to full training are separate milestones, both guided by symptoms and tolerance. Rest alone often does not settle it for long, and symptoms that have been present for a long time can take longer to settle.
Does cadence actually help IT band pain?
Sometimes. Taking slightly quicker steps, around 5 to 10 percent above your usual step rate (cadence), tends to shorten your stride, reduce how much you bounce up and down, and lower the peak load on the outside of the knee. It is a useful add-on rather than a fix on its own. Mucha and colleagues' 2017 review of risk factors in runners and Louw's 2014 biomechanical review both point to running mechanics as one of several contributors worth addressing.
Does ITB syndrome need imaging or injections?
Usually not. The diagnosis is made from your history and an examination: pain on the outside of the knee brought on by single-leg tasks with weight on the leg or by longer runs, tenderness near the bony bump on the outside of the knee, and a recognisable pattern in your training history. Imaging is considered when the story does not fit, when pain is not settling with a well-built program, or when a meniscus problem or a problem in the outer half of the knee joint is suspected. Injections are not a first-choice treatment.
Can strength work alone fix ITB syndrome?
Often, when combined with load management. The hip muscles that move the leg out to the side, turn it outward and extend it usually need work, and so do how much you run and how much of it is on hills. Patients who do strengthening without adjusting training tend to stall, and those who adjust training without strengthening tend to relapse.
Why is downhill running so much worse?
Downhill running increases knee bending in the 20 to 30 degree range, where the tissues under the IT band are squeezed most against the bony bump on the outside of the knee. It also asks more of the hip muscles, which have to control the movement while lengthening (eccentric control). That combination is why steep descents often flare symptoms. Early rehab usually avoids hard downhill work and reintroduces it gradually once strength and running form are holding up.
The science
The Science of IT Band Syndrome
IT band syndrome involves irritation where the crosses the lateral knee. It's not friction but compression of sensitive fat pad beneath the band. Contributing factors include hip weakness, training errors, and biomechanical issues.
Contributing factors
syndrome is felt at the knee, but hip control may play a part. When the pelvis drops on one side during single-leg activities, the thigh angles inward (), which can increase tension in the IT band and compress the sensitive tissue underneath it at the knee. Hip weakness and running differences seen in people with ITB pain do not prove they caused it, but they are things rehab can work on.
Running mechanics play a huge role in developing IT band syndrome. Overstriding (landing with your foot too far in front of your body), excessive crossover gait (feet landing across the midline), and running with too much vertical oscillation all increase IT band tension. Downhill running is particularly problematic because it encourages longer stride lengths and places greater demands on your hip stabilizers. When your hip muscles fatigue, your running form deteriorates, creating even more IT band stress.
Training errors compound the biomechanical issues. Sudden increases in mileage, running primarily on cambered roads (which creates uneven leg lengths), or consistently running in the same direction on tracks forces your body to adapt to asymmetric loading patterns. Tight hip flexors from prolonged sitting limit hip extension during running, forcing your IT band to work harder to stabilize your pelvis. Even factors like leg length differences or old ankle injuries can alter your gait pattern enough to overload one IT band. The IT band itself is rarely the whole problem; it is often responding to how the hip above controls the leg.
Research
What the studies show
Hip muscle weakness and hip strengthening in distance runners with IT band syndrome
In a small study of 24 distance runners with IT band syndrome, with no comparison group, a 6-week program strengthening the muscle on the side of the hip (gluteus medius) left 22 of 24 pain-free and able to return to running, with no return of symptoms at 6 months.
Supports hip-focused rehabilitation.
Fredericson M, Cookingham CL, Chaudhari AM, et al. (2000). Hip abductor weakness in distance runners with iliotibial band syndrome. Clin J Sport Med. PMID: 10959926.
Guides on knee pain
Longer explanations of symptoms and scan-report wording.
- Pain Right Below the KneecapA single tender spot below the kneecap that flares with jumping, stairs, or deep squats. Most commonly patellar tendinopathy in active adults, and growth-plate conditions in young athletes.
- Suprapatellar Effusion (Fluid on the Knee)Extra fluid inside the knee joint, seen in the pouch above the kneecap. What the size words on a report mean, the usual causes by how quickly the swelling came on, and when to see a doctor first.
- Joint Space Narrowing in the KneeThe gap between the bones looks thinner than expected on an X-ray. What medial, tricompartmental and the severity words mean, how it relates to pain, and what the guidelines recommend.
Related Conditions
Conditions I commonly see alongside, or confused with, this one.
Lateral Hip Pain & Gluteal Tendinopathy
Both involve lateral hip/thigh structures; IT band connects to trochanteric region
Shin Splints
Both are common running injuries with overlapping biomechanical causes
Ankle Sprains
Ankle instability can alter lower limb mechanics contributing to IT band stress
Plantar Fasciitis & Heel Spurs
Both involve lower limb overuse; foot dysfunction can affect IT band mechanics
ACL Injuries
Getting back to it
Physiotherapy for IT band syndrome, built around the activity you want back.
