
Golfer's Elbow
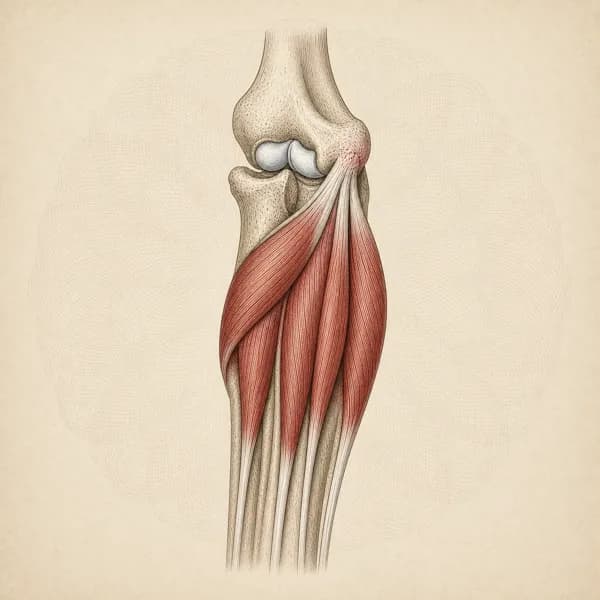
Golfer's elbow (medial epicondylalgia) is pain on the inner side of the elbow, where the tendons that bend the wrist and turn the forearm attach to the bone. It is often linked to repeated gripping, lifting or work tasks, and does not require playing golf. Gripping, carrying and opening jars often hurt.
Key points
- What usually helps
- Strengthening the muscles that bend the wrist, built up gradually. The evidence is more limited than for tennis elbow.
- What you can do now
- Find the grip you do not notice. Use thicker handles and a whole-hand grip.
- How long it takes
- Many people notice change over a few months; longer-standing cases take longer.
- When to see a doctor first
- Some signs need medical care the same day. Check the list before you start treatment.
Symptoms
Does this sound like you?
- Pain and tenderness over the bony bump on the inner elbow (the medial epicondyle)
- A weaker grip, especially when bending the wrist forward or turning the palm down
- Pain when you bend the wrist forward, or turn the palm down, against resistance
- Pain during gripping activities (handshake, carrying objects, opening jars)
- Difficulty with tasks that bend the wrist forward (typing, lifting, using tools)
Often alongside it
- Aching and tiredness in the muscles on the palm side of the forearm
- Occasional numbness or tingling in the ring and little fingers (from the ulnar nerve)
- Neck and shoulder tension from using the arm differently
- Morning stiffness in elbow and forearm
- Difficulty with daily tasks requiring forceful gripping (turning keys, wringing towels)
It comes on gradually over weeks to months. Pain is typically worse with gripping, lifting and bending the wrist forward. It often improves with rest but quickly returns when activity starts again. Morning stiffness is common, and the grip may feel weak or give way.
Before using this comparison, check when these symptoms need a doctor first.
When to see a doctor first
Get seen today
Severe swelling, deformity, or pain that started with a fall or a single forceful movement
Go to emergency or urgent care to rule out a fracture, ligament rupture, or tendon tear
Check with your doctor
Numbness or weakness in the ring and little fingers that keeps getting worse
See your family doctor promptly to check the ulnar nerve; nerve testing or a surgical opinion may be needed
The elbow feels unstable or gives way, especially when throwing
See your family doctor, who can arrange imaging and a specialist opinion for a ligament injury
No improvement or progressive worsening despite 3 months of appropriate treatment
I flag it to your family doctor, who can arrange imaging or a specialist opinion and discuss other options
Severe night pain or pain at rest unrelated to activity
See your family doctor before starting physiotherapy, to rule out inflammatory arthritis, infection, or another cause
Treatment
How it is treated
Main approach. Strengthening exercises for the muscles that bend the wrist and turn the palm down (the wrist flexors and pronators), built up gradually and including slow lowering work (eccentric exercise), may reduce pain and improve function, especially alongside managing how much load the arm takes. The evidence for golfer's elbow is limited and less certain than for tennis elbow.
Alongside it. Hands-on treatment (manual therapy), such as soft tissue work and joint mobilization, can give short-term pain relief when combined with exercise. Adjusting work and grip habits helps limit flare-ups during rehab.
Managing it over time. Looking at your work set-up and changing how you grip can reduce the risk by lowering the load on the tendon. Forearm strengthening, built up over time, keeps the tendon able to handle the demands of work and sport.
A typical rehabilitation progression
Three phases, from settling symptoms to returning to full activity.
Recovery from golfer's elbow is usually staged: calm the symptoms first, then rebuild the strength and capacity of the area, then return to your full activities. The phases below show how that can progress.
Phase 1Calm the Tendon and Begin Loading (Weeks 1 to 3)
Settle the worst of the irritation, start loading at a level the tendon can tolerate, and fix any workstation problems or sudden jumps in training that set this off. Holding the muscle tight without moving the wrist ( exercise) is useful for pain relief and as a safe starting load. Reviewing your daily activities comes first: whatever repeatedly loaded the tendon on the inner elbow (the flexor-pronator tendon) has to change, at least for a while, for the strengthening to have a chance.
Example exercises
- Wrist flexion holds without moving (isometric): forearm supported, elbow bent to 90 degrees, bending the wrist forward against a light weight or band, 5 sets of 30 to 45 seconds, at pain no higher than 3 out of 10
- Holds turning the palm down against a fixed object or band without moving (isometric ), 5 sets of 20 to 30 seconds
- Gentle stretch for the muscles on the back of the forearm (wrist extensor stretch), 3 holds of 30 seconds, to balance out the program
- Grip squeezes with a soft ball at less than full effort, 3 sets of 10, without bending the wrist fully forward while gripping
- Shoulder blade and setting with a light band, 3 sets of 10, so the elbow and forearm do less extra work during reaching and lifting
Possible progression milestones
Possible milestones, adapted to the person rather than treated as fixed cut-offs: the wrist holds feel comfortable, no more than mild next-day soreness after sessions over several days in a row, and everyday gripping tasks such as carrying groceries or using a kettle no longer provoking sharp pain on the inner elbow.
Phase 2Building Up the Inner Forearm Muscles (Weeks 3 to 8)
Build the tendon's tolerance with heavier, slower exercises for the muscles that bend the wrist and turn the palm down (the flexor-pronator group). The evidence for golfer's elbow is less specific than for tennis elbow, but the general principles for tendon problems carry over: slow movements, load that builds up gradually, and respect for the 24-hour symptom rule. Some discomfort during these exercises, up to 5 out of 10, is acceptable provided it settles within 24 hours.
Example exercises
- Heavy slow resistance wrist curls with a dumbbell (bending the wrist forward), forearm supported palm up, 3 seconds up and 3 seconds down, 3 sets of 10 to 15, 3 times per week
- Slow lowering wrist curls (): the other hand helps with the lift, then the sore side lowers slowly over 4 seconds, 3 sets of 10
- Turning the palm down against resistance (pronation) with a hammer or weighted lever, 3 sets of 10 to 12 per side
- Farmer and suitcase carries with a moderate load, 3 rounds of 20 to 40 metres, to build how long you can hold a grip without very high peak force
- Continued shoulder blade work and strengthening for the back of the body (posterior chain), 3 sets of 10 to 12, so the forearm is not overloaded during lifting
Possible progression milestones
Possible milestones, adapted to the person rather than treated as fixed cut-offs: pain-free grip closer to the unaffected side, heavy slow resistance sessions completed without a 24-hour flare over several weeks, and scores on an elbow pain and function questionnaire (PREE) falling from where they started.
Phase 3Return to Full Sport, Work, and Heavier Loading (Weeks 8 to 16+)
Rebuild tolerance for the actual demands that caused the problem. For desk workers that is long spells of gripping, mouse and keyboard time. For trades and gym users that is tool use, repeated lifting, carrying and overhead work. For golfers and throwers it is a step-by-step return with an honest look at grip size, technique and training volume.
Example exercises
- Wrist curls and palm-down turning through the full range, at close to the heaviest resistance you can tolerate, 3 sets of 8 to 10
- Multi-joint pulling and pressing exercises, such as rows, deadlifts and chin-ups spread across the week, with attention to how long you can hold a grip
- Sport-specific return: for golfers, graded practice (chipping, half-swings, then full swings) before returning to 18 holes; for throwers, a progressive throwing program
- Practising your work tasks at a realistic length and load, with short breaks planned in
- Keep-up strengthening 1 to 2 times per week once back to full duties, to maintain tolerance for the tasks you return to
Possible progression milestones
Possible milestones, adapted to the person rather than treated as fixed cut-offs: low pain during full work or sport demands, grip strength close to the other side, and a sustained return to full duties without a 24-hour symptom flare.
What you can do now
- Find the grip you do not notice. A big contributor is often quiet and constant: the forearm turned in and gripping for hours, such as a phone held at its bottom edge, the steering wheel, the mouse, a dog leash wound tight, or a toddler carried on one hip. Spot these through your day and use only as much grip force as each task needs.
- Use thicker handles and a whole-hand grip. Thicker handles spread pressure over a larger area, and gripping with the whole hand puts less stress on one spot than pinching with the fingertips. Choosing or adapting tools also reduces how hard you need to grip.Make changes gradually, and watch for the wrist or shoulder taking over the work.
- Start with wrist holds. With the forearm supported and the elbow bent to 90 degrees, bend the wrist forward against a light weight or band without letting it move, and hold for 30 to 45 seconds, 5 times. Holding still like this (isometric exercise) is useful for pain relief and as a safe starting load.Keep the pain during the holds at 3 out of 10 or less.
- Add slow lowering curls next. Once the holds feel comfortable, lower a light weight slowly over 3 to 4 seconds and use your other hand to help lift it back up (eccentric exercise). Evidence specific to golfer's elbow is limited, so these sit within a broader strengthening program that builds up gradually.Mild discomfort during the exercise, 3 to 4 out of 10, is acceptable. Sharp pain, or symptoms lasting beyond 24 hours, means the load was too much, so reduce the weight.
- Keep the arm working, but trim the peaks. Complete rest does not usually build the tendon's tolerance, and symptoms often come back when people take weeks off and then return to full activity. Spread heavy tasks through the week and check the elbow 24 hours later; a temporary rise that settles within 24 hours is acceptable.Progress is often uneven, and a flare does not mean you have undone anything, so adjust the load rather than stopping. Pins and needles or numbness in the ring and little fingers is a different signal (the ulnar nerve rather than the tendon), so get it assessed rather than working through it, and see your family doctor promptly if it keeps getting worse.
What I use in clinic
- Slow lowering exercises (eccentric strengthening). The evidence is low in certainty: a 2026 review found five small studies in which pain and function improved with slow lowering exercise, with an advantage over a comparison treatment in only one trial (See et al., 2026).
- Hands-on treatment (manual therapy). Some evidence for short-term pain relief when combined with exercise. Includes gentle elbow and wrist joint movement (mobilization) and soft tissue work for the inner forearm muscles (the flexor-pronator group).
- Activity and load changes. An essential part of care, supported by clinical consensus and biomechanical research; the practical steps are under What you can do now.
- Dry Needling. Emerging evidence for pain relief and better function when needling tender, irritable spots (active trigger points) in the inner forearm muscles, matched to where the pain spreads.
- Ongoing strength training. Continuing to build strength after the early phase can improve load tolerance for work and sport; evidence on preventing recurrence is limited.
- Education. Understanding the condition and how much activity to do can help people stay with a strengthening program and feel confident using the arm.
Recovery
How long it takes
Many people notice meaningful change over a few months of structured strengthening, although the evidence specific to golfer's elbow is limited and timelines vary. Longer-standing cases tend to take longer.
Many cases settle over time. In a study of workers followed for about three years, most had recovered (Descatha et al., 2003), but symptoms can linger for many months, and a structured program aims to shorten that time.
What changes the timeline
- How long you have had symptoms (longer is linked with slower recovery and a higher chance of it becoming long-standing)
- How much tendon change a scan shows (more severe changes need longer rehab)
- The demands of your job, and whether you can adjust aggravating tasks while you recover
- Sticking with the strengthening program (something you can control)
- Symptoms from the ulnar nerve (tingling or numbness in the ring and little fingers) or a neck problem at the same time (these need treating too)
- Grip and forearm strength at the start (weaker is linked with a longer recovery)
- Worry and stress, including fear of movement (kinesiophobia), expecting the worst about the pain (catastrophizing), and stress at work
- Earlier treatments that did not work, or several cortisone (corticosteroid) injections (may point to a more complex case)
How I track it. I measure grip strength with a grip meter (dynamometer), comparing both sides. I check your pain with specific tests, such as bending the wrist forward or turning the palm down against resistance, and track the key activities that were hard at the start. Tracking your pain during and 24 hours after specific tasks guides how fast the load goes up
Similar conditions
Conditions that can feel similar
- Ulnar Nerve Compression at the Cubital Tunnel
- Numbness or tingling into the ring and little fingers rather than one tender spot at the elbow, worse when the elbow stays bent (holding a phone, sleeping). Tapping over the nerve at the inner elbow sets off tingling (Tinel sign), or holding the elbow fully bent brings on symptoms (elbow flexion test). In more severe cases the small hand muscles are weak.
- Ulnar Collateral Ligament Sprain
- Pain and looseness when the inner elbow is stressed by pushing the forearm outward (valgus stress test), a history of throwing or a specific injury, and a sense of instability when throwing or loading the arm overhead. It often comes with a strain of the inner forearm muscles, rather than a tendon problem on its own.
- Cervical Radiculopathy (C7 or C8)
- Pain mainly in the neck that spreads into the arm along the strip of skin one nerve root supplies (a dermatome). Turning and tilting the head toward the sore side with gentle downward pressure brings on the arm symptoms (Spurling's test), and any numbness or weakness follows that nerve root rather than staying around the inner elbow.
- Medial Epicondyle Avulsion or Stress Reaction
- Comes on suddenly with a specific throw or pull, with tenderness at one spot on the bone rather than the tendon. It is more common in teenage throwers whose growth plates are still open, and the changes show on X-ray or MRI.
- Pronator Syndrome (Median Nerve Compression in the Forearm)
- Aching along the upper forearm on the palm side rather than over the bony bump on the inner elbow. Turning the palm down against resistance brings on the symptoms, and there is tingling (paresthesia) in the area the median nerve supplies, including the skin of the palm (the palmar cutaneous branch).
- Referred Pain from Cervical Facet or Rotator Cuff
- A spread-out ache without one tender point at the inner elbow. Tests of the shoulder or neck bring on the symptoms, while loading the wrist into bending or palm-down turning does not, and symptoms do not clearly follow gripping.
Commonly confused with
Side-by-side comparisons for patterns that often get mistaken for golfer's elbow.
Questions
What patients ask me most
Is golfer's elbow actually caused by golf?
Usually not. Many cases arise outside golf, often linked to repetitive work tasks, lifting, or gym training. Golfers can develop it, but carrying, gripping, climbing, trades work, or a sudden gym or yard work spike are more common links.
Is golfer's elbow the same as tennis elbow?
No. They are similar in principle (both are load-related tendon problems at the elbow), but they affect opposite sides. Golfer's elbow involves the shared tendon on the inner elbow of the muscles that bend the wrist and turn the palm down (the flexor-pronator tendon). Tennis elbow involves the shared tendon on the outer elbow of the muscles that lift the back of the hand (the extensor tendon). The rehab principle is the same, progressive loading over months, but the specific exercises differ, and so do the tests used during assessment.
How long does golfer's elbow take to heal?
The honest answer is that the evidence base for golfer's elbow (medial epicondylalgia) is weaker than for tennis elbow, with fewer high-quality trials. Going by the wider tendinopathy literature, many people see meaningful change over a few months of structured loading, although timelines vary. Longer symptom duration has been linked to slower recovery, so people who have had symptoms for over a year may need a longer program.
Should I rest my elbow completely?
Complete rest does not usually build the tendon's tolerance. Reducing aggravating peaks while continuing gentle, structured loading is how I work on tendon capacity. When people take weeks off and then return to full activity, symptoms often come back soon after, because the tendon's capacity has not changed.
Should I get a cortisone shot for golfer's elbow?
I am cautious about it. In trials on the outer elbow (tennis elbow), including Coombes and colleagues' JAMA 2013 trial, corticosteroid injection helped in the short term but was linked to worse outcomes at one year and more recurrence. Golfer's elbow has less high-quality data than tennis elbow, so that evidence may not transfer exactly, but I apply the same caution. Injection is a conversation for a physician, usually when pain is stopping someone from doing the loading rehab, rather than a first-line fix.
Why do my ring and small fingers feel numb too?
The ulnar nerve runs right behind the medial epicondyle, and some people with golfer's elbow also have ulnar nerve irritation alongside it. If you are getting numbness or tingling into the ring and small fingers, I specifically test the nerve where it passes the inner elbow (the cubital tunnel) and check whether the ulnar nerve is involved, because that changes the plan. If nerve symptoms dominate, rehab focuses on nerve gliding (nerve mobilisation) and positioning, not just the tendon.
When can I go back to lifting weights or golf?
Once you can tolerate full-range loading under moderate resistance without a 24-hour flare, and grip strength is close to your unaffected side. For golf, that also means reviewing whether grip size, swing mechanics, or a recent change in practice volume contributed to the original flare. Returning to the exact conditions that caused the problem without changing them is a common reason symptoms recur.
Do I need an MRI for golfer's elbow?
Usually not. The diagnosis is made from the examination: tenderness at one spot on the bony bump of the inner elbow, pain when bending the wrist forward or turning the palm down against resistance, and a history of repetitive load. When symptoms do not respond to an appropriate 3-month loading program, when there is a specific concern about the ligament on the inner side of the elbow (the ulnar collateral ligament) in a thrower, or when nerve involvement is significant, I flag it to your family doctor or specialist and refer you for imaging.
The science
The Science of Golfer's Elbow
Medial (golfer's elbow) is a affecting the common flexor-pronator tendon origin at the of the humerus, primarily involving the pronator teres and flexor carpi radialis tendons. Despite the name, only a small share of cases occur in golfers. The condition represents a failed healing response resulting in tendinosis rather than , characterized by angiofibroblastic degeneration, disorganized structure, increased mucoid ground substance, and .
The pathophysiological process begins with repetitive mechanical overload of the wrist flexors and forearm pronators exceeding the tendon's capacity for adaptation and repair. This creates microtears in the tendon structure that accumulate faster than the tissue can heal. The body's attempt to repair this damage results in disorganized collagen deposition, increased vascularity with neurogenic ingrowth, and eventual structural weakening rather than strengthening. Histologically, biopsies show angiofibroblastic hyperplasia with absence of inflammatory cells, confirming this as degenerative tendinosis rather than acute inflammation.
The flexor-pronator mass originates from a relatively small area on the medial epicondyle and must generate force during gripping, wrist flexion, and forearm , functions required in countless daily activities. The pronator teres and flexor carpi radialis experience the highest loads during gripping activities combined with forearm rotation, making them particularly vulnerable to overload. The medial epicondyle also serves as an attachment site for the ulnar , meaning any stress at the elbow can indirectly stress the flexor-pronator origin.
Neurogenic develops in chronic cases, with elevated substance P and calcitonin gene-related peptide contributing to pain amplification. This neuroplastic change helps explain why some cases become recalcitrant to standard treatment approaches. The condition frequently coexists with symptoms due to the nerve's proximity to the medial epicondyle, syndrome, and , requiring careful differential diagnosis.
Risk factors include age 40-60 years (peak incidence), occupations requiring forceful gripping with wrist flexion (construction, cooking, assembly work, manual labor), racquet sports with poor technique, overhead throwing sports, and sudden increases in hand-intensive activities. Biomechanical factors such as reduced grip strength, poor proximal stability, and cervical dysfunction contribute to onset and chronicity.
Contributing factors
The biomechanical drivers of golfer's elbow center on repetitive and of the wrist flexors and forearm pronators during gripping and rotational tasks. When you grip an object forcefully while simultaneously flexing your wrist or rotating your forearm inward (), high tensile stress concentrates at the . This loading pattern occurs during the golf downswing (hence the name), but more commonly during occupational and daily activities.
Computer work may add some load for some people. Typing with the wrists propped in a bent position keeps the flexor muscles working at a low level, and mouse use with the forearm turned palm-down adds some pronation load. This is a plausible loading mechanism rather than proof that ordinary computer work damages the tendon; many people type all day without elbow pain, and how a tendon responds depends on total load, recovery, and general health.
Manual labor and tool use create even more extreme loading scenarios. Using a hammer requires forceful gripping combined with rapid eccentric loading during impact deceleration. The flexor-pronator muscles must stabilize the wrist against the vibration and torque generated with each strike. Screwdriver use, particularly when driving screws into hard materials, combines sustained maximal grip force with repetitive pronation-supination torque. Carrying heavy objects with handles (shopping bags, buckets, toolboxes) places sustained isometric load on the flexors, especially when the load is held away from the body with the elbow extended.
Golf technique can add load. During the downswing, the lead arm (left for right-handed golfers) must generate both club speed and control. Poor technique that creates excessive wrist flexion at impact, early release of the wrist angle before ball contact, or hitting behind the ball repeatedly creates explosive eccentric loading on the flexor-pronator mass. Gripping too tightly throughout the swing prevents necessary relaxation phases. The trailing arm is also vulnerable during the follow-through if the golfer pulls across the body with excessive forearm rotation.
Throwing mechanics in baseball and softball create similar stresses. During the acceleration phase of throwing, the medial elbow experiences high stress that loads both the ulnar and flexor-pronator mass. The flexors must eccentrically control the elbow extension velocity while the forearm pronates to impart spin on the ball. This is why medial elbow pain in overhead athletes often represents a complex of including UCL strain, flexor-pronator , and potential irritation.
Racquet sports, particularly tennis serves and overhead strokes, create wrist flexion torque at ball contact that must be controlled by the flexor-pronator group. Poor technique that relies on wrist action rather than trunk rotation significantly overloads these structures. Single-handed backhands with late contact point create similar medial elbow demands.
What happens further up the arm may add to the load at the elbow. Weak scapular stabilizers can lead to compensatory wrist and forearm muscle activation during reaching and lifting tasks. Limited rotation causes the forearm to generate movement that should originate from the trunk. Reduced shoulder internal rotation range, common in throwing athletes and manual laborers, increases the pronation demands on the forearm during rotational tasks. Even dysfunction can alter motor control patterns of the forearm musculature through neural mechanisms, contributing to overload.
Grip size and tool design significantly influence loading magnitude. Smaller diameter handles (thin golf club grips, undersized tool handles) require higher muscle activation to maintain grip security compared to larger diameter grips that distribute pressure across more surface area. Tool weight and balance affect the moment arm and force requirements at the medial epicondyle. Ergonomic modifications such as padded handles, proper grip sizing, and power-assisted tools reduce sustained muscle activation demands.
Research
What the studies show
Slow lowering exercise may reduce pain and improve function in golfer's elbow, but the evidence is limited
A review of slow lowering (eccentric) exercise for golfer's elbow (See, Loo and Jaafar, Complementary Therapies in Medicine, 2026) found five studies with 143 patients in total. Pain and function improved in the people doing the exercise, but it did better than a comparison treatment in only one randomised trial, and the authors rated the overall certainty of the evidence as low.
Slow lowering exercise is a reasonable part of a broader strengthening program, but no single exercise plan has been shown to be better than the others for golfer's elbow.
See ZH, Loo CE, Jaafar Z (2026). Eccentric exercise therapy for medial epicondylitis: A systematic review of clinical outcomes. Complement Ther Med. PMID: 41887339.
In tennis elbow, cortisone injections gave short-term relief but worse results at one year and more recurrences
A randomised trial of cortisone (corticosteroid) injection, physiotherapy, or both for elbow tendon pain (Coombes, Bisset, Brooks, Khan and Vicenzino, JAMA, 2013) found that the injection improved short-term results, but clearly fewer people had fully recovered, and more had a recurrence, at one year than with a placebo injection. This trial studied tennis elbow, on the outer side. Good-quality evidence for golfer's elbow is sparser, but the same pattern of short-term benefit and a worse long-term result is generally applied, with caution, to the inner side.
Injections can give short-term relief, but in tennis elbow they did not improve one-year outcomes. If one is considered, it belongs alongside a loading program, not in place of it.
Coombes BK, Bisset L, Brooks P, et al. (2013). Effect of corticosteroid injection, physiotherapy, or both on clinical outcomes in patients with unilateral lateral epicondylalgia: a randomized controlled trial. JAMA. PMID: 23385272.
Related Conditions
Conditions I commonly see alongside, or confused with, this one.
Tennis Elbow
Both are elbow tendinopathies affecting opposite epicondyles
Repetitive Strain Injuries
Medial epicondylitis is a repetitive strain injury from overuse
Carpal Tunnel Syndrome
Both involve median nerve pathway; wrist flexor tension can contribute to carpal tunnel
Thoracic Outlet Syndrome
Both can cause medial arm/forearm symptoms and nerve-related pain
De Quervain's Tenosynovitis
Both involve overuse of wrist and forearm muscles from similar activities
Wrist Sprains & Strains
Getting back to it
Physiotherapy for golfer's elbow, built around the activity you want back.
