
Shoulder Impingement Syndrome
Shoulder impingement, often called subacromial pain syndrome, describes pain commonly linked to the rotator cuff tendons and nearby bursa. Lifting the arm, reaching overhead and lying on that side often hurt. The name does not establish that bone is pinching a tendon, and symptoms overlap with other shoulder problems.
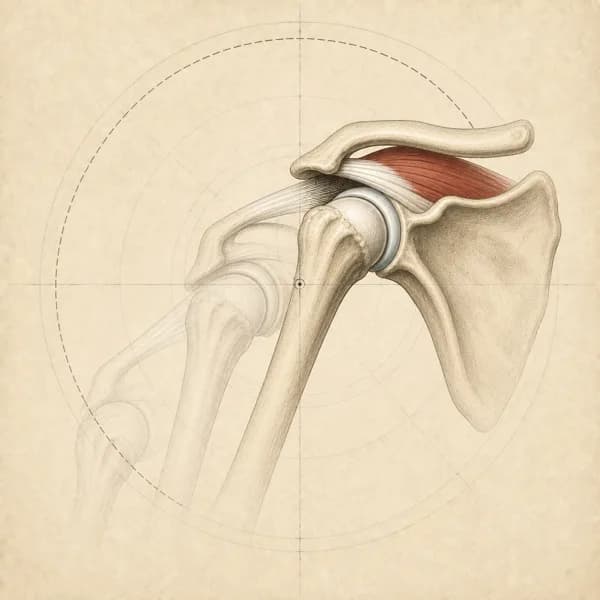
Key points
- What usually helps
- Strengthening the rotator cuff and shoulder blade muscles. Surgery to make more space did no better than placebo surgery.
- What you can do now
- Support the arm at night. Start with static holds.
- How long it takes
- Substantial progress by 6 to 8 weeks for many, and most improve over 3 to 6 months.
- When to see a doctor first
- Some signs need emergency care. Check the list before you start treatment.
Symptoms
Does this sound like you?
- Pain with overhead activities
- Pain through the middle range as you lift the arm out to the side (a painful arc, about 60 to 120 degrees)
- Night pain
- Weakness lifting the arm
- Pain reaching behind your back
Often alongside it
- Neck pain
- Clicking sensations
- Stiffness that builds over time
- Moving differently to work around the pain
- Difficulty with daily tasks
Pain comes with particular positions rather than being constant. Overhead activities are hard.
Before using this comparison, check when these symptoms need a doctor first.
When to see a doctor first
Go to emergency
Shoulder or arm pain with chest pain, shortness of breath, sweating or nausea, or pain that comes on with exertion and eases with rest
Call 911. Heart problems can show up as shoulder pain
A hot, red, swollen shoulder, or shoulder pain with fever or feeling unwell
Go to emergency now
Get seen today
A fall or blow followed by severe pain or a change in the shape of the shoulder
Same-day medical assessment to rule out a fracture or dislocation
Check with your doctor
Sudden weakness after an injury, so you cannot lift the arm
See your family doctor within a few days. An early imaging and surgical opinion matters for a fresh tear
Shoulder pain with a history of cancer, unexplained weight loss, or constant pain at night that does not ease with position
See your family doctor before starting physiotherapy
Treatment
How it is treated
Main approach. A structured exercise program that strengthens the rotator cuff and improves shoulder blade control is the first treatment to try. In a large trial (CSAW, Beard and colleagues, 2018), surgery to shave bone and make more space (decompression) did no better than placebo surgery for this kind of pain, so it is not a first option.
Alongside it. Joint mobilization and, through your doctor, a steroid (corticosteroid) injection may give short-term relief while the exercise program builds up what the shoulder can handle.
Managing it over time. Keeping up cuff and shoulder blade strengthening, and building overhead load gradually, may lower the chance of a flare.
A typical rehabilitation progression
Three phases, from settling symptoms to returning to full activity.
Recovery from shoulder impingement syndrome is usually staged: calm the symptoms first, then rebuild the strength and capacity of the area, then return to your full activities. The phases below show how that can progress.
Phase 1Settle and Reload
Take the edge off symptoms, protect sleep, and bring back load in a way the cuff tolerates. A static hold, where the muscle works without the arm moving (an ), can be a manageable way to begin when movement is painful. It eases pain for some people, but not consistently, so I choose the effort and hold time by your response and use another option if it aggravates symptoms. The 2022 clinical guideline for problems (Lafrance and colleagues) recommends active rehabilitation built around everyday tasks over treatments done to you (passive treatments) or rest.
Example exercises
- Static hold turning the arm outward (isometric external rotation), elbow at your side, pressing into a wall or doorframe: 30 to 45 seconds at a moderate, comfortable effort, 4 to 5 repetitions daily
- Static holds pressing the arm out to the side () and turning it inward (internal rotation) at the same effort, stopping before any sharp pain
- Low-row holds and shoulder blade squeeze holds with a band (drawing the shoulder blades back), to get the muscles at the back of the shoulder working again
- Moving the arm yourself within a pain-free range, such as table slides (sliding the hand along a table), wall walks (walking the fingers up a wall) and pendulum swings (letting the arm hang and swing gently), to keep the shoulder moving without a flare
- Activity review: finding the particular overhead tasks, or positions at the end of your reach, that set off flare-ups, and changing them for now
Possible progression milestones
Night pain manageable on most nights, low pain at rest, and the static holds feeling comfortable without a flare that lasts into the next day.
Phase 2Build Cuff and Scapular Capacity
Move from settling pain to real strength work. In a 2024 review (Zhong and colleagues), shoulder blade exercises were linked with slightly better pain and disability scores than standard physiotherapy for this kind of shoulder pain, and an earlier review of 16 trials (Hanratty and colleagues, 2012) found exercise helped pain and function in the short term.
Example exercises
- Turning the arm outward against a dumbbell or band, elbow at your side (external rotation), 3 sets of 8 to 12 reps, taking 3 seconds to return to the start (the phase), with small increases in load each week
- Side-lying external rotation (lying on your side and turning the top arm outward), Y, T and W arm lifts lying face down, and face-down rows, for the muscles that steady the shoulder blade
- Cable or band rows at chest height, focusing on drawing the shoulder blades back (retraction) and turning the arm outward
- Landmine press (pressing up one end of a barbell whose other end is anchored at the floor) and half-kneeling press progressions, to bring back pressing at angles short of straight overhead
- Loaded carries (walking with a weight in each hand, the farmer carry, or in one hand, the suitcase carry) to train the shoulder and shoulder blade to stay steady while moving under load
Possible progression milestones
Outward rotation strength getting closer to the other side, moderate dumbbells loaded through full available range without painful catching, and overhead reach for daily tasks without hitching.
Phase 3Return to Overhead and Demand-Specific Loading
Rebuild the shoulder's ability to handle overhead work, faster movements and work at the end of its reach. Later rehabilitation helps prepare the shoulder for the demands you want to return to. Return to overhead sport is guided by rotation strength, shoulder blade control and sport-specific load built up in steps, rather than the calendar. A flare can still happen after a well-completed program; if it does, I review the plan with you.
Example exercises
- Overhead press progressions, from a landmine press to full overhead dumbbell and barbell presses
- Pull-up and lat pulldown progressions, plus weighted rows heavy enough to build strength
- Fast throw-and-catch work for the cuff (): medicine ball chest passes, overhead throws and rebounder drills (throwing a ball against a small trampoline), for throwing athletes
- Drills for your sport or job (throwing technique, swim stroke, overhead lifting), with the amount built up in planned steps
- Strength work at the end of the shoulder's reach: holding weight fully overhead, Turkish get-ups (getting up from lying to standing while holding a weight overhead), and bottoms-up kettlebell work (holding a kettlebell upside down by its handle), for steadiness with the arm at full stretch
Possible progression milestones
Strength close to the other side on rotation, lifting and pressing, sport or job demands managed at the usual volume without pain, and confidence in the shoulder during unplanned or reactive movements.
What you can do now
- Support the arm at night. Many people do better on the other side with the sore arm supported forward on a pillow, or on their back with a small pillow under the elbow. Night pain often eases over a few weeks of the right loading, though how quickly varies.Avoid sleeping on the sore shoulder for now; a wall of pillows can help when you sleep on your side. Severe, constant pain that does not change with position needs a medical review: see the warning signs on this page.
- Start with static holds. Press the arm outward into a wall or doorframe with the elbow at your side, so the cuff muscles tighten without the arm moving. Phase 1 uses 30 to 45 seconds at a moderate, comfortable effort, 4 to 5 repetitions daily.Stop before any sharp pain.
- Keep training, with a few swaps. Complete rest tends to backfire. For now, drop the movements that flare you, often overhead pressing, upright rows and behind-the-neck work, and keep loaded work below shoulder height.Bring overhead loading back in steps as symptoms settle, rather than stopping everything for a month and then jumping back to your old program.
- Judge the dose by the next morning. Some soreness while you exercise is fine if it settles within a day. Go by how the shoulder feels the next morning, not mid-session, so you do not overdo it on good days.Stay with little or no pain or bearable discomfort, and ease off if you get sharp pain.
- Change position often. Posture itself has only a weak link with this pain, but holding the arm forward or overhead for long spells, or staying at the end of your reach, tends to aggravate a sensitive shoulder. An hourly reminder to change position can help.
What I use in clinic
- Structured exercise program. Can help most people.
- Shoulder blade (scapular) control exercises. Part of the program. Altered shoulder blade movement has been linked to a higher risk of future shoulder pain in athletes without pain.
- Surgery compared with exercise. High-quality trials, including one with placebo surgery, have not shown a long-term benefit of surgery to shave bone and make more space (decompression) over exercise, so surgery is not a first-line treatment.
- Steroid (corticosteroid) injection. Can give better short-term relief than exercise alone over the first several weeks, with no long-term advantage. Most useful to calm a very irritable shoulder enough to start exercise.
Recovery
How long it takes
Recovery is measured in months. Some improvement often comes within 2 weeks, with substantial progress by 6 to 8 weeks, and most people improve over 3 to 6 months.
Many people improve with treatment that does not involve surgery. Left alone, it can linger, and the shoulder can become more sensitive over time.
What changes the timeline
- Having symptoms for more than 3 months is linked with a slower recovery
- Stress at work and little support from others (psychosocial factors) substantially affect how well you recover
- Middle age (45 to 54) is linked with a longer recovery
- The shape of the bony point of the shoulder (the acromion) does not predict how you will recover
- More pain and difficulty with daily tasks at the start calls for more intensive treatment
- Keeping up the exercises affects progress
How I track it. I track how much the pain gets in the way of the tasks that matter to you, how well you move when I test those tasks in clinic, and how confident you feel in daily activities
Similar conditions
Conditions that can feel similar
- Rotator Cuff Tear (Full or High-Grade Partial)
- Weakness out of proportion to pain when turning the arm outward or lifting it out to the side against resistance, the arm dropping when lowered slowly from shoulder height (drop-arm test), and a history of sudden loss of strength, often after an injury in younger people. Subacromial pain typically shows a painful arc, with strength intact once the pain is eased.
- Frozen Shoulder (Adhesive Capsulitis)
- Movement is lost in every direction, even when someone else moves the arm, particularly turning the arm outward with the elbow at the side, with a firm stop. With subacromial pain the arm usually still moves fully when moved for you, and the signs are weakness against resistance or a painful arc rather than true tightness of the joint capsule, although early frozen shoulder can be hard to tell apart.
- AC Joint Pathology
- Pain pinpointed at the top of the shoulder over the AC joint, which is tender to press. Reaching the arm across the body brings it on (cross-body adduction test). Testing the cuff against resistance is often pain-free, which helps tell it apart from a subacromial problem, although the two can coexist.
- Biceps Tendinopathy
- Pain at the front of the shoulder over the groove the biceps tendon runs in (bicipital groove). Pain when bending the elbow or turning the palm up against resistance (Speed and Yergason tests). Subacromial pain more often spreads to the outer upper arm with overhead movement, although the two can overlap.
- Cervical Radiculopathy (C5-C6)
- Arm pain that follows the path of one nerve from the neck (a dermatomal pattern). Tilting the head and pressing down on it brings on the arm pain (Spurling test), and there may be nerve signs such as a changed reflex or weakness in particular muscles. The shoulder moves fully when moved for you, and testing the cuff against resistance is usually pain-free.
- Calcific Tendinopathy of the Rotator Cuff
- Often sudden, severe pain out of proportion to what the examination finds, a calcium deposit visible on X-ray or ultrasound, and a more sudden, dramatic course than the gradual start typical of subacromial pain.
Questions
What patients ask me most
Is shoulder impingement actually a pinching problem?
The name is misleading. Modern terminology has moved toward subacromial pain syndrome or rotator cuff-related shoulder pain, because the older mechanical model of the acromion pinching the cuff does not match what the evidence shows. Imaging studies find so-called hooked acromions in plenty of pain-free shoulders, and the CSAW trial (Beard et al., Lancet 2018) found that shaving the underside of the acromion produced no meaningful benefit over placebo surgery. What I see in clinic is a loading problem: the cuff cannot yet handle the demands placed on it, often alongside shoulder blade control issues and a more sensitive shoulder (sensitisation). So treatment focuses on building capacity rather than making more space.
Do I need an MRI before starting physio?
Rarely. For straightforward shoulder pain of this kind, without warning signs and not caused by an injury, MRI usually adds cost and anxiety without changing the plan. Imaging finds rotator cuff abnormalities in plenty of pain-free shoulders, especially past age 50, so a finding on the scan does not automatically explain your pain. I flag it to your family doctor and refer you for imaging only for shoulders not responding to 6 to 12 weeks of appropriate loading, suspected full-thickness tears from an injury, or when a specific clinical question would genuinely change the plan.
How long until I feel better?
Most people notice meaningful change in 6 to 12 weeks of consistent loading, with further gains over 3 to 6 months. The biggest predictor of slower recovery I see is symptom duration before starting care, which matches Chester and colleagues (BJSM 2018, 1030 patients) who found longer symptom duration, higher pain at the start, and lower confidence in managing pain (pain self-efficacy) consistently predicted worse outcomes at 6 weeks and 6 months. Psychological factors were more strongly associated with outcome than any specific structural finding. Starting structured loading early usually helps more than waiting it out.
Why does it hurt more at night?
Night pain is common with this kind of shoulder pain. Lying on the sore side or holding the arm in one position for a long time can aggravate it, but position is not the whole explanation, and a sensitive tendon can simply be more irritable at rest. Many people do better on the other side with the sore arm supported forward on a pillow, or on their back with a small pillow under the elbow. Night pain often eases over a few weeks of appropriate loading, though how quickly varies. Severe, constant pain that does not change with position needs a medical review.
Should I get a cortisone injection?
It has a role, but a narrow one. The higher-quality evidence shows a steroid injection under the point of the shoulder (subacromial corticosteroid) provides short-term pain relief over the first 6 to 8 weeks with no long-term advantage over exercise alone. I consider it when pain is so high that someone cannot engage with loading, or when sleep disturbance has pushed them into a flare-up cycle. It buys a window. It does not fix the underlying capacity problem, and repeated injections carry their own risks.
Do I need surgery if exercise does not work quickly?
Surgery is not the next step after a slow month of rehab. The CSAW trial (Beard et al., Lancet 2018) randomised 313 patients with at least 3 months of subacromial pain who had not improved with non-surgical care, including exercise and at least one steroid injection. Keyhole surgery to shave the acromion (arthroscopic subacromial decompression) produced no clinically important benefit over placebo surgery at 6 months. The 2022 JOSPT clinical practice guideline on rotator cuff disorders (Lafrance et al.) recommends against subacromial decompression for rotator cuff tendinopathy. My threshold for a surgical referral conversation is a shoulder that has genuinely plateaued on well-delivered loading over several months, not weeks.
Can I keep lifting weights?
Usually yes, with modifications. Complete rest tends to backfire. Early on I cut the movements that flare you (often overhead pressing, upright rows, behind-the-neck work), keep loaded work below shoulder height, and add static cuff holds (isometrics) and shoulder blade work. As symptoms settle, overhead loading comes back in progressively. Keeping some modified training going is usually easier to build back from than stopping everything for a month and then jumping back to your previous program.
Is bad posture causing this?
Less than most people assume, but not nothing. Cross-sectional studies have not shown a strong link between a specific resting posture and shoulder pain, so I do not spend much clinic time straightening people into an idealised upright position. What does matter is positional variety and cuff capacity: not staying for long at the end of your range of movement, moving regularly, and having enough strength to tolerate the positions your day requires.
The science
The Science of Shoulder Impingement Syndrome
Shoulder ( pain syndrome) involves irritation of the tendons and in the subacromial space. Despite the name, it's now understood as more than just mechanical compression. The tendons develop changes and the bursa becomes thickened, not from simple pinching but from a complex interaction of factors.
Modern understanding shifts away from blaming the shape of your (the 'hooked' acromion seen on X-rays is common in pain-free shoulders too). Instead, I treat it as a load-related irritation of the rotator cuff tendons and the bursa: the tendons are being asked to do more than they are ready for. That is why it overlaps so closely with rotator cuff and shoulder , and why all three respond to the same gradual loading.
Contributing factors
This is a capacity problem rather than a pinch. The common contributors are a that is weak or tires quickly, shoulder blade muscles that are not keeping up, and a recent jump in overhead work, training or lifting.
In overhead athletes, the rest of the body matters too, because much of the power for throwing and serving comes from the legs and trunk. This is why I look at how you throw, serve or press, not just at your shoulder.
Common aggravating factors include the 'boom-bust' cycle of overdoing on good days, specific movements like overhead reaching or reaching behind, sleeping on the affected shoulder, and periods of increased stress which heighten muscle tension and pain sensitivity.
Research
What the studies show
Shoulder blade exercises for shoulder impingement
This review pooled 8 randomised trials with 387 participants. Shoulder blade stabilising exercises were linked with greater improvements in pain and in a shoulder pain and disability score than standard physiotherapy.
Suggests shoulder blade exercises are worth including in physiotherapy for this condition.
Zhong Z, Zang W, Tang Z, Pan Q, Yang Z, Chen B. Effect of scapular stabilization exercises on subacromial pain (impingement) syndrome: a systematic review and meta-analysis of randomized controlled trials. Front Neurol. 2024;15:1357763. PMID: 38497039.
Non-surgical physiotherapy for shoulder impingement: an update of reviews
This update brought together systematic reviews of non-surgical physiotherapy for this kind of shoulder pain. It reported strong evidence supporting exercise, hands-on treatment (manual therapy) and approaches that combine several treatments. Exercise showed consistent benefits for pain and function across multiple high-quality reviews.
Supports non-surgical care as the first treatment for shoulder impingement.
Pieters L, Lewis J, Kuppens K, et al. An update of systematic reviews examining the effectiveness of conservative physical therapy interventions for subacromial shoulder pain. J Orthop Sports Phys Ther. 2020;50(3):131-141. PMID: 31726927.
Related Conditions
Conditions I commonly see alongside, or confused with, this one.
Getting back to it
Physiotherapy for shoulder impingement syndrome, built around the activity you want back.
