Morton's Neuroma
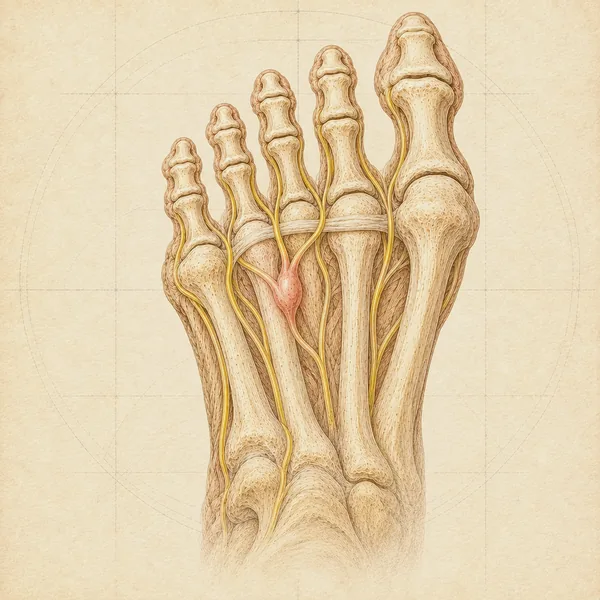
Morton's neuroma is a thickened, irritated nerve between the bones of the forefoot, most often between the third and fourth toes. It often causes burning or electric pain in the ball of the foot, numbness in the toes and a feeling of walking on a pebble. Tight shoes can aggravate it, and taking them off may help.
Does this sound like you?
- Sharp, burning, or electric shock-like pain in the ball of the foot
- Numbness or tingling in two neighbouring toes (typically the third and fourth)
- Sensation of walking on a pebble, marble, or rope in the shoe
- Pain that intensifies with weight-bearing and tight footwear
- Quick relief when you take the shoe off and rub the forefoot
- Cramping sensation in the forefoot during activity
Often alongside it
- Shooting pain that radiates into the affected toes
- Increased symptoms with prolonged standing or walking
- Pain that worsens throughout the day
- Difficulty wearing normal shoes comfortably
- Night pain in severe, long-standing cases
- Walking differently to keep weight off the front of the foot
Symptoms typically creep in gradually, and people often put them down to ill-fitting shoes or more activity. At first the pain comes only in certain shoes, then with most shoes, and eventually even when walking barefoot. A click may be felt when the forefoot is squeezed from side to side (a 'Mulder's click'). It can affect both feet, usually one more than the other.
Before using this comparison, check when these symptoms need a doctor first.
When to see a doctor first
Redness, heat or swelling after an injection with fever, chills or feeling generally unwell
Go to emergency now. This can be a serious infection
Redness, heat or swelling after an injection, without fever, chills or feeling unwell
Same-day medical assessment for a possible infection
Sudden severe forefoot pain after an injury, or pain at one spot on a bone
See your family doctor or urgent care for an X-ray to rule out a fracture
Weakness in the toes or foot that keeps getting worse
See your family doctor promptly to check for a different nerve problem
Numbness spreading beyond two neighbouring toes, or in both feet
See your family doctor before starting physiotherapy, to check for tarsal tunnel syndrome or a nerve condition such as diabetic neuropathy
No improvement after 16 weeks of non-surgical care
I flag it to your family doctor, who can arrange an ultrasound or MRI and a specialist opinion on injection or surgery
How it is treated
Treatment without surgery can settle symptoms in many cases, combining a change of shoes, a metatarsal pad under the forefoot and cutting back on what aggravates it. This is particularly true when it starts soon after symptoms begin.
Injections are given by a physician. A 2024 Cochrane review, which brought together the available trials, found that adding a steroid (corticosteroid) to a numbing injection (local anaesthetic) made little to no difference to pain at three to six months. Using ultrasound to guide the needle probably helped.
Continuing with wide, low-heeled footwear after symptoms settle may lower the chance of a flare.
A typical rehabilitation progression
Recovery from Morton's neuroma is usually staged: calm the symptoms first, then rebuild the strength and capacity of the area, then return to your full activities. The phases below show how that can progress.
Phase 1 · Weeks 1 to 4
Calming the Nerve and Taking Pressure Off the Forefoot
Reduce the squeeze on the nerve when you walk, then add gentle movement work around the . Most of the improvement in this phase comes from changing shoes, a well-placed pad and a real cut in the time spent in tight shoes. Exercise in this phase supports those changes rather than fixing the problem on its own.
Example exercises
- Wearing a shoe with a clearly wider toe box and a heel under roughly 2 cm every day, for work, commuting and errands
- A metatarsal pad placed just behind the painful space between the toe bones, positioned by a clinician at first, then checked over the first week to make sure you tolerate it
- Spreading the toes apart (toe splay) and using a toe spreader at home for 5 to 10 minutes, for comfort and toe movement
- Gentle loosening between the toes (interdigital mobilisation): pinching the skin between the toes and separating them softly, 10 slow repetitions for each gap, daily
- Changing your activity: cut back on long walks in shoes that bring on symptoms, and choose comfortable footwear at home; barefoot time or a roomy sandal is optional if comfortable, with a wide, cushioned indoor shoe as an alternative
Phase 2 · Weeks 4 to 10
Strengthening the Small Muscles of the Foot
Once the nerve has calmed, rebuild the strength and control of the small muscles inside the foot (the ) that support the arch across the ball of the foot (the transverse arch). I use these exercises as an adjunct for foot strength and control; they have not been shown to decompress the nerve or reverse the neuroma. Keep wearing shoes with a wide toe box and using the metatarsal pad during this phase.
Example exercises
- Short-foot exercise: gently shortening the arch by pulling the ball of the foot toward the heel without curling the toes, 3 sets of 10 with 10-second holds
- Toe splay holds, actively spreading the toes apart, 3 sets of 10 with 5-second holds, progressing from seated to standing
- Towel scrunches and picking up small objects with the toes, to train control of the small foot muscles, 2 sets of 15 to 20 repetitions per foot
- Standing on one leg on firm ground with the foot neither rolled in nor out (a neutral foot posture), 3 sets of 30 to 45 seconds, progressing to a foam pad
- Calf raise variations (rising onto your toes) with the heel moving cleanly in line with the second toe, 3 sets of 12 to 15, to keep the forefoot lined up as you push off
Phase 3 · From Month 3
Return to Activity and a Long-Term Shoe Plan
Build back up to the activities that used to bring on symptoms, including longer walks, running if you run, and, if it is one of your goals, the occasional narrower or dressier shoe. The long-term plan is not avoiding certain shoes completely but choosing shoes with care: foot-shaped shoes for everyday wear, and narrower shoes now and then.
Example exercises
- Increasing how far or how long you walk or run in small weekly steps, bringing back landing on the front of the foot (forefoot strike) cautiously if you run that way
- Strengthening the small foot muscles twice a week to keep the gains, rather than daily
- Bringing back narrower or dressier shoes for shorter spells, with recovery time in wider shoes, rather than all-day wear
- Keeping up calf and single-leg exercises, with body weight or a light load, to support control of the forefoot
- Periodic footwear reviews every 6 to 12 months, because sock thickness, shoe wear, and foot shape all change over time
What you can do now
- Wear a wide, low-heeled shoe every dayChoose a toe box with room to spare (about a thumb's width between your longest toe and the end of the shoe) and a heel under about 2 cm, for work, commuting and errands. Narrow toe boxes and raised heels push the ends of the long foot bones together and add pressure on the irritated nerve, so wearing suitable shoes consistently for a few months gives it a chance to settle.Keep dressier shoes for later: many people go back to them once things have settled, but more selectively than before.
- Place a metatarsal pad behind the sore spotThe pad sits just behind the painful space between the toe bones, not on top of it. Lifting the long foot bones from behind opens the space between their ends as you push off and takes the squeeze off the nerve.A pad set too far forward often makes symptoms worse; if yours seems to, have its position checked in clinic. Replace pads once they wear down.
- Cut back on long walks in tight shoesFor a while, shorten long walks, long spells of standing and high-impact activity, especially in the shoes that bring it on, so the irritated nerve can settle. Around the home, choose what is comfortable: barefoot time or a roomy sandal may suit some people, while others do better in a wide, cushioned indoor shoe.This is a temporary change; build your walking back up in small weekly steps as symptoms settle.
- Spread and gently loosen the toes dailySpread your toes apart, or use a toe spreader, for 5 to 10 minutes at home, then gently pinch the skin between the toes and separate them softly, 10 slow repetitions for each gap. This is for comfort and toe movement, not a demonstrated way to create more space around the nerve.Keep it gentle, and stop if pain, numbness or tingling increases. Numbness that spreads beyond two neighbouring toes, or appears in both feet, needs your family doctor before you start physiotherapy, as the warning signs on this page explain.
What I use in clinic
- Fitting metatarsal pads and orthoticsCorrectly placed pads can reduce forefoot pressure and ease symptoms. Custom orthotics are an option when simpler pads and footwear changes have not helped.
- Hands-on treatment (manual therapy)Gentle movement of the joints between the toe bones and at the base of the toes, combined with techniques that glide the nerve (neural mobilization), may give short-term relief alongside footwear and padding changes.
- Steroid injection (corticosteroid)Given by a physician, not by me. The 2024 Cochrane review found that adding the steroid to a numbing injection (local anaesthetic) gave little to no extra pain relief, and it occasionally thinned the skin or the fat pad under the foot. Using ultrasound to guide the injection probably reduced pain more than an unguided injection.
How long it takes
- Weeks 1 to 4Calming the Nerve and Taking Pressure Off the Forefoot
- Weeks 4 to 10Strengthening the Small Muscles of the Foot
- From Month 3Return to Activity and a Long-Term Shoe Plan
Many people notice some change within several weeks of footwear changes and padding, and improvement can continue over a few months. Long-standing cases may take longer.
Symptoms often come and go with footwear and activity, and in some people they become more constant over time. Many people settle with footwear changes and padding. Surgery has good reported results but can leave permanent numbness in the toes, so it is reserved for those who do not settle with treatment without surgery.
What changes the timeline
- How long you have had symptoms before starting treatment: earlier treatment tends to do better
- How severe it is when you first come in: constant pain tends to mean a slower recovery
- Footwear: people who stay with suitable shoes tend to do better
- When both feet are affected, it often points to factors in how the feet are built and move, which need a broader plan
- Body weight and activity level affect both how it develops and how it responds to treatment
- Other foot problems, such as hammer toes or bunions, may complicate treatment and recovery
Progress. I monitor your pain during different activities, how long you can walk without symptoms, whether you can wear suitable shoes comfortably, and changes in toe numbness or tingling
Conditions that can feel similar
- Metatarsophalangeal Joint Synovitis
- Tenderness right over a toe joint at the ball of the foot, pain when I move the joint, and sometimes visible swelling
- Stress Fracture of Metatarsal
- Tenderness at one spot on the bone, pain when the bone is tapped (percussion test), and worse with impact activities
- Tarsal Tunnel Syndrome
- Symptoms start at the inner ankle, tapping over the nerve there sets off tingling (Tinel's sign), and numbness covers a wider area of the sole
- Plantar Plate Tear
- It typically affects the second toe. Pushing the base of the toe upward shows too much movement or brings on pain (drawer test), and the toe may drift sideways or lift up
- Intermetatarsal Bursitis
- Pain is more spread out, with less tingling or numbness, and it may respond to anti-inflammatory medicines
Side by side
NextQuestionsWhat patients ask me most
Why does it feel like there is a pebble or a lump in my shoe when there is nothing there?
The enlarged nerve sits between the bones of the forefoot, and as you push off, the ends of the long foot bones (the metatarsal heads) squeeze it. The brain interprets the pressure and altered nerve signalling as something under the foot rather than as a nerve problem. That pebble feeling is one of the most recognisable features of Morton's neuroma, and people often try different insoles and shoes for months before realising the sensation is coming from inside the foot, not outside it.
Do I have to give up the shoes I like?
For now, mostly yes, but not for good. During the active treatment phase the shoe choice is doing most of the work. Narrow toe boxes and raised heels push the metatarsal heads together and drive pressure up through the forefoot, which is exactly what the irritated nerve cannot tolerate. A wider toe box and a heel under about 2 cm, used consistently for a few months, gives the nerve a chance to settle. Many people return to a dressier shoe afterwards, but often on a more selective basis than before.
Should I have a cortisone injection?
An injection is an option to discuss with a physician if footwear changes and padding have not helped enough. The evidence is limited: in the 2024 Cochrane review, adding a steroid to a local anaesthetic injection made little or no difference to pain at three to six months, while ultrasound guidance probably improved results compared with an unguided injection (Matthews et al., 2024). Steroid injections can also thin the skin or the fat pad under the foot in a small number of people. The benefits, side effects and alternatives deserve their own discussion with the physician giving it, and the footwear and loading changes still matter either way.
How do metatarsal pads help, and where do they go?
A metatarsal pad sits behind the painful space between the toe bones, not on top of it. By lifting the long foot bones from behind, the pad opens up the space between their ends as you push off and takes the squeeze off the nerve. A pad set too far forward often makes symptoms worse, because it pushes directly into the sensitive area rather than behind it. Getting the position right is usually the difference between a pad that clearly helps and one you quickly give up on.
Will Morton's neuroma go away completely?
Most well-treated cases settle substantially, and many people return to pain-free daily life. The nerve thickening itself does not always fully reverse, and the nerve may stay somewhat enlarged even after pain resolves. Some people have mild residual numbness in the affected toes as a trade-off for eliminating the shock-like pain. Trial evidence for non-surgical care is limited, but in my experience earlier footwear and loading changes tend to settle things more easily than long-standing cases.
What is the difference between Morton's neuroma and metatarsalgia?
Metatarsalgia describes mechanical overload under the metatarsal heads, often with calluses and a bruised, aching quality. Morton's neuroma is a nerve problem between the metatarsal heads, with electric shock, burning, or tingling radiating into the toes, often with a sense of something underfoot. They can coexist. When both are present, the treatment order usually goes footwear first, then forefoot offloading, then a closer look at which component is lingering.
The science of Morton's neuroma
Morton's neuroma, more accurately termed intermetatarsal neuroma, represents a localized thickening of the common digital nerve as it passes beneath the deep transverse ligament. Despite its name, this condition is not a true neuroma but rather perineural fibrosis, a reactive thickening of the nerve sheath and surrounding connective tissue.
The condition most commonly affects the third intermetatarsal space (between the third and fourth metatarsals) due to unique anatomical factors. In this location, the medial and lateral plantar nerves converge, creating a larger nerve bundle that is more susceptible to compression. The nerve passes beneath the ligament that joins the metatarsal heads (the deep transverse metatarsal ligament), and can be compressed against that ligament and between the neighbouring metatarsal heads during toe-off.
Repetitive mechanical irritation leads to chronic inflammation of the nerve sheath, followed by progressive fibrosis and thickening. This creates a pathological cycle where the enlarged nerve becomes increasingly susceptible to further compression. The resultant ischemia and mechanical deformation of nerve fibers produces the characteristic pain symptoms.
Contributing factors include biomechanical abnormalities that increase loading, such as excessive , first ray insufficiency, or metatarsal length variants. Intrinsic factors like hammertoe deformities or claw toes can further compress the intermetatarsal spaces. The condition is much more common in women, largely attributed to restrictive footwear with narrow toe boxes and elevated heels that force the metatarsals together and increase forefoot loading.
Normal mechanics distribute weight-bearing forces relatively evenly across all five during push-off. The intermetatarsal nerves lie in the relatively protected spaces between adjacent metatarsals, with adequate clearance during normal gait patterns.
When biomechanical dysfunction occurs, several factors can increase nerve compression. Excessive forefoot loading, whether from first ray insufficiency, flexible flatfoot, or gastrocnemius tightness, increases the forces transmitted through the lesser metatarsals. This creates a more forceful "squeeze" of the intermetatarsal spaces during propulsion.
High-heeled shoes create a cascade of biomechanical changes: the elevated heel shifts body weight forward and increases forefoot loading. Narrow toe boxes force the metatarsals into a more compressed position, reducing the available space for neural structures. The combination creates maximum compression precisely where the nerve is most vulnerable.
As the foot widens with weight-bearing, the intermetatarsal spaces normally expand slightly to accommodate nerve movement. Restrictive footwear prevents this natural accommodation, maintaining compression throughout the stance phase of gait.
The 's role in maintaining arch stability affects metatarsal mechanics. When the plantar is tight or the is inefficient, compensatory overloading of the forefoot can occur. This explains why Morton's neuroma often coexists with other forefoot like metatarsalgia or plantar .
What the studies show
- 2024 · Cochrane Database of Systematic Reviews
Treatments for Morton's neuroma
This Cochrane review found only a few trials (6 randomised trials, 373 participants), and none was free of concerns about bias. Adding a steroid (corticosteroid) to a numbing injection (local anaesthetic) made little to no difference to pain at three to six months, while guiding the injection with ultrasound probably reduced pain compared with an unguided injection.
Footwear changes and padding remain a sensible first step because of how they take pressure off the forefoot, but the trial evidence for every option, including injections, is limited.
Matthews BG, Thomson CE, Harding MP, et al. Treatments for Morton's neuroma. Cochrane Database Syst Rev. 2024;2(2):CD014687. PMID: 38334217.
- 2016 · Bone & Joint Journal
In one trial, ultrasound guidance made no clear difference to the results of steroid injections
In this randomised trial, steroid injections improved symptoms whether or not ultrasound was used to guide the needle, and using ultrasound made no clear difference to the result. Because both groups had the same steroid injection, the trial cannot show whether the steroid itself helps.
In this single trial, ultrasound guidance made no clear difference to results, although the 2024 Cochrane review, pooling two trials, found it probably reduced pain more.
Mahadevan D, Attwal M, Bhatt R, Bhatia M. Corticosteroid injection for Morton's neuroma with or without ultrasound guidance: a randomised controlled trial. Bone Joint J. 2016;98-B(4):498-503. PMID: 27037432.
- 2006 · BMC Musculoskeletal Disorders
Metatarsal pads placed behind the ends of the foot bones lowered forefoot pressure in people with ball-of-foot pain
In people with pain under the ball of the foot (metatarsalgia), metatarsal pads placed just behind the ends of the long foot bones (the metatarsal heads) reduced the highest pressure under the forefoot, and were linked with people reporting that their symptoms improved. This gives a mechanical reason to place pads behind the painful space between the toe bones, rather than directly under it.
This informs how insoles and shoes are set up to take pressure off the forefoot, with the pad just behind the ends of the long foot bones.
Kang JH, Chen MD, Chen SC, Hsi WL. Correlations between subjective treatment responses and plantar pressure parameters of metatarsal pad treatment in metatarsalgia patients: a prospective study. BMC Musculoskelet Disord. 2006;7:95. PMID: 17147793.
- 2010 · International Orthopaedics
Surgery to remove the nerve gave excellent or good results in about 82% of feet
In 78 people (82 feet) followed for an average of about 4.6 years, surgery to remove the nerve (Morton's neurectomy) gave excellent or good results in about 82% of feet, fair results in 10% and no improvement in 8%. This supports surgery as a reasonable option when symptoms do not settle with treatment without surgery, while a minority of patients remain dissatisfied.
These outcome figures can help you make an informed decision about surgery if treatment without surgery has not helped.
Pace A, Scammell B, Dhar S. The outcome of Morton's neurectomy in the treatment of metatarsalgia. Int Orthop. 2010;34(4):511-515. PMID: 19484237.
Keep reading
Guides on foot & ankle pain
 Plantar Calcaneal Spur (Heel Spur)A small ledge of bone under the heel bone on a foot X-ray. What the report wording means, why a spur is common without pain, and how heel pain is treated whether or not a spur is there.
 Thickened Plantar FasciaA plantar fascia over 4 mm, hypoechoic, with Doppler signal or a partial tear on an ultrasound or MRI. What normal thickness is, why the number did not predict recovery, and what the guidelines recommend.
 Achilles TendinosisA thickened or changed Achilles tendon on an ultrasound or MRI, mid-portion or insertional, with the Doppler, partial tear, bursitis and Haglund wording around it. How common it is in painless tendons and why the two locations are loaded differently.
 Achilles Tendon Rupture: Treatment and RecoverySudden Achilles injury, diagnosis, surgical and non-surgical treatment, boot protection, calf strength and return to running or sport.Lisfranc Injury: Midfoot Stability and RecoveryMidfoot injury, weight-bearing X-rays, CT and MRI, stable and unstable injuries, treatment choices and rehabilitation.
 Heel Pain on the First Steps in the MorningWhy the first steps after sleep or sitting can hurt, how pain under the heel differs from pain at the back, and what you can try before standing.
 Shin Pain When RunningWhat to notice when a run brings on shin pain, when to stop impact and get it checked, and how a return to running can be planned.
Related conditions
 MetatarsalgiaBoth cause forefoot pain; neuroma can be mistaken for metatarsalgia
 Hallux Valgus (Bunions)Bunion deformity can alter forefoot mechanics contributing to neuroma development
 Hammer Toe DeformitiesToe deformities can contribute to neuroma formation through altered mechanics
 Plantar Fasciitis & Heel SpursBoth involve forefoot loading issues; altered mechanics can affect both conditions
I write and review every page on this site myself, and the review date at the top is the last time I checked this one. If something here is out of date, tell me.
Getting back to it
Physiotherapy for Morton's neuroma, built around the activity you want back.