
De Quervain's Tenosynovitis
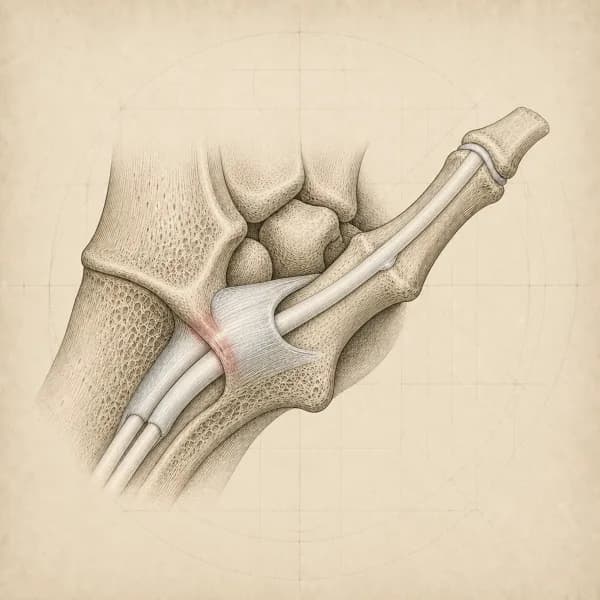
De Quervain's tenosynovitis is pain on the thumb side of the wrist, where two thumb tendons pass through a narrow tunnel and their sheath becomes thickened and irritated. It often follows new, repeated thumb and wrist use, such as lifting a baby, and gripping or lifting with the thumb up tends to hurt.
Key points
- What usually helps
- A thumb splint with activity changes. A splint combined with a cortisone injection succeeded more often in trials.
- What you can do now
- Wear the thumb splint as planned. If you lift a baby, use your forearms.
- How long it takes
- Mild cases often improve over several weeks; longer-standing cases can take a few months.
- When to see a doctor first
- Some signs need emergency care. Check the list before you start treatment.
Symptoms
Does this sound like you?
- Sharp pain in one spot on the thumb side of the wrist, 2 to 3 cm above the base of the thumb
- Visible swelling over the bony bump on the thumb side of the wrist (the radial styloid)
- Thumb-side wrist pain with lifting, gripping, or certain thumb movements. A clinician can use gentle examination tests to assess the tendons; avoid repeatedly forcing the thumb into a painful stretch to check it yourself
- Difficulty gripping and lifting, especially with the thumb pointing up
- Pain when moving the thumb away from the hand or straightening it (abduction and extension)
Often alongside it
- Catching, snapping or a grinding feeling (crepitus) when the thumb moves
- Pain spreading up the forearm toward the elbow, or down into the thumb
- A weaker grasp and pinch with the thumb
- Morning stiffness in thumb and wrist requiring warm-up period
- Difficulty with activities requiring pinch grip (turning keys, opening jars, using scissors)
It comes on gradually over weeks to months, often after starting a new repetitive activity (caring for a baby, gardening, more texting or gaming). At first the pain comes only with certain movements, then gradually becomes more constant and appears with simple tasks. Both wrists are often affected, though not always equally. It is much more common in women, particularly after childbirth or between the ages of 40 and 60.Book an assessment for de Quervain's tenosynovitis
When to see a doctor first
Go to emergency
Fever or feeling unwell with a red, hot, swollen wrist or thumb
Go to emergency now to rule out an infected tendon sheath
Get seen today
Pain in the hollow at the base of the thumb (the anatomical snuffbox) after a fall onto an outstretched hand
Get a prompt medical assessment, the same day or next day, for an X-ray. Until then, support the wrist in a splint and avoid lifting or putting weight through it. An early X-ray can be normal, so continued suspicion needs follow-up imaging and protection; a missed scaphoid fracture can fail to heal
Check with your doctor
Numbness or tingling in the thumb or hand
Tell me at the assessment; if it is spreading or getting worse, see your family doctor to check for a nerve problem at the wrist or neck
Progressive pain and dysfunction despite 8-12 weeks of appropriate conservative treatment with good compliance
I flag it to your family doctor, who can arrange an injection, an ultrasound, or a surgical opinion
Several swollen or painful tendons or joints at the same time
See your family doctor to check for an inflammatory arthritis
Treatment
How it is treated
Main approach. A thumb splint (thumb spica) with activity changes can ease symptoms by reducing friction in the tendon tunnel on the thumb side of the wrist (the first dorsal compartment). When trial results were pooled, a splint combined with a cortisone (corticosteroid) injection succeeded more often than a splint alone or an injection alone (Cavaleri et al., 2016).
Alongside it. A cortisone injection from a physician, often with a short period in the splint, can be discussed early rather than only after other care has failed; the choice depends on your symptoms, your preferences and medical factors. Guiding the needle with ultrasound improves accuracy (Abi-Rafeh et al., 2022). Gentle tendon gliding and, later, strengthening help restore thumb use.
Managing it over time. Changing how you lift (taking a baby's weight on the forearm rather than on a stretched-out thumb), setting up tools and phone use to spare the thumb, and thumb and wrist strengthening lower the risk of it coming back in higher-risk groups, including new mothers and people in repetitive jobs.
A typical rehabilitation progression
Three phases, from settling symptoms to returning to full activity.
Recovery from de Quervain's tenosynovitis is usually staged: calm the symptoms first, then rebuild the strength and capacity of the area, then return to your full activities. The phases below show how that can progress.
Phase 1Calm the tendon tunnel (Weeks 1 to 3)
The first job is to reduce friction in the tendon tunnel on the thumb side of the wrist (the first dorsal compartment) and take the sting out of daily tasks. That means wearing the thumb splint consistently, moving only within a pain-free range, and taking a deliberate look at how the thumb is loaded during the day. Nothing in this phase should bring back the sharp pain on the thumb side of the wrist.
Example exercises
- An off-the-shelf or custom thumb splint (thumb spica) that supports the wrist and the base and knuckle joints of the thumb (CMC and MCP), leaving the thumb's end joint free, worn during waking hours for 2 to 3 weeks
- Pain-free bending and straightening of the thumb's end joint and knuckle (IP and MCP joints), 10 slow repetitions 3 times daily, to prevent stiffness
- Coaching on lifting technique for new parents: a wide scoop with the baby supported on the forearms, palms up where possible, thumbs kept close to the hand
- Ice over the bony bump on the thumb side of the wrist (radial styloid) for 10 to 15 minutes after aggravating activities, if it helps
- A review of daily tasks: cut down long spells of pinching (phone scrolling, gardening shears, scissors) rather than stopping every activity
Possible progression milestones
Tenderness over the bony bump on the thumb side of the wrist clearly reduced, the clinician's tendon stretch test () still uncomfortable but no longer sharp, and the thumb moving through a pain-free range without a flare, over one to two weeks of consistent splint use.
Phase 2Rebuild tolerance (Weeks 3 to 8)
Once the tendon sheath is calmer, start rebuilding strength in the thumb and wrist, and further up the arm. The aim is to tolerate everyday loads again without stirring up the tendon tunnel. Posture and shoulder blade control matter, because overuse at the hand and wrist often reflects poor support further up the arm.
Example exercises
- Holds without moving () for moving the thumb away from the hand and straightening it (thumb and extension), 5 seconds on, 5 seconds off, 3 sets of 10, at a load that never brings on pain on the thumb side of the wrist
- Tendon gliding through the tunnel: pain-free thumb circles and touching the thumb across to the fingertips (circumduction and opposition), avoiding the end of the Finkelstein stretch (thumb tucked in a fist, wrist bent toward the little finger) until symptoms are gone
- Strengthening for bending the wrist forward and back with a light dumbbell, moving slowly, 3 sets of 10 to 15 through a comfortable range
- Shoulder blade setting, rows and turning the arm outward (external rotation) with a light band, 3 sets of 10 to 12, to give the arm better support from the shoulder
- Weaning off the splint during light activities first, keeping it on for baby care, gardening or long spells of pinching
Possible progression milestones
The Finkelstein test no longer sharp, tenderness over the bony bump minimal or gone, strength moving the thumb away from the hand equal on both sides when tested by hand, and everyday tasks like opening jars or caring for a baby tolerated without a flare.
Phase 3Return to real demand (Weeks 8+)
Now the hand has to cope with the demands that caused the problem in the first place, often caring for a baby, pinching at work, or racquet and stick sports. The goal is a thumb and wrist that handle full load, with the technique changes kept for the long run. If a flare happens here, the plan steps back one phase rather than starting from scratch.
Example exercises
- Practice that copies real demands: longer holds while caring for a baby, long spells of tool use, grip work for your sport, with planned short breaks
- Full-range thumb and wrist strengthening with moderate resistance, 3 sets of 8 to 12, two to three times per week
- Grip and pinch work that builds up over time, measured with a grip gauge (dynamometer) or done with putty, aiming to match the uninjured side
- Carrying moderate dumbbells (farmer walks) to build how long you can hold a grip
- Ongoing upper back and shoulder blade exercises, particularly for desk workers and new parents who spend long hours feeding in supported positions
Possible progression milestones
Two weeks in a row of full daily and work demands without pain, thumb and grip strength equal on both sides, no need for the splint outside heavy one-off tasks, and a clear plan for what to do if a flare appears.
What you can do now
- Wear the thumb splint as planned. A well-fitted thumb splint (thumb spica) supports the wrist and the base and knuckle joints of the thumb, usually leaving the end joint free, so the irritated tendons can settle. A typical plan is waking hours for the first 2 to 3 weeks, then during heavier tasks for a further 3 to 4 weeks, taking it off to wash and to do your exercises.Make sure it holds the wrist straight. Skin irritation, numbness or extra swelling under the splint means it is too tight, so loosen or refit it.
- If you lift a baby, use your forearms. Scooping under the arms with the thumbs stretched out is the movement that keeps irritating the tendons. Use a wide scoop with the baby's weight on your forearms, palms up where possible and thumbs close to the side of the hand, and use both hands for every lift.Switch sides so one wrist is not overloaded, and use nursing pillows or a carrier where you can, so you lift less often.
- Spare the thumb on phones and tools. Use a phone holder or voice-to-text instead of long spells of thumb typing, and hold the phone with your fingers behind it rather than stretching the thumb across the screen. Choose padded, thicker handles, keep the wrist straight rather than bent sideways, and take a 30-second break every 10 to 15 minutes of repetitive work.
- Keep the thumb moving, gently. Slow, pain-free bending and straightening of the thumb, 10 times, 3 times a day, helps prevent stiffness in the early weeks. Once the early irritation has settled, usually after 2 to 3 weeks, gentle tendon gliding (5 slow repetitions, 3 to 5 times a day) keeps the two thumb tendons sliding through their tunnel.These should not cause sharp pain; mild discomfort is acceptable. Until late in rehab, avoid making a fist around the thumb and bending the wrist toward the little finger (the Finkelstein position), and do not keep testing that painful stretch yourself.
- Use ice after aggravating tasks. Ice over the bony bump on the thumb side of the wrist for 10 to 15 minutes after an aggravating activity can ease pain for a while. It tends to help more in the first 2 to 4 weeks than for long-standing symptoms.Put a towel between the ice and your skin to prevent an ice burn. A red, hot, swollen wrist or thumb with fever or feeling unwell is not a flare: go to emergency now (see the warning signs on this page).
What I use in clinic
- Thumb splinting. Splinting with activity changes can help, but in pooled trial data a splint alone succeeded less often than a splint combined with an injection (Cavaleri et al., 2016). The splint is usually worn for several weeks, then weaned. A 2023 analysis that compared many treatments across trials (a network meta-analysis) recommended an injection combined with 3 to 4 weeks in such a splint as a first-line option, although the added benefit of the splint was small (Challoumas et al., JAMA Network Open 2023).
- Activity changes. A core part of care, though trial evidence on specific techniques is limited; the practical steps are under What you can do now.
- Corticosteroid Injection. Given by a physician, not by me. Injection guided by ultrasound was more accurate than injection guided by feel (landmarks), with higher reported success rates (73 to 100% versus 59 to 83% across studies) (Abi-Rafeh et al., Plastic and Reconstructive Surgery, 2022).
- Hands-on treatment and tendon gliding. Limited evidence; gentle wrist and thumb mobilization and tendon gliding are used alongside splinting and activity changes to keep the thumb moving.
- Strengthening. Can improve load tolerance once the tendon sheath has settled; evidence on preventing recurrence is limited.
- Education. Understanding the condition, wearing the splint consistently, and knowing realistic timelines can help people stay with the plan.
Recovery
How long it takes
Mild cases often improve over several weeks of splinting and activity changes, and longer-standing cases can take a few months. A cortisone injection from a physician, often with a short period in a splint, can be discussed early or when symptoms persist, and surgery to open the tunnel (surgical release) is an option for the few who do not settle.
Some cases settle on their own, particularly after pregnancy as hormones and lifting demands change. Others persist for months, and long-standing cases with a thickened tendon sheath are more likely to need an injection or surgery to open the tunnel.
What changes the timeline
- How long you have had symptoms (a shorter history predicts a better response to non-surgical care; cases lasting over 6 months are more likely to need injection or surgery)
- How narrowed and thickened the tendon sheath is (marked thickening on ultrasound predicts a poorer response to non-surgical care)
- Natural variations in anatomy (a tunnel divided by a wall of tissue, a septum, may need surgery to open it if an injection fails; one of the thumb tendons (APL) split into several strands, or slips, complicates treatment)
- Whether you can change the activities that provoke it (new mothers who cannot avoid lifting a baby recover more slowly; changes at work are needed when work is the cause)
- Consistency with the splint and activity changes, if that is the chosen approach
- After childbirth (hormonal factors from pregnancy typically settle by 6 months after the birth, which helps healing)
- Other health conditions (diabetes, rheumatoid arthritis and an underactive thyroid are associated with slower healing and more treatment failures)
- Earlier treatments that did not work (several cortisone injections predict less success with further non-surgical care)
How I track it. I track your pain during specific activities (pinching, bending the wrist sideways, lifting), how tender the tendon tunnel is to press (measured with a pressure gauge, or algometer, when available), grip and pinch strength compared with the other hand, and the daily tasks you find hard. I repeat the thumb-and-wrist stretch tests (Finkelstein's and Eichhoff's) to see how the pain they bring on is changing
Similar conditions
Conditions that can feel similar
- Carpometacarpal (CMC) Arthritis (Thumb Base Arthritis)
- Pain at the joint at the base of the thumb, closer to the hand than De Quervain's, and worse with pinching and gripping. Pressing the thumb into its base joint while rotating it brings on pain (the grind test), the base of the thumb may look bumpy or squared off, and an X-ray shows narrowing of the joint and bone spurs (osteophytes)
- Intersection Syndrome
- Pain 4 to 6 cm further up the forearm from the bony bump on the thumb side of the wrist, where the two thumb tendons (APL and EPB) cross over the wrist extensor tendons. There may be visible swelling and a grinding feeling (crepitus). Lifting the back of the hand and bending the wrist toward the thumb against resistance brings it on. It sits higher up the forearm than De Quervain's
- Scaphoid Fracture (Acute or Non-union)
- A history of falling onto an outstretched hand, pain in the small hollow at the base of the thumb (the anatomical snuffbox), pain when the thumb is pushed in along its length toward the wrist, and pain when the scaphoid is compressed (scaphoid compression test). It needs imaging
- Superficial Radial Nerve Neuritis (Wartenberg's Syndrome)
- Burning, tingling pain over the back of the wrist and hand on the thumb side. Tapping over the nerve there (the superficial radial nerve) sets off tingling (Tinel's sign), symptoms come on when the wrist bends forward and toward the little finger (the opposite of De Quervain's), and the Finkelstein test is not painful
- Scapholunate Ligament Injury
- Pain more central in the wrist, a painful click when the wrist bends from side to side, and a painful clunk when the clinician presses on the scaphoid while moving the wrist (Watson's scaphoid shift test). Grip is weak, and there is a history of a wrist injury
Questions
What patients ask me most
Why does my thumb-side wrist hurt so much when I lift my baby?
That specific pattern (sharp pain on the thumb side of the wrist, just above the thumb, when you scoop a baby up under the arms) is the textbook De Quervain's picture. The scoop loads the two thumb tendons involved (abductor pollicis longus and extensor pollicis brevis) as they bend around the bony bump on the thumb side of the wrist (the radial styloid). New parents repeat that movement dozens of times a day, often with the wrist bent sideways and the thumb stretched out under load. It is one of the most common reasons post-partum patients end up in front of me.
Is Finkelstein's test enough to diagnose this?
It is one part of the clinical diagnosis, not the whole picture. The test often described online (making a fist around the thumb and bending the wrist toward the little finger) is strictly Eichhoff's manoeuvre, which can also be uncomfortable in healthy wrists (Wu et al., Journal of Hand and Microsurgery 2018). A clinician-performed test, combined with tenderness directly over the tendon tunnel on the thumb side of the wrist (the first dorsal compartment) and a story that fits (new parenting, a spike in thumb-loading activity, hairdressing, racquet sports), is often enough for a working diagnosis. What I am also doing is ruling out arthritis at the base of the thumb (CMC arthritis), intersection syndrome, a scaphoid problem, and irritation of a small nerve on the thumb side of the wrist (the superficial radial nerve). Those can all sit close by and be mistaken for each other.
Do I really have to wear a thumb spica splint?
Not always; it is one option. A properly fitted thumb spica supports the wrist and the base and knuckle joints of the thumb (CMC and MCP), usually leaving the thumb's end joint free, which takes load off the tendon tunnel. Huisstede and colleagues' 2018 systematic review in Archives of Physical Medicine and Rehabilitation supports splinting, particularly combined with corticosteroid injection, and a 2023 network meta-analysis recommended an injection plus 3 to 4 weeks in a splint as a first-line option, although the splint added only a small benefit (Challoumas et al., JAMA Network Open 2023). If you use one, consistency matters, and the fit and wearing schedule should suit your symptoms and daily tasks.
Will a cortisone injection fix this?
For many people with a confirmed De Quervain's, a well-placed corticosteroid injection into the first dorsal compartment can help, particularly when combined with a short period in a thumb spica, and it can be discussed early rather than only after other care has failed. Many people have a wall of tissue dividing the tunnel in two (a septum), and injections that miss one of the two sections do not work as well. That is why ultrasound-guided injection tends to outperform injection guided by feel (landmark-based) in the literature. Injection is not something I do myself, but I often coordinate with the physician who does.
How long until it settles?
Many mild and moderate cases improve over several weeks of splinting, activity modification, and graded exercise, or after an injection from a physician. Post-partum cases often continue to settle over a few months as the hormonal picture shifts and the lifting pattern improves. Cases that have been smouldering for more than six months, or that have already failed injection, tend to be slower and sometimes end up at a surgical consult.
Can I still pick up my baby?
Yes, but the technique needs to change. Scooping under the arms with the thumb sticking out is the exact movement that keeps irritating the tendons. I coach patients to scoop with a wider, forearm-supported lift, palm-up where possible, keeping the thumbs close to the side of the hand rather than flared out. Small changes to how you lift, burp, and feed add up quickly over a day.
Do I need surgery?
Usually not. Surgery to open the tendon tunnel (release of the first dorsal compartment) is an option when it is needed, but the path usually starts with conservative care: a thumb spica, activity change, and graded rehab, with a corticosteroid injection from a physician as an option early on or if symptoms persist. Surgery is reserved for people who have failed a proper trial of conservative care including injection, or for clear anatomical reasons, such as a separate section of the tunnel for one tendon (EPB) that keeps stopping injections from working.
The science
The Science of De Quervain's Tenosynovitis
De Quervain's is a stenosing tenosynovitis affecting the first dorsal compartment of the wrist, specifically involving the pollicis longus (APL) and extensor pollicis brevis (EPB) tendons. These tendons pass through a fibro-osseous tunnel bordered by the radial styloid process and overlying extensor . The condition represents inflammation and thickening of the tendon sheath (tenosynovium) that creates a progressive (narrowing) of the compartment, mechanically restricting tendon glide and causing friction-induced inflammation.
The pathophysiological cascade begins with repetitive mechanical irritation from thumb movements combined with wrist deviation. This creates microtrauma to the tendon sheath lining, triggering an inflammatory response with synovial thickening, edema, and fibrous tissue deposition. As the sheath thickens, the space available for tendon excursion diminishes, creating a vicious cycle where normal movements cause progressively more friction and inflammation. Histologically, the sheath shows chronic inflammatory changes, metaplasia, and myxoid rather than acute inflammation, explaining why anti-inflammatory medications have limited efficacy.
Anatomical variations influence susceptibility. Many people have more than one APL tendon slip, and a dividing wall (septum) that splits the first compartment is common: a 2022 review found one in 67% of people having surgery for De Quervain's, compared with 35% in the general cadaver population (Abi-Rafeh et al.). These septations create additional friction points and help explain why some cases respond poorly to injection, because the medication may not reach every subcompartment.
The condition shows strong demographic patterns: women are affected far more often than men, most commonly between their 40s and 60s. Pregnancy and early postpartum period represent particularly high-risk times due to hormonal influences on tendon and ligament combined with new repetitive infant care activities. Estrogen and relaxin affect metabolism and tendon material properties, potentially predisposing to inflammatory conditions. Risk factors include diabetes mellitus, rheumatoid , hypothyroidism, and previous wrist trauma or fracture.
The condition frequently coexists with other thumb including carpometacarpal (CMC) arthritis, intersection syndrome (inflammation where APL/EPB cross over wrist extensors), and syndrome. Differential diagnosis requires careful assessment as these conditions can produce overlapping symptoms but require different management approaches.
Contributing factors
The biomechanical drivers of De Quervain's center on repetitive thumb movements combined with ulnar deviation of the wrist, a movement pattern that maximally tensions and deviates the APL and EPB tendons through the first dorsal compartment. The classic provocative movement involves lifting or grasping with the thumb abducted while simultaneously bending the wrist toward the ulnar side (little finger direction). This combination creates maximum angulation and friction as the tendons change direction around the radial styloid process.
The "new mother" presentation is the archetypal example of biomechanical overload. Repeatedly lifting an infant requires sustained thumb and extension to support the baby's head and neck, combined with wrist ulnar deviation and slight flexion, the position that most loads the first compartment tendons. The "baby lift" movement performed dozens of times daily, often while sleep-deprived and with altered posture from breastfeeding, creates cumulative microtrauma exceeding tissue repair capacity. Symptoms often appear in the first months after delivery, when infant lifting demands peak.
Smartphone and texting activities contribute significantly to modern De Quervain's incidence. Thumb-intensive texting maintains the thumb in repetitive abduction and extension against resistance, while the wrist often adopts ulnar deviation to balance the device weight. Gaming with controllers requiring sustained thumb movements shows similar biomechanical loading. The sustained nature of these activities prevents adequate recovery periods between loading cycles, promoting chronic irritation of the tendon sheath.
Occupational activities create high-risk scenarios. Hairdressing requires sustained pinch grip with scissors while the wrist deviates to angle the cut, with thousands of repetitions daily with the thumb in sustained abduction against resistance. Gardening, particularly pruning with secateurs or hand shears, combines forceful pinch grip with wrist deviation. Assembly work requiring repeated thumb-operated tools (staplers, precision screwdrivers, tweezers) maintains continuous loading without relaxation. Even office work involving extended mouse use can contribute if the thumb maintains sustained extension to control buttons while the wrist adopts awkward postures.
Daily activities that seem innocuous create cumulative loading. Wringing towels or washcloths requires forceful pinch grip combined with repetitive twisting: the wrist moves into ulnar deviation as you wring, while the thumb works hard to maintain grip. Opening jar lids combines thumb abduction force with wrist torque. Lifting pots, pans, or kettles by their handles with thumb-up grip position loads the tendons maximally. Knitting and crochet maintain sustained thumb positioning with repetitive fine motor control requiring continuous APL/EPB activation.
The anatomical path of these tendons creates inherent vulnerability. As they travel from the forearm to the thumb, they must turn a sharp corner around the radial styloid through a narrow tunnel. Any movement combining thumb abduction with wrist ulnar deviation tightens this angle further, compressing the tendons against the radial styloid like a rope pulled taut around a pulley. The more acute the angle, the higher the friction and pressure within the compartment.
Grip technique and tool design influence loading. Larger diameter handles requiring wider thumb-finger spread increase APL/EPB activation compared to smaller diameter grips. Tools positioned to maintain neutral wrist position reduce tendon deviation through the first compartment compared to designs forcing wrist deviation. Power grip patterns (full hand around object) distribute forces across multiple tendons, while pinch grip patterns (thumb opposing fingers) isolate loading to thumb tendons including APL/EPB. Shoulder and shoulder blade control may also play a part in how much the thumb and wrist are asked to do.
Research
What the studies show
Injections guided by ultrasound were more accurate than injections guided by feel, and a dividing wall inside the tunnel is common in De Quervain's
A review that pooled studies on the use of ultrasound in De Quervain's (Abi-Rafeh and colleagues, Plastic and Reconstructive Surgery, 2022) found that a wall of tissue dividing the tendon tunnel (an intercompartmental septum) was clearly more common in people who had surgery for De Quervain's than in the general population studied in anatomy dissections (67% versus 35%). Cortisone injections guided by ultrasound were placed accurately more often than injections guided by feel (90 to 100% versus 40 to 100%), and were linked with better reported success rates (73 to 100% versus 59 to 83%).
If an injection is being considered, ultrasound guidance is worth asking the physician about, because a dividing wall in the compartment is common in people with De Quervain's.
Abi-Rafeh J, Mojtahed Jaberi M, Kazan R, et al. (2022). Utility of Ultrasonography and Significance of Surgical Anatomy in the Management of de Quervain Disease: A Systematic Review and Meta-Analysis. Plast Reconstr Surg. PMID: 35077418.
More people were treated successfully with a thumb splint plus a cortisone injection than with either one alone
A review that pooled trials (Cavaleri and colleagues, Journal of Hand Therapy, 2016) compared cortisone injection with hand therapy for De Quervain's. Both improved pain and function from the start, and across the trials neither made a clear difference over the other. However, clearly more people were treated successfully when a splint was combined with an injection than with a splint alone or an injection alone, which supports combining treatments without surgery.
Splinting and activity changes are a reasonable start, and when symptoms persist, combining a splint with an injection from a physician has the best support in this review.
Cavaleri R, Schabrun SM, Te M, et al. (2016). Hand therapy versus corticosteroid injections in the treatment of de Quervain's disease: A systematic review and meta-analysis. J Hand Ther. PMID: 26705671.
Related Conditions
Conditions I commonly see alongside, or confused with, this one.
Repetitive Strain Injuries
De Quervains is a repetitive strain injury affecting thumb tendons
Carpal Tunnel Syndrome
Both affect wrist structures; similar risk factors and can coexist
Golfer's Elbow
Both involve overuse of wrist/forearm muscles from gripping activities
Tennis Elbow
Wrist extension activities can stress both lateral elbow and thumb tendons
Getting back to it
Physiotherapy for de Quervain's tenosynovitis, built around the activity you want back.
