
ACL Injuries
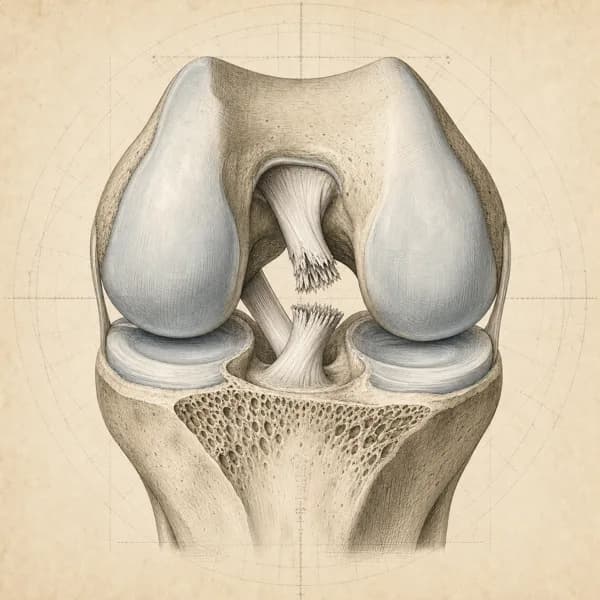
The ACL (anterior cruciate ligament) helps steady the knee by resisting forward movement and twisting of the shinbone. A tear often follows a sudden pivot or awkward landing and can cause a pop, rapid swelling or giving way. Treatment may involve rehabilitation alone or surgery; the exercise phases here describe rehabilitation after reconstruction.
Key points
- What usually helps
- Without surgery, training balance, landing and knee control step by step. After surgery, rehab guided by milestones.
- What you can do now
- Avoid twisting and sudden changes of direction. Keep up your strength and balance work.
- How long it takes
- Daily activities: 3 to 6 months without surgery. Sport after surgery: 9 to 12 months.
- When to see a doctor first
- Some signs need emergency care. Check the list before you start treatment.
Symptoms
Does this sound like you?
- Immediate swelling after injury
- A feeling of the knee giving way
- Difficulty with sudden changes of direction (cutting) or twisting on the leg (pivoting)
- Pain when fully straightening or fully bending the knee
- A sense that the knee is unstable
Often alongside it
- Weakness and loss of bulk in the front thigh muscle (quadriceps)
- Hip and ankle problems from moving differently to protect the knee
- Fear of re-injury
- Difficulty with stairs
- Doing less activity than before
It often starts with a sudden injury, a pop and swelling straight away. Afterwards, the knee may give way during sudden changes of direction. It may still work well for straight-line activities.Book an assessment for ACL injuries
When to see a doctor first
Go to emergency
After surgery: calf pain, swelling or warmth, or sudden shortness of breath or chest pain
Possible blood clot. Calf symptoms need same-day medical assessment; shortness of breath or chest pain means go to emergency now
The foot is cold, pale or numb, or the knee feels loose in several directions after a high-energy injury
Possible knee dislocation or injury to more than one ligament. Go to emergency now
Get seen today
You cannot take four steps on the leg after the injury, or there is sharp tenderness on the bone
Possible fracture. Same-day medical assessment for an X-ray
After surgery: a fever, or a wound that is red, hot, leaking or increasingly painful, or a knee that becomes hot and very swollen
Possible infection. Contact your surgical team the same day, or go to emergency
Check with your doctor
The knee locks and will not straighten
Possible meniscus tear blocking movement. See your family doctor or surgeon within a few days
The knee keeps giving way in daily activities despite rehab
Ask your family doctor for a referral to discuss surgery
Treatment
How it is treated
Main approach. For an ACL tear managed without surgery, training that builds up balance, landing and knee control step by step (neuromuscular training) can improve knee stability and function in a majority of cases, especially for recreational activities and straight-line sports.
Alongside it. Strengthening the front and back thigh muscles (quadriceps and hamstrings) restores strength and improves knee control, which is essential whether or not you have surgery.
Managing it over time. Injury prevention programs that teach safer landing and better knee control can meaningfully reduce the risk of ACL injury in sports with cutting and pivoting. A 2018 review that combined eight earlier reviews (Webster and Hewett) found these programs cut the risk of ACL injury by about half, mostly in studies of female athletes; there is too little data to say how well they work in male athletes.
A typical rehabilitation progression
Three phases, from settling symptoms to returning to full activity.
Recovery from ACL injuries is usually staged: calm the symptoms first, then rebuild the strength and capacity of the area, then return to your full activities. The phases below show how that can progress.
Phase 1Early Recovery After Surgery (Weeks 0 to 6 After ACL Reconstruction)
Protect the new ligament (the graft), get the knee fully straight to match the other side, reduce swelling in the joint, and get the front thigh muscle (quadriceps) switching on again. The 2023 Aspetar clinical guideline on rehab (Kotsifaki and colleagues) treats this as the phase for working on specific problems such as stiffness, swelling and weakness (the impairment-based phase). Not getting the knee fully straight in the early weeks is linked with poorer long-term results, so regaining it matters more than pushing the bend too fast.
Example exercises
- Quad sets (tightening the thigh muscle with the leg straight) and straight leg raises without the knee sagging (extension lag), to get the thigh muscle contracting on command again
- Heel hangs lying face down and heel props lying on your back, to regain full straightening of the knee, matching the other side
- Gently moving the kneecap in all four directions (patellar mobilizations) to prevent stiffness that limits the thigh muscle
- Stationary cycling once the knee bends to about 110 degrees, starting with a high seat and low resistance
- Wall sits and mini-squats with only part of your weight on the leg, within a range that causes no pain or swelling
Possible progression milestones
The knee straightens fully, matching the other side, and bends to nearly 120 degrees; little or no swelling in the joint; the thigh muscle contracts well, with no sag on a ; and pain-free walking without a brace or crutches, as set by the surgical protocol.
Phase 2Strength and Movement Control (Weeks 6 to Month 5)
Build real strength in both legs, regain control on one leg, and bring back running once the criteria are met. This is where most failed returns to sport are set in motion, because athletes often move on because time has passed rather than because of what the knee can do. Grindem and colleagues (2016) found that more even front thigh (quadriceps) strength between the legs before returning to sport was linked with a lower risk of injuring the knee again.
Example exercises
- Heavy, slow leg press, split squats and Romanian deadlifts, building toward the operated leg having more than 80 percent of the other leg's strength (limb symmetry index)
- Step-downs and single-leg squats, keeping the trunk steady and the knee from dropping inward
- Jump landings on two legs, progressing to small hops in place once the strength criteria are met (typically around month 3 to 4)
- A return to straight-line running once your surgical team has cleared it and proposed criteria are met, such as front thigh (quadriceps) strength above 80 percent of the other side (2023 Aspetar guideline), a knee that straightens fully, a knee free of pain and swelling, and pain-free hopping in place on one leg
- Balance and control training (neuromuscular training), including drills where you hold steady against pushes or a moving surface, balance board work, and reacting quickly to keep the knee stable
Possible progression milestones
Front thigh (quadriceps) strength about 90 percent of the other side on a strength-testing device (dynamometer), pain-free running at a moderate pace, a single-leg squat with good control, and no swelling after loading.
Phase 3Return to Sport and Performance (Month 6 to 12+)
Complete a set of return-to-sport tests before cutting, pivoting and contact are cleared. Grindem and colleagues (2016) found the reinjury rate dropped by 51 percent for each month return to sport was delayed, up to 9 months, and that athletes who passed the return-to-sport criteria had fewer reinjuries. Measurable criteria, not a date on the calendar, drive the decision.
Example exercises
- The full set of return-to-sport hop tests (single hop for distance, triple hop, crossover hop and 6 metre timed hop), aiming for the operated leg to reach at least 90 percent of the other leg (limb symmetry index)
- Strength testing of the front and back thigh muscles with a machine or handheld device (dynamometry), aiming for at least 90 percent of the other leg
- Progressive agility and change-of-direction drills: T-drill, 5-10-5 shuttle, cutting at 45 then 90 degrees, reactive cutting with a partner
- Sport-specific jumping and landing drills () and slowing-down training, including drop jumps and bounding
- A questionnaire on how mentally ready you feel to return (the ACL Return to Sport after Injury scale, ACL-RSI), alongside the performance criteria
Possible progression milestones
At least 90 percent of the other leg on front and back thigh strength and on all four hop tests, at least 9 months since the reconstruction, a mental readiness score (ACL-RSI) that supports returning, and full training completed without pain or swelling.
What you can do now
- Avoid twisting and sudden changes of direction. Avoiding sudden changes of direction (cutting) and twisting on the leg (pivoting) reduces episodes of the knee giving way. If your knee is managed without surgery, you may need to change how you take part in sport.If the knee keeps giving way in daily activities despite rehab, ask your family doctor for a referral to discuss surgery.
- Keep up your strength and balance work. Strong front and back thigh muscles help make up for the injured ligament, and balance and control training builds knee control, whether or not you have surgery. Many people do well with structured rehab alone, and the decision about surgery depends partly on how the knee responds to a 3 month trial of steadily increasing exercise.
- After surgery, get the knee fully straight. In the early weeks after reconstruction, regaining full straightening, matching the other side, matters more than pushing the bend too fast, because not getting it back is linked with poorer long-term results. Follow your surgical team's protocol for what to do and when.Do not return to running or pivoting until your surgical team has cleared it and you meet the strength and control milestones, not just the calendar.
- Know the warning signs after surgery. After surgery, calf pain, swelling or warmth needs a same-day medical assessment, and sudden shortness of breath or chest pain means go to emergency now. A fever, a wound that is red, hot, leaking or increasingly painful, or a knee that becomes hot and very swollen means contact your surgical team the same day, or go to emergency.
What I use in clinic
- Balance and Control Training (Neuromuscular Training). Balance, landing and cutting drills build knee control for return to sport, and injury prevention programs built on them are linked with fewer ACL injuries in team sports.
- Progressive Strengthening. Strength in the front and back thigh muscles (quadriceps and hamstrings) matters a great deal for knee stability. Strong muscles help make up for the injured ligament, so the load is built up step by step.
Recovery
How long it takes
Without surgery, getting back to daily activities typically takes 3 to 6 months. After surgery, returning to sport typically takes 9 to 12 months.
Without surgery, the knee can function well if you are willing to change some activities. In the long term, the risk of meniscus tears and arthritis is higher.
What changes the timeline
- What you need the knee to do shapes the choice of treatment
- Other injuries in the knee at the same time affect the timeline
- Keeping up with rehabilitation matters a great deal
- Age and how active you were before the injury are important
How I track it. I track how much the pain gets in the way of the tasks that matter to you, how well you move when I test those tasks in clinic, and how confident you feel in daily activities
Similar conditions
Conditions that can feel similar
- Medial Meniscus Tear
- Tenderness along the joint line, catching or locking, and pain on twisting and bending tests (McMurray or Thessaly tests). It often happens together with an ACL injury (the O'Donoghue triad), but it can occur on its own after a twist, with less dramatic swelling at first.
- MCL Sprain
- The knee is pushed inward (a valgus force). Tenderness runs along the inner joint line and the ligament. Pushing the knee inward with it bent about 30 degrees is painful and shows looseness (laxity). Swelling is usually more localized, and less of it sits inside the joint than with an ACL tear.
- PCL Injury
- The shin bone moves or sags backward on testing (posterior drawer test and sag sign), often after a dashboard injury or a fall onto a bent knee. Pain is more often at the back of the knee, and early bleeding into the joint (hemarthrosis) is less dramatic than with an ACL rupture.
- Patellar Dislocation or Subluxation
- The kneecap shifts out to the side at the time of injury, and the inner edge of the kneecap is tender (over the medial patellofemoral ligament). The person becomes apprehensive when the kneecap is pushed outward (apprehension test). The swelling can look like an ACL tear, but the injury is usually a direct blow or a twist with the kneecap moving out to the side.
- Tibial Plateau Fracture
- A high-energy injury, being unable to take weight on the leg, marked tenderness over the bone, and swelling in the joint that may contain blood and fat from the bone (lipohaemarthrosis). It needs imaging to diagnose and must be ruled out before rehab loading starts.
- Posterolateral Corner Injury
- The outer side of the knee opens up when the knee is pushed outward (varus instability), and the shin turns outward further than normal with the knee bent 30 degrees (dial test). It is often missed when it happens on its own. It can happen together with an ACL or PCL injury, and it changes surgical planning if present.
Commonly confused with
Side-by-side comparisons for patterns that often get mistaken for ACL injuries.
Questions
What patients ask me most
Do I need surgery for an ACL tear?
Not automatically. Many people do well with structured rehabilitation alone, particularly if they do not return to cutting, pivoting, or contact sports. The Delaware-Oslo ACL cohort (Grindem et al., OJSM 2018) reported that a little over half of highly active ACL-injured patients who chose progressive rehabilitation without reconstruction had a successful 2-year outcome and knee function comparable to uninjured peers. The decision depends on your goals, knee stability on testing, associated meniscus or cartilage injuries, and how your knee responds to a 3 month trial of progressive loading.
Can you live without an ACL?
Yes, many people do. The ACL is one of the main structures that stops the shin bone sliding forward and twisting under the thigh bone, so the challenge is controlling the knee when you change direction or twist on it. People often grouped as 'copers' regain function through progressive strengthening and balance and control training (neuromuscular training). 'Non-copers' tend to have episodes of the knee giving way and may benefit from reconstruction. Who will cope cannot reliably be predicted at the time of injury, which is why a structured rehab trial before deciding on surgery is evidence-based.
How long is ACL surgery recovery?
Return to sport is typically 9 to 12 months after reconstruction, not the 6 months sometimes quoted. The Aspetar 2023 clinical practice guideline on ACL rehabilitation (Kotsifaki et al., BJSM) recommends moving on only when set criteria are met, through phases that restore strength and movement, then sport-specific work, then return to play, rather than following a fixed timeline. Grindem et al. (BJSM 2016) found that each month return to sport was delayed up to 9 months reduced the reinjury rate by 51 percent, and that athletes who failed the return-to-sport criteria had far more reinjuries than those who passed. Daily activities return much earlier, usually within 3 months.
What are the chances of reinjury after ACL reconstruction?
Higher than most people realize. Wiggins et al. (AJSM 2016) pooled data showing a 21 percent second ACL injury rate in patients under 25, rising to about 23 percent in athletes under 25 who return to high-risk sport. Those figures count both a tear of the new ligament (the graft) in the same knee and an ACL tear in the other knee. Kyritsis et al. (BJSM 2016) found athletes who failed six return-to-sport discharge criteria had roughly a four-fold higher rate of graft tears. This is why I emphasise meeting objective discharge criteria, not just feeling ready, before clearing return to sport.
When can I run after ACL surgery?
Typically between 12 and 16 weeks after reconstruction, but only once criteria are met, not purely by the calendar. Running starts only after agreed clinical and strength criteria are met and your surgical team has cleared it. The Aspetar 2023 guideline proposes front thigh (quadriceps) strength above 80 percent of the other side, together with a knee that fully straightens, minimal swelling and pain-free relevant loading such as hopping in place. These are proposed criteria, not a guarantee of safety, and symmetry alone can mislead when both legs have lost strength. Running too early on a weak quadriceps is a common reason rehab stalls.
Do all ACL tears need an MRI?
MRI is the preferred imaging when an ACL injury is suspected on examination, because it also shows the meniscus, cartilage and any bone bruising, which influence management. A skilled hands-on examination that checks how far the shin bone moves forward and whether the knee shifts as it bends (the Lachman, pivot shift and anterior drawer tests) is highly accurate for complete ACL ruptures in the right hands. If your history and exam are clearly consistent with an ACL tear and you are going ahead with rehab, imaging is usually still done to check for other injuries that would change the plan.
Can physio fix a partial ACL tear?
Partial ACL tears are a mixed group, and outcomes depend on how much of the ligament is still intact, how stable the knee is in everyday use, and what you need the knee to do. Many partial tears respond well to progressive strengthening, balance and control training (neuromuscular training) and a return to activity guided by set criteria, without surgery. Some progress to full tears, particularly in athletes whose sports involve pivoting. I reassess stability and function throughout rehab and involve an orthopaedic consultation if the knee continues to give way despite appropriate loading.
The science
The Science of ACL Injuries
The ACL () is crucial for knee stability, preventing the tibia from sliding forward. Tears usually occur during cutting, pivoting, or landing movements. The ligament has poor blood supply, limiting natural healing capacity.
After injury, the knee loses rotational stability, leading to episodes of giving way and potential damage to other structures like the and cartilage. ACL injuries significantly increase the long-term risk of developing knee , even with successful surgical reconstruction. Concurrent injuries such as meniscus tears or /LCL sprains are common and require comprehensive management alongside ACL rehabilitation.
Contributing factors
Many injuries happen without direct contact to the knee, during cutting, jumping, or landing. Injury risk reflects several factors, including the sport, fatigue, strength and movement, and some of these can be changed with training. A pattern often described in research combines the knee caving inward (), landing with the knee fairly straight, and the foot planted away from the body's centre of mass, which can place high rotational and shearing loads on the ligament.
Landing mechanics matter. Landing from a jump with straight or minimally bent knees leaves less of the force shared through the hips and ankles. Female athletes have a higher rate of ACL injury in many sports, for a mix of reasons that are still being studied, and movement differences may be one part of it. Leaning the trunk sideways over one leg can add to the load.
The "position of no return" happens during cutting movements when your foot plants and your knee starts to collapse inward while your body continues moving in a different direction. This typically occurs in the first 50 milliseconds of the movement, faster than you can consciously react. Hip strength may play a part, because the glutes help control thigh position, and fatigue can make control harder late in games or training sessions. These are reasons to train strength and movement, not a way to blame anyone for an injury.
Research
What the studies show
Aspetar clinical practice guideline on rehabilitation after ACL reconstruction
Exercise is the main part of rehab after ACL reconstruction, with other treatments (modalities) as an early add-on when pain, swelling or limited knee movement hold exercise back. Return to running and return to training are the key milestones, but the guideline found no evidence on which criteria should decide progression or discharge, and it rated the certainty for most parts of rehab as very low, so most of its recommendations rest on agreement among the guideline panel. Rehab before surgery might improve knee movement and front thigh (quadriceps) strength afterwards.
Gives a current framework for rehab after ACL reconstruction, built largely on agreement among the guideline panel. Progress is judged on how the knee is doing as well as time since surgery, because the new ligament (graft) needs a minimum time to heal and no single set of criteria has been shown to be best.
Kotsifaki R, Korakakis V, King E, et al. Aspetar clinical practice guideline on rehabilitation after anterior cruciate ligament reconstruction. Br J Sports Med. 2023;57(9):500-514. PMID: 36731908.
Adding specific exercise therapy after ACL surgery: a review of 11 trials
Adding specific exercise therapy (such as vibration training, core training, strength training, blood flow restriction training and aquatic training) to rehabilitation after ACL surgery was associated with better knee function, less pain and better muscle strength across 11 randomised trials.
Supports a structured, progressive exercise program after ACL reconstruction.
Zhou H, Qian J, Xing YM, Cui L, Bu YF. How effective is the addition of specific exercise therapy for patients after anterior cruciate ligament surgery? A systematic review and meta-analysis. Front Physiol. 2025;16:1501458. PMID: 39927331.
Guides on knee pain
Longer explanations of symptoms and scan-report wording.
- Pain Right Below the KneecapA single tender spot below the kneecap that flares with jumping, stairs, or deep squats. Most commonly patellar tendinopathy in active adults, and growth-plate conditions in young athletes.
- Suprapatellar Effusion (Fluid on the Knee)Extra fluid inside the knee joint, seen in the pouch above the kneecap. What the size words on a report mean, the usual causes by how quickly the swelling came on, and when to see a doctor first.
- Joint Space Narrowing in the KneeThe gap between the bones looks thinner than expected on an X-ray. What medial, tricompartmental and the severity words mean, how it relates to pain, and what the guidelines recommend.
Related Conditions
Conditions I commonly see alongside, or confused with, this one.
Knee Osteoarthritis
ACL injuries increase risk of early knee arthritis due to altered mechanics
Patellar Tendinopathy (Jumper's Knee)
Both common in jumping sports; altered knee mechanics can affect patellar tendon
Ankle Sprains
Both involve knee/ankle stability; ankle instability can predispose to ACL injury
Patellofemoral Pain (Kneecap Pain)
Getting back to it
Physiotherapy for ACL injuries, built around the activity you want back.
