
Rotator Cuff Injuries
The rotator cuff is a group of muscles and tendons that steady the shoulder and help lift and turn the arm. Problems include tendon pain and partial or full tears. Reaching overhead and lying on that side often hurt. This page also discusses recovery after surgical repair, which needs a separate rehabilitation plan.
Key points
- What usually helps
- Strengthening built up step by step. Many people avoid surgery, and a surgical opinion is discussed for some tears.
- What you can do now
- Support the arm when you sleep. Start with static holds.
- How long it takes
- Some improvement within 2 to 4 weeks; full function usually takes 3 to 6 months.
- When to see a doctor first
- Some signs need emergency care. Check the list before you start treatment.
Symptoms
Does this sound like you?
- Shoulder pain, especially with overhead activities
- Weakness when lifting or turning the arm
- Night pain when lying on the sore side
- Difficulty reaching behind your back
- Pain through the middle range as you lift the arm out to the side (a painful arc, about 60 to 120 degrees)
Often alongside it
- Clicking or catching sensations
- Neck and upper back tension from working around the sore shoulder
- Gradual loss of shoulder movement
- Muscle wasting when it has gone on for a long time
- Difficulty with daily tasks like dressing
Pain comes with particular movements rather than being constant. Overhead activities and reaching behind you are especially hard. Night pain is common.
Before using this comparison, check when these symptoms need a doctor first.
When to see a doctor first
Go to emergency
Shoulder or arm pain with chest pain, shortness of breath, sweating or nausea, or pain that comes on with exertion and eases with rest
Call 911. Heart problems can show up as shoulder pain
A hot, red, swollen shoulder, or shoulder pain with fever or feeling unwell
Go to emergency now
Get seen today
A fall or blow followed by severe pain, a change in the shape of the shoulder, or being unable to lift the arm
Same-day medical assessment to rule out a fracture or dislocation
Check with your doctor
Sudden weakness after an injury, so you cannot lift the arm, especially if you are under 65
See your family doctor within a few days. An early imaging and surgical opinion matters for a fresh tear
Shoulder pain with a history of cancer, unexplained weight loss, or constant pain at night that does not ease with position
See your family doctor before starting physiotherapy
Treatment
How it is treated
Main approach. Strengthening exercise, built up step by step, is the usual first treatment for rotator cuff pain and for many tears that came on gradually, and many people avoid surgery. Repair can offer an advantage for some tears, so I discuss a surgical opinion when the type of tear or your progress makes it relevant. A sudden injury that leaves you unable to lift the arm is different, and I refer on quickly.
Alongside it. Shoulder blade exercises can help as part of the program, so the rotator cuff and the shoulder blade muscles share the load in daily activities.
Managing it over time. Keeping up some shoulder strengthening after the pain settles, and building up overhead work gradually, may lower the chance of a flare.
A typical rehabilitation progression
Three phases, from settling symptoms to returning to full activity.
Recovery from rotator cuff injuries is usually staged: calm the symptoms first, then rebuild the strength and capacity of the area, then return to your full activities. The phases below show how that can progress.
Phase 1Settling Pain and Starting to Load
Settle symptoms, protect sleep, and start putting load through the tendon in a way it tolerates. A static hold, where the muscle works without the arm moving (an ), can be a manageable way to begin when movement is painful. It eases pain for some people, but the effect varies, so I set the effort and hold time by how your shoulder responds and use another option if it aggravates symptoms. The 2022 clinical guideline for problems (Lafrance and colleagues) recommends active rehabilitation with exercise and education rather than rest.
Example exercises
- Static hold turning the arm outward (isometric external rotation), elbow at your side, pressing into a wall or doorframe: hold 30 to 45 seconds, 4 to 5 repetitions, daily
- Static holds pressing the arm out to the side () and turning it inward (internal rotation), at a moderate, comfortable effort with no sharp pain
- Shoulder blade setting drills (gently drawing the shoulder blade back and down) and low-row band holds, to restore control of the muscles at the back of the shoulder
- Moving the arm yourself, without pain, forward, out to the side and in rotation, to keep the shoulder moving
- Advice on changing activities: taking out, for now, the particular overhead tasks or end-of-reach positions that set off flare-ups
Possible progression milestones
Night pain becoming manageable, low pain at rest, and the static holds feeling comfortable without a flare that lasts into the next day.
Phase 2Progressive Loading
Build up how much load the tendon and the rest of the cuff can handle, using resistance that increases over time. In a small trial (the SELF study, Littlewood and colleagues 2016), a single exercise done at home and made gradually harder gave results similar to usual physiotherapy for rotator cuff tendon pain (). The aim is enough load for the tendon to adapt, increased steadily rather than staying on light bands indefinitely.
Example exercises
- Turning the arm outward against a dumbbell or band, elbow at your side (external rotation), 3 sets of 8 to 12 reps, taking a controlled 3 seconds to return to the start (the phase)
- Side-lying external rotation (lying on your side and turning the top arm outward with a dumbbell), increased weekly by small dumbbell increments
- Y, T and W arm lifts lying face down, and face-down rows, for the muscles that steady the shoulder blade
- Cable or band rows at chest height, focusing on drawing the shoulder blades back (retraction) and turning the arm outward
- Loaded carries (walking with a weight in each hand, the farmer carry, or in one hand, the suitcase carry) to train the shoulder and shoulder blade to stay steady while moving under load
Possible progression milestones
Outward rotation strength getting closer to the other side, a moderate dumbbell moved through full range without painful catching, and overhead reach for daily tasks without hitching the shoulder.
Phase 3Return to Overhead, Sport, and Heavier Work
Rebuild the shoulder's ability to handle overhead work, faster movements and load at the end of its reach. Later rehabilitation helps prepare the shoulder for the demands you want to return to, and I progress it on how the shoulder performs (strength, control and confidence) rather than on the calendar. A flare can still happen after a well-completed program, particularly with heavy overhead sport or work; if it does, I review the plan with you.
Example exercises
- Overhead press progressions, starting with a landmine press (pressing up one end of a barbell whose other end is anchored at the floor) and moving on to full overhead dumbbell and barbell presses
- Pulling variations: pull-ups with assistance as needed, lat pulldowns, and weighted rows
- Fast throwing and catching work for the rotator cuff (), such as medicine ball chest passes, overhead throws and rebounder drills (throwing a ball against a small trampoline), for throwing athletes
- Drills for your sport or job (throwing technique, swim stroke, overhead lifting), with the amount built up gradually
- Strength work at the end of the shoulder's reach: holding weight fully overhead, Turkish get-ups (getting up from lying to standing while holding a weight overhead), and bottoms-up kettlebell work (holding a kettlebell upside down by its handle), for steadiness with the arm at full stretch
Possible progression milestones
Strength close to the other side on rotation, lifting and pressing, sport or job demands managed at the usual volume without pain, and confidence in the shoulder during unplanned or reactive movements.
What you can do now
- Support the arm when you sleep. Sleep on the other side with the sore arm supported forward on a pillow, or on your back with a small pillow under the elbow. This takes load off the shoulder, and night pain often eases over a few weeks as it settles.Avoid lying directly on the sore shoulder, and avoid sleeping on your stomach, which usually makes shoulder symptoms worse. Constant pain at night that does not ease with any position is one of the warning signs on this page: see your family doctor before starting physiotherapy.
- Start with static holds. Press the arm outward into a wall or doorframe with the elbow at your side, so the cuff muscles tighten without the arm moving. The first rehab phase on this page uses holds of 30 to 45 seconds, 4 to 5 repetitions, daily, at a moderate, comfortable effort.Stop if a hold causes sharp pain or leaves a flare that lasts into the next day.
- Keep lifting, below shoulder height. Completely resting a painful tendon tends to leave it weaker. Early on, drop overhead pressing, upright rows and behind-the-neck movements, and keep loaded work below shoulder height.Bring overhead lifting back gradually as symptoms settle and strength returns. If you suddenly cannot lift the arm after a fall or a sudden pull, see your family doctor within a few days, as the warning signs on this page describe.
- Change arm position often. Holding the arm in one position for long spells, especially reaching forward or overhead, tends to aggravate a sensitive cuff. Short, regular breaks matter more than a perfect posture.
- Pace your good days. Avoid the cycle of doing too much on good days and then flaring up. Building back up gradually gives the tendon time to adapt.Avoid sudden increases in overhead activity.
What I use in clinic
- Progressive loading exercise. For many tears that came on gradually (degenerative tears), a structured strengthening program can help and many people avoid surgery. For small to medium tears, one long-term trial found repair gave better results at 15 years, so surgery stays an option for selected tears.
- Shoulder blade (scapular) control exercises. Part of the program. In athletes without pain, altered shoulder blade movement was linked to a 43% higher risk of later shoulder pain (Hickey and colleagues, BJSM 2018).
- Hands-on treatment (manual therapy). Can help restore movement and reduce pain when combined with exercise.
- Steroid injection compared with exercise. An injection gives better relief for the first 6 to 8 weeks, but no long-term advantage over exercise alone.
Recovery
How long it takes
Recovery is usually measured in months, not weeks. Most people notice some improvement within 2 to 4 weeks and substantial improvement by 6 to 8 weeks, and a return to full function usually takes 3 to 6 months.
Most people improve with treatment that does not involve surgery. Many partial tears become pain-free with rehabilitation. A complete tear may not heal, but the shoulder can still become pain-free and work well for daily life.
What changes the timeline
- Having symptoms for more than 3 months predicts a slower recovery
- More pain and difficulty with daily tasks at the start calls for more intensive treatment
- Stress at work and little support from others (psychosocial factors) substantially affect how well you recover
- The size and location of a tear affect the timeline
- Smoking can slow tendon healing
How I track it. I track your pain during daily activities, how far the arm moves, and gains in strength
Similar conditions
Conditions that can feel similar
- Frozen Shoulder (Adhesive Capsulitis)
- When the arm is turned outward for you with the elbow at your side, it is markedly stiff and stops firmly because the joint capsule is tight, not just because it hurts. With a rotator cuff problem the shoulder typically still moves fully when someone else moves it, and the signs are a painful arc or weakness against resistance rather than stiffness in every direction.
- Subacromial Pain Syndrome / Bursitis
- Pain through the middle range of lifting the arm out to the side (a painful arc, 60 to 120 degrees). Pain when the arm is raised or turned in set positions (Neer and Hawkins-Kennedy tests), and relief after a numbing injection under the point of the shoulder (subacromial). Often overlaps with rotator cuff tendon pain, but scans show the tendon is intact.
- Biceps Tendinopathy
- Pain at the front of the shoulder over the groove the biceps tendon runs in (bicipital groove). Pain when bending the elbow or turning the palm up against resistance (Speed and Yergason tests). Rotator cuff pain more often spreads to the outer upper arm with resisted rotation, although the two often overlap and can occur together.
- AC Joint Pathology
- Pain pinpointed at the top of the shoulder over the AC joint, which is tender to press. Reaching the arm across the body brings it on (cross-body adduction test). Testing the cuff against resistance is often pain-free, which helps tell it apart from a cuff problem, although the two can coexist.
- Cervical Radiculopathy (C5-C6)
- Arm pain that follows the path of one nerve from the neck (a dermatomal pattern). Tilting the head and pressing down on it brings on the arm pain (Spurling test), and there may be nerve signs such as a changed reflex or weakness in particular muscles. The shoulder moves fully when moved for you, and testing the cuff against resistance is usually pain-free.
- Glenoid Labral Tear (SLAP or Anterior Lesion)
- Deep clicking or clunking with overhead movement, and a feeling the shoulder is unstable or might slip out. Holding the arm in set positions brings on the pain or that feeling (O'Brien or apprehension tests). More common in younger throwing athletes than in middle-aged people with wear-related cuff problems.
- Glenohumeral Osteoarthritis
- Grinding or crackling with movement (crepitus) rather than catching. X-rays show a narrowed joint space and bone spurs (osteophytes). Movement is lost both when you lift the arm yourself and when it is moved for you. Usually appears later in life and develops gradually over a decade or more.
Commonly confused with
Side-by-side comparisons for patterns that often get mistaken for rotator cuff injuries.
Questions
What patients ask me most
How do I know if my rotator cuff is torn?
The pattern I look for is weakness that is out of proportion to pain, especially when I test one tendon against resistance, plus a story of sudden loss of strength or long-standing trouble with overhead use. Classic signs include the arm dropping when you try to lower it slowly from shoulder height (a drop-arm test), weakness turning the arm outward against resistance, or difficulty lifting the arm overhead without hiking up the shoulder blade. Clinical tests are imperfect, so when knowing whether there is a tear would change the plan, I flag it to your family doctor or specialist and refer you for an ultrasound or MRI.
Can a torn rotator cuff heal without surgery?
Many tears can become pain-free and functional without surgery, even if the tendon itself does not knit back together. In the MOON Shoulder Group cohort (Kuhn and colleagues, JSES 2013), about 75% of people with atraumatic full-thickness tears had not had surgery two years after a structured exercise program, and at ten years physical therapy was still successful for more than 70% (Kuhn and colleagues, JBJS 2024). Trial data add nuance. Moosmayer and colleagues randomised 103 people with small to medium tears (up to 3 cm) to tendon repair or physiotherapy, and at 15 years repair gave better shoulder scores, less pain and more pain-free movement, while unrepaired tears had on average grown (JBJS 2024). So many atraumatic tears can be managed without surgery and stay functional, but repair may offer an advantage for selected tears, especially over the long term. Traumatic tears in younger, active people are a different conversation, and I refer on promptly when that applies.
What makes rotator cuff pain worse at night?
Night pain is common with rotator cuff problems. Lying on the sore side or holding the arm in one position for a long time can aggravate it, but position is not the whole explanation, and a sensitive tendon can simply be more irritable at rest. I usually suggest sleeping on the other side with the sore arm supported forward on a pillow, or on your back with a small pillow under the elbow. Night pain often eases over a few weeks as the shoulder settles, though how quickly varies. Severe, constant pain that does not change with position needs a medical review.
How long to recover from rotator cuff surgery?
Full recovery after arthroscopic rotator cuff repair generally takes 6 to 12 months, not the 6 weeks patients often expect. Typical milestones, in line with the American Society of Shoulder and Elbow Therapists' consensus statement on rehabilitation after arthroscopic rotator cuff repair (Thigpen and colleagues, J Shoulder Elbow Surg 2016), are: an early period of relative immobilisation, where the arm is only moved gently for you to protect the repair (protected passive range), restoration of active range of motion, progressive strengthening generally introduced around 12 weeks, and a staged return to higher demand activity over the following months. Re-tear rates in the literature range widely depending on tear size and patient factors, which is why graded loading matters.
Is it safe to lift weights with a rotator cuff injury?
Often yes, with modifications. Completely resting a painful tendon tends to leave it weaker still (deconditioning). Research from Littlewood and Lewis supports progressive loading as a core treatment. Early on I usually cut overhead pressing, upright rows, and behind-the-neck movements, keep loaded work below shoulder height, and add static cuff holds (isometrics) and shoulder blade work. As symptoms settle and strength returns, I progressively reintroduce overhead loading.
Do MRIs always show a torn rotator cuff?
MRI is sensitive, but the bigger issue is the reverse: scans often show cuff changes in people with no shoulder pain. A 2014 review that pooled 30 studies (Teunis and colleagues) found rotator cuff abnormalities on scans in about 10% of people aged 20 and younger, rising to about 62% of those aged 80 and older, and a similar rise with age whether or not people had symptoms. So a scan has to be read alongside your symptoms and examination, and a tear on an image does not automatically mean surgery is needed.
Can rotator cuff injuries heal on their own?
Tendinopathy and partial tears often improve with appropriate loading, activity modification, and time, but unlike a bone, a structurally torn tendon does not reliably knit back together. What research does show is that pain and function can improve substantially even when the tear itself persists, because you are retraining the rest of the cuff and the shoulder blade muscles to share the load. Leaving symptoms entirely untreated tends to lead to moving around the problem and to stiffness that follows from it.
Why do I feel weakness but no pain after a sudden injury?
Painless weakness after a fall or sudden pull on the arm is a finding I take seriously. It can indicate a full-thickness traumatic rotator cuff tear, especially in patients under 65 who suddenly cannot lift the arm to shoulder level. Evidence suggests an earlier surgical opinion in this group improves outcomes, as the torn tendon pulls back and the muscle is gradually replaced by fat over months (fatty infiltration). In that situation I will refer for imaging and orthopaedic review quickly rather than watch and wait.
The science
The Science of Rotator Cuff Injuries
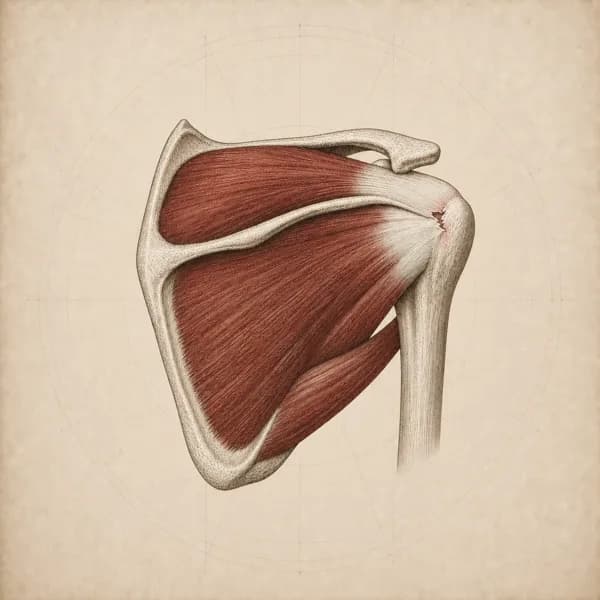
The consists of four muscles that stabilize and move your shoulder. These tendons can be injured through sudden trauma or gradual wear. The tendon tissue becomes disorganized and may develop tears.
Tendons adapt slowly, so healing takes months rather than weeks. Rotator cuff pain, shoulder and what used to be called are now usually grouped as rotator cuff related shoulder pain, because they overlap and respond to the same loading approach.
Contributing factors
Most pain is a load problem: the tendons are asked to do more than they are currently ready for. A jump in overhead work, a new sport or training block, a weekend of painting a ceiling, or a busy spell after weeks of less activity are the common stories.
The older idea that the tendons are pinched under the with every movement does not match the research. Bone shape and resting posture do not predict who gets pain, and surgery to make more space did no better than placebo surgery (CSAW trial, Beard and colleagues, Lancet 2018). What does matter is capacity: how much load the cuff and shoulder blade muscles can tolerate, and how quickly that load was increased.
Age plays a part, because tendons change over the decades and cuff changes are common on scans of pain-free shoulders. Smoking, diabetes, poor sleep and stress can also slow recovery.
Research
What the studies show
Exercise and other non-surgical treatments for shoulder impingement: a review of trials
This review pooled randomised trials in adults with shoulder impingement. Exercise reduced pain more than comparison treatments that did not include exercise, and exercises aimed at the problem did better than general exercises. Adding hands-on treatment (manual therapy) to exercise gave a small extra benefit in the short term. The authors concluded that exercise should be considered for people with impingement symptoms, though the overall quality of the evidence was low.
Supports targeted exercise with load as a first approach without surgery for shoulder impingement, which often overlaps with rotator cuff tendon pain.
Steuri R, Sattelmayer M, Elsig S, et al. Effectiveness of conservative interventions including exercise, manual therapy and medical management in adults with shoulder impingement: a systematic review and meta-analysis of RCTs. Br J Sports Med. 2017;51(18):1340-1347. PMID: 28630217.
Rehabilitation after keyhole rotator cuff repair: a consensus statement from shoulder and elbow therapists
A group of clinicians from several professions agreed how rehabilitation after keyhole rotator cuff repair should run. Controlled stress is applied to the healing repair gradually, taking account of the tear size, the quality of the tissue and the person. The framework includes about two weeks of strict immobilisation (keeping the arm still), then gentle movement done for you to protect the repair (protected passive range of motion) through roughly weeks two to six, then getting back the movement you make yourself, and strengthening that builds up from around week twelve after surgery, followed by a staged return toward demanding activity.
Guides rehabilitation after surgery, with stages that follow tissue healing and move on when set milestones are met.
Thigpen CA, Shaffer MA, Gaunt BW, et al. The American Society of Shoulder and Elbow Therapists' consensus statement on rehabilitation following arthroscopic rotator cuff repair. J Shoulder Elbow Surg. 2016;25(4):521-535. PMID: 26995456.
Related Conditions
Conditions I commonly see alongside, or confused with, this one.
Getting back to it
Physiotherapy for rotator cuff injuries, built around the activity you want back.
