
Frozen Shoulder
Frozen shoulder (adhesive capsulitis) causes pain and restricted movement as the capsule around the shoulder joint tightens. Night pain is common, and turning the arm outward is often especially limited. Symptoms can change over months or years, without following neat stages. It is more common in people with diabetes.
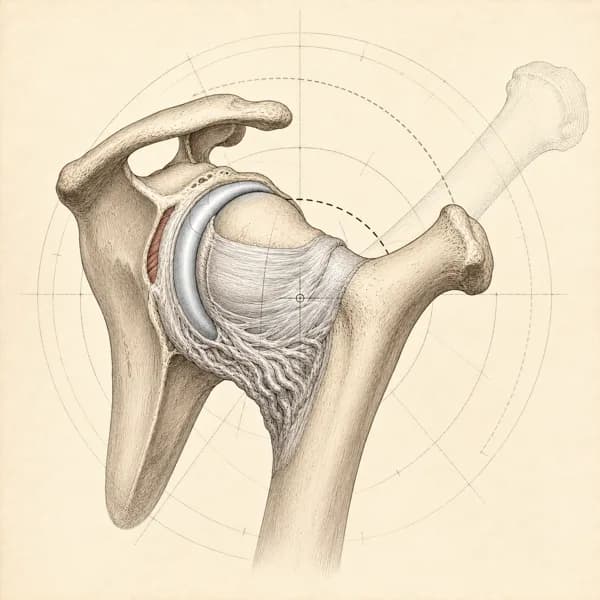
Key points
- What usually helps
- Physiotherapy matched to how painful and how stiff the shoulder is right now.
- What you can do now
- Use the traffic-light rule when stretching. Move it little and often.
- How long it takes
- Often many months, sometimes longer, with plateaus and flare-ups along the way.
- When to see a doctor first
- Some signs need emergency care. Check the list before you start treatment.
Symptoms
Does this sound like you?
- Shoulder movement that is gradually lost
- Pain with movement in all directions
- Night pain disturbing sleep
- Unable to reach behind your back or overhead
- Difficulty with dressing and grooming
Often alongside it
- Neck and back pain from working around the stiff shoulder
- Arm weakness from using it less
- Low mood or frustration at what you cannot do
- Elbow and wrist stiffness
- Overusing the other shoulder
Comes on gradually without a clear cause. Movement becomes more limited over months. Turning the arm outward is typically the most limited.
Before using this comparison, check when these symptoms need a doctor first.
When to see a doctor first
Go to emergency
Shoulder or arm pain with chest pain, shortness of breath, sweating or nausea, or pain that comes on with exertion and eases with rest
Call 911. Heart problems can show up as shoulder pain
A hot, red, swollen shoulder, or shoulder pain with fever or feeling unwell
Go to emergency now
Get seen today
Stiffness and pain that started after a fall or blow
Same-day medical assessment to rule out a fracture or dislocation
Check with your doctor
Shoulder pain with a history of cancer, unexplained weight loss, or constant pain at night that does not ease with position
See your family doctor before starting physiotherapy
Treatment
How it is treated
Main approach. Physiotherapy matched to how painful and how stiff the shoulder is now can help pain and function while the condition changes, which often takes many months.
Alongside it. Joint mobilization and stretching within comfort may help range of movement, with the intensity matched to how irritable the shoulder is.
Managing it over time. Frozen shoulder coming back in the same shoulder is uncommon, and there is no established way to prevent it in the other one. If stiffness is building, an assessment can clarify the cause and help you manage pain and daily tasks.
A typical rehabilitation progression
Three phases, from settling symptoms to returning to full activity.
Recovery from frozen shoulder is usually staged: calm the symptoms first, then rebuild the strength and capacity of the area, then return to your full activities. The phases below show how that can progress.
Phase 1Painful, Irritable Shoulder (Often the First Few Months)
Settle pain and protect sleep while keeping whatever movement you currently have. The shoulder is very easily irritated in this phase, and forceful stretching tends to backfire. The 2013 clinical guideline for frozen shoulder (Kelley and colleagues) recommends gentle movement guided by pain, alongside physical treatments for pain relief (modalities) and education, rather than loading at the end of the range in this irritable phase.
Example exercises
- Pendulum (Codman) swings: letting the arm hang and swing in small circles, 1 to 2 minutes, 3 to 4 times daily, using gravity rather than force
- Gentle table slides, sliding the supported arm forward and across the body within a pain-free range
- Turning the arm outward with help from a stick pushed by the other hand (passive external rotation), stopping clearly before the point where it hurts
- Shoulder blade setting (gently drawing the shoulder blade back and down) and neck movement drills, to reduce overuse of the neck and upper shoulder muscles (upper trapezius) from guarding
- Practising sleep positions: lying on the other side, hugging a pillow with the sore arm, or on your back with a rolled towel behind the shoulder blade
Possible progression milestones
Night pain reducing to a level that allows most nights of sleep, pain at rest dropping to around 3 out of 10 or less, and movement in mid-range no longer provoking sharp pain.
Phase 2Stiffness Is the Main Problem (Timing Varies Widely)
Now that pain is calmer, the tight joint capsule is the main barrier. The shoulder now tolerates, and often needs, firmer . The 2013 clinical guideline for frozen shoulder (Kelley and colleagues) suggests joint mobilization and stretching matched to how irritable the shoulder is, so at this stage stretches can build up over time and be held into the zone of discomfort at the end of the range, rather than backing off at the first resistance.
Example exercises
- Hands-on joint mobilization of the shoulder joint in clinic (firmer, grade III to IV glides of the ball backward and downward), followed straight away by stretching you do at home
- Sleeper stretch (lying on the sore side and using the other hand to ease the forearm down toward the bed) for turning the arm inward, holding 30 to 60 seconds, 3 to 5 repetitions, several times daily
- Doorway or corner stretch for raising the arm forward and out to the side, going a little deeper week to week
- Stretch turning the arm outward with the arm raised 90 degrees out to the side, using a stick or a wall, held at the end of the range
- Forward bend at a table to help raise the arm overhead, letting your body weight produce the stretch
Possible progression milestones
Measurable gains of roughly 10 to 15 degrees in turning the arm outward or raising it forward over 4 to 6 weeks, being able to reach behind your back to the middle of the lower back, and the shoulder settling within 30 to 60 minutes of stretching rather than staying aggravated into the night.
Phase 3Movement Returning (Loading for Daily Tasks)
Once movement is returning, the shoulder needs strength and confidence to meet everyday demands. Months of guarding often leave the muscles substantially weaker (deconditioning). General evidence on loading tendons and shoulders supports moving from static holds (isometrics) to strengthening through movement as range returns to normal, matched to what your shoulder is tolerating that week.
Example exercises
- Turning the arm outward and inward against a resistance band, elbow at your side, building from static holds to slow repetitions through movement
- Rows, and Y, T and W arm lifts lying face down, to restore control of the shoulder blade by the muscles at the back of the shoulder
- Wall push-up progressions working toward standard push-ups, loading the shoulder with the hands fixed against a surface (closed-chain)
- Overhead press with light dumbbells once you can raise the arm fully overhead yourself, progressed by adding weight rather than repetitions
- Carrying, reaching and lifting drills that mirror the activities you are trying to return to
Possible progression milestones
Strength within roughly 10 to 15% of the other side when turning the arm outward and lifting it out to the side, pain-free overhead reach for daily tasks, and sleeping and dressing back to normal without working around the shoulder.
What you can do now
- Use the traffic-light rule when stretching. Stay in the amber zone of bearable stretch and avoid the red zone of sharp or lingering pain. In the early, painful phase, forcing the stretch at the end of the range tends to flare symptoms, disturb sleep and stall progress.If a stretch leaves pain that lingers or disturbs your sleep, you have gone into the red zone: ease off next time. Once the shoulder is mainly stiff rather than painful, it tolerates, and often needs, firmer stretches held longer, so match the intensity to the phase you are in.
- Move it little and often. Gentle movement 3 to 4 times a day can help keep and improve movement. Pendulum swings, letting the arm hang and swing in small circles for 1 to 2 minutes, and supported table slides within a pain-free range use gravity and support rather than force.
- Support the arm at night. Sleep on the other side with pillows supporting the sore arm forward, or on your back with the arm supported. Night pain often eases as the painful phase settles, though this can take months.Avoid forcing the arm into painful positions. If night pain comes with fever, weight loss or feeling unwell, check the warning signs on this page and follow them.
- Try heat before you stretch. Heat for 10 to 15 minutes before your exercises can help the tissues stretch more easily and ease protective muscle tension.Skip heat during a sudden, inflamed flare-up.
- Keep using the arm within comfort. Using the arm for everyday tasks within comfort helps stop it stiffening completely. Dressing aids and small changes to tasks help you avoid straining your neck, back or other shoulder by working around the stiff one.
What I use in clinic
- Hands-On Mobility Work. May help range of movement when combined with exercise.
- Stretching and Exercise. Stretching within comfort can help range in the stiff and recovering phases.
- Steroid (corticosteroid) injection. Can speed up early improvement in pain and movement when combined with physiotherapy, with little difference later on.
Recovery
How long it takes
Many people improve over months to years, but recovery can be incomplete and does not always follow three neat phases. Plateaus and flare-ups are normal. Physiotherapy can help you manage pain and keep function while it changes.
It usually improves over time, but recovery may be incomplete. In one long-term follow-up averaging over four years, 41% still had some symptoms, mostly mild (Hand and colleagues, 2008). Many people get back near-normal use of the shoulder, though it does not always recover completely.
What changes the timeline
- Diabetes and thyroid conditions are linked with a longer recovery
- How long you have had symptoms before treatment affects the outcome
- High mental demands, for example at work, and little support from others predict poorer outcomes
- Calming pain early in the freezing phase can make the stiff phase easier to work through
- Regular home exercise matters
- The phase the shoulder is in affects how it responds to treatment
How I track it. I track how far the shoulder moves in every direction, your pain, and the everyday tasks you can do
Similar conditions
Conditions that can feel similar
- Rotator Cuff Tear or Tendinopathy
- The shoulder typically still moves fully when someone else moves it, weakness stands out more than stiffness, and pain is felt in the outer upper arm when the muscles work against resistance. Frozen shoulder limits turning the arm outward early on, even when the arm is moved for you, which a rotator cuff problem usually does not.
- Subacromial Bursitis / Impingement Syndrome
- Pain through the middle range of lifting the arm (a painful arc, 60 to 120 degrees), while the shoulder still moves fully when moved for you. Pain when the arm is raised or turned in set positions (Neer and Hawkins tests), and relief after an injection under the point of the shoulder (subacromial). Frozen shoulder is stiff in every direction even when moved for you, especially turning the arm outward with the elbow at the side.
- Glenohumeral Osteoarthritis
- A similar loss of movement, including turning the arm outward, but usually in older people, with grinding or crackling (crepitus), a narrowed joint and bone spurs (osteophytes) on X-ray, and a slower course over many years, whereas frozen shoulder often improves over months to years.
- Calcific Tendinitis
- Often starts with sudden, severe pain that is out of proportion to what the examination finds. A calcium deposit shows on X-ray or ultrasound. Movement is limited more by pain and protective tension than by the firm stop of a tight capsule.
- Cervical Radiculopathy (C5-C6)
- Pain spreads from the neck into the arm along the path of one nerve (a dermatomal pattern). Tilting the head and pressing down on it brings on the arm pain (Spurling test), and the shoulder usually moves fully when moved for you. Nerve signs such as changed reflexes or weakness in particular muscles point away from a problem in the joint capsule.
- AC Joint Pathology
- Pain at the top of the shoulder over the AC joint, which is tender to press. Reaching the arm across the body brings it on (cross-body adduction test), and the main shoulder joint still moves fully when moved for you. Frozen shoulder pain is typically deep and hard to pin down, with stiffness in every direction.
Commonly confused with
Side-by-side comparisons for patterns that often get mistaken for frozen shoulder.
Questions
What patients ask me most
How long does frozen shoulder last?
Longer than most people want to hear. The classic teaching is 1 to 3 years through freezing, frozen, and thawing phases, but long-term data pushes that timeline out. Wong and colleagues (Physiotherapy 2017) systematically reviewed the natural history and found that without treatment, range of movement improved somewhat but not completely over one to four years, that most improvement came early rather than late, and that the tidy idea of phases ending in full recovery is not well supported. Hand and colleagues (JSES 2008) followed patients on average 4.4 years and found 41% reported some ongoing symptoms, though most were mild. Physiotherapy matched to your phase can help you manage pain and keep function along the way, but I am careful not to promise a quick fix.
Will my shoulder ever move normally again?
Most people regain enough range for daily life, but returning to exactly the motion you had before is not certain. Hand and colleagues (JSES 2008) followed patients for an average of more than four years and found 59% had normal or near-normal shoulders while 41% reported some ongoing symptoms, most of which were mild. My functional targets are pain-free sleep, full overhead reach for daily tasks, and the ability to dress and groom without working around the shoulder. Getting the last 10 degrees of rotation back can take many months of consistent work.
Do cortisone injections help frozen shoulder?
The evidence supports them for short-term pain relief, particularly in the painful freezing phase. Cochrane reviews and multiple randomised trials show that a steroid injection into the joint (intra-articular corticosteroid) reduces pain and improves function more quickly than physiotherapy alone in the first 6 to 12 weeks. After that window, differences between groups narrow and long-term outcomes look similar. The best results I see are when an injection calms the pain enough for someone to actually tolerate the mobility work. Benefits beyond 6 months are less certain, and the decision is about timing and access, not a permanent fix.
Why does my shoulder hurt so much at night?
Night pain is one of the most recognisable features of frozen shoulder, especially in the early, painful phase. Rolling onto the sore side or holding the arm still in one position can aggravate it, but it can persist whatever position you are in, and the exact reasons are not fully understood. I usually suggest sleeping on the other side with pillows supporting the sore arm forward, or on your back with the arm supported. Night pain often eases as the painful phase settles, though this can take months. If night pain comes with fever, weight loss or feeling unwell, see your family doctor.
Do I need surgery for frozen shoulder?
For most people, no. The UK FROST trial (Rangan et al., Lancet 2020) compared early structured physiotherapy, manipulation under anaesthesia, and arthroscopic capsular release in over 500 patients. At 12 months, none of the three was clinically superior on shoulder pain and function, and capsular release carried the highest complication rate. Physiotherapy is a reasonable first-line option, and I reserve surgical referral conversations for people who have genuinely plateaued after 6 to 9 months of well-delivered non-surgical care and still cannot meet their daily needs. Surgery carries its own risks and rehabilitation burden.
Can I prevent frozen shoulder coming back?
Recurrence in the same shoulder is uncommon, which is reassuring. The other shoulder becomes involved in roughly 5 to 34% of cases over several years in observational follow-up, with higher risk if you have diabetes or thyroid disease. There is no proven prevention protocol. The practical steps are keeping both shoulders moving through full range regularly, managing conditions such as diabetes or thyroid disease, and addressing any shoulder pain early rather than guarding it for weeks.
Should I push through the pain when stretching?
Not in the freezing phase. When the capsule is actively inflamed, forcing the stretch at the end of the range tends to flare symptoms, disturb sleep, and stall progress. I use a simple traffic-light rule: stay in the amber zone of bearable stretch, avoid the red zone of sharp or lingering pain. Once you move into the stiff phase, the tissue tolerates, and often needs, firmer stretches held longer at the end of the range to regain movement. Matching intensity to the phase you are in matters more than how hard you push on any given day.
Does frozen shoulder affect people with diabetes differently?
Yes, and it is worth knowing. People with diabetes are significantly more likely to develop frozen shoulder, the condition often affects both shoulders, and recovery is generally slower. Zreik and colleagues' 2016 meta-analysis estimated prevalence near 13% in people with diabetes compared to the 2 to 5% typically cited in the general population, with diabetic patients roughly five times more likely to develop the condition. I flag this at assessment because it shifts expectations on timeline, and keeping blood glucose well-controlled is sensible general care even if it will not on its own fix the shoulder.
The science
The Science of Frozen Shoulder
Frozen shoulder () involves thickening and tightening of the shoulder capsule. The normally loose capsule becomes inflamed then fibrotic, severely restricting movement. The condition typically progresses through freezing, frozen, and thawing phases.
The exact trigger is often unknown but can follow injury, surgery, or periods of immobilization. Physiotherapy for frozen shoulder focuses on restoring range of motion through graded and progressive loading, adapted to the stage of the condition. The intensity of treatment is matched to whether the capsule is in its painful, stiff, or recovering phase.
Contributing factors
The cause of frozen shoulder is not fully understood. The capsule around the joint becomes inflamed and then thickens and tightens, and this happens whether or not the shoulder is used. Guarding a painful shoulder does not cause it, but keeping the arm moving within comfort helps you hold on to the function you have.
When your shoulder becomes stiff, you'll unconsciously start using your neck, upper back, and other shoulder to perform daily tasks. Many people come in with secondary neck pain and upper back tension from months of working around a stiff shoulder, and that part usually settles with treatment.
Diabetes, thyroid conditions, and a recent period with the arm in a sling or after surgery are the best-known risk factors.
Research
What the studies show
Steroid injection, supervised physiotherapy, or both, for frozen shoulder
In a placebo-controlled trial, Carette and colleagues randomly assigned 93 people with frozen shoulder to groups that included a steroid injection into the joint, supervised physiotherapy, or both. The injection combined with physiotherapy gave the fastest early improvement in pain and range of movement, and the injection contributed most to the short-term gains.
Supports combining injection with physiotherapy for faster early relief rather than either alone.
Carette S, Moffet H, Tardif J, et al. Intraarticular corticosteroids, supervised physiotherapy, or a combination of the two in the treatment of adhesive capsulitis of the shoulder: a placebo-controlled trial. Arthritis Rheum. 2003;48(3):829-838. PMID: 12632439.
Related Conditions
Conditions I commonly see alongside, or confused with, this one.
Getting back to it
Physiotherapy for frozen shoulder, built around the activity you want back.
