
Knee Osteoarthritis
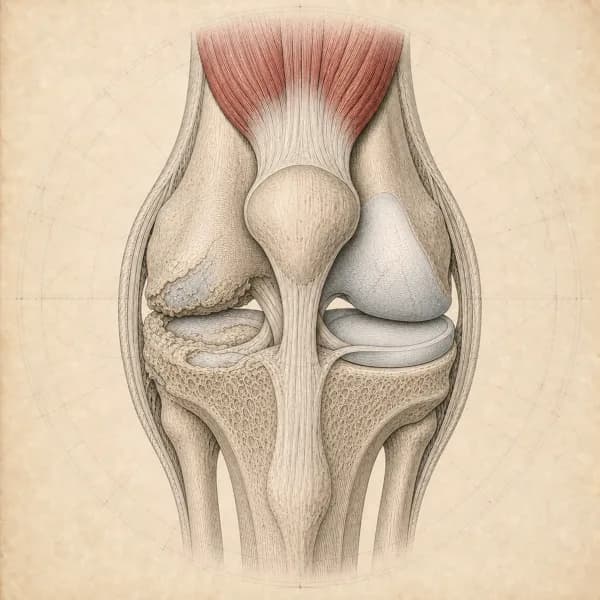
Knee osteoarthritis involves changes throughout the joint, including cartilage, underlying bone and the joint lining. It can cause activity-related pain, brief morning stiffness and swelling. Symptoms and X-ray findings do not always match, and diagnosis is often clinical. Care focuses on comfort, function and maintaining activities that matter to you.
Key points
- What usually helps
- Strengthening the front thigh muscle with low-impact exercise such as cycling, walking or water exercise.
- What you can do now
- Keep moving, and keep strengthening. Aim for 2 to 3 sessions a week.
- How long it takes
- Improvement is often seen within 6 to 12 weeks, and it needs long-term management.
- When to see a doctor first
- Some signs need emergency care. Check the list before you start treatment.
Symptoms
Does this sound like you?
- Knee pain when standing and walking on the leg
- Morning stiffness lasting less than 30 minutes
- A grinding or crackling feeling in the joint (crepitus)
- Swelling after activity
- Difficulty with stairs
Often alongside it
- Reduced walking distance
- Aching at night in later stages
- The knee feeling unstable or buckling
- Muscle weakness
- A change in the way you walk
It comes on gradually over years. At first, pain comes with activity and eases with rest. Everyday activities then become gradually more limited.
Before using this comparison, check when these symptoms need a doctor first.
When to see a doctor first
Go to emergency
Calf pain, swelling or warmth, or sudden shortness of breath, especially after surgery or a long period of reduced activity
Possible blood clot. Calf symptoms need same-day medical assessment; shortness of breath or chest pain means go to emergency now
Get seen today
A hot, red, very swollen knee, especially with a fever or feeling unwell
Possible joint infection or gout. Same-day medical assessment, even without a fever, or go to emergency if you feel unwell
You cannot put weight on the leg after a fall, or pain is severe at night and at rest
Possible fracture or other bone problem. See your family doctor promptly, the same day after a fall
Check with your doctor
The knee locks and will not straighten
Possible loose fragment or meniscus tear blocking movement. See your family doctor or a sports medicine physician within a few days
Treatment
How it is treated
Main approach. Building up strength in the front thigh muscle (quadriceps), together with low-impact exercise for fitness (aerobic exercise) such as cycling, walking or water exercise, can meaningfully reduce pain and improve function for many people, and for some it helps put off surgery.
Alongside it. For people carrying extra weight, losing some weight reduces the load on the knee and can improve pain and function alongside exercise.
Managing it over time. Keeping up a strengthening and activity routine after the first block of rehab helps keep pain and function from slipping back, and for some people helps put off the need for surgery.
A typical rehabilitation progression
Three phases, from settling symptoms to returning to full activity.
Recovery from knee osteoarthritis is usually staged: calm the symptoms first, then rebuild the strength and capacity of the area, then return to your full activities. The phases below show how that can progress.
Phase 1Calm Symptoms and Restart the Thigh Muscles (Weeks 1 to 4)
Bring day-to-day pain down to a level that allows regular training, and start rebuilding strength in the front thigh (quadriceps) and hip. This follows the 2019 international guideline (OARSI) and the 2022 NICE guideline (NG226), which place exercise plus education at the core of first treatment. The amount matters: Juhl and colleagues (2014) found that programs with enough total exercise tend to do better than sparse ones, so early sessions focus on building a home routine you can repeat.
Example exercises
- Sit-to-stand from a firm chair, 3 sets of 8 to 10, progressing to a lower seat height
- Short-arc quadriceps extension (straightening the knee from a slight bend, with a roll under the knee) through a pain-free range close to straight, 3 sets of 10 to 12
- Wall sit held still with the knees only slightly bent, 3 sets of 20 to 45 seconds
- Side-lying (lifting the top leg while lying on your side), 3 sets of 12 to 15 per side
- Stationary cycling at light resistance, 10 to 20 minutes, used as both warm-up and joint mobility work
Possible progression milestones
Pain during daily walking and stairs at or below 3 out of 10, no flare lasting beyond 24 hours after sessions, and tolerance for 2 to 3 exercise sessions per week for two consecutive weeks.
Phase 2Progressive Loading and Functional Strength (Weeks 4 to 12)
Build real lower-body strength under load. A 2015 Cochrane review (Fransen and colleagues) found that structured exercise on land brings gains in pain and function large enough to matter to patients, and the size of the benefit usually tracks with how consistently people keep to the program. This phase adds exercises with the foot on the ground (closed-chain), single-leg strength and fitness work. Some discomfort during exercise is acceptable provided it settles within 24 hours.
Example exercises
- Goblet squat (holding a weight at your chest) to a box, 3 to 4 sets of 8 to 10, adjusting box height to how deep you can comfortably go
- Leg press, 3 sets of 8 to 12, progressively loaded
- Step-ups and step-downs, 3 sets of 8 to 10 per side, keeping the knee under control
- Split squats or supported reverse lunges, 3 sets of 8 per side
- Fitness work (aerobic exercise), 20 to 40 minutes of cycling, brisk walking or water exercise, 3 to 5 times per week
Possible progression milestones
Walking at least 30 minutes without a flare-up, standing up fully from a chair without using your arms, measurable strength gains on leg press or step-down tests, and stable or improving scores on a standard knee questionnaire.
Phase 3Return to Activity and Long-Term Maintenance (Months 3 onward)
Bring back the activities you care about, whether that is recreational running, tennis, hiking or dancing with grandchildren, and build a maintenance plan you can keep up. Symptoms commonly come back if exercise stops, so this phase is about building what the knee can handle and keeping it up, rather than a fixed end point.
Example exercises
- Progressive walking or walk-run program, using gradual weekly increases in duration rather than pace
- Heavier squats and deadlifts on both legs, matched to your goals and what the knee tolerates
- Single-leg balance and hops, built up where your sport needs them
- Hiking or stair intervals, if those are the activities you are working toward
- A twice-weekly maintenance routine of 4 to 6 key strength exercises kept indefinitely
Possible progression milestones
Back to the recreational activity you want, with pain 2 out of 10 or less and no flare-up over the next 24 hours, knee questionnaire scores at or above your personal target, and a maintenance plan you can realistically keep up on your own.
What you can do now
- Keep moving, and keep strengthening. People who stay active with a structured strength program generally keep their function better than those who stop moving to protect the joint. Squats and lower-body work with weights can be part of it, with depth and load matched to how the knee is now.Some discomfort during exercise is acceptable if it settles within 24 hours.
- Aim for 2 to 3 sessions a week. The amount of exercise needs to be enough to help. That usually means at least 2 to 3 sessions a week for 8 to 12 weeks before judging how well it is going.
- Pick exercise you will keep doing. In trials, water exercise, cycling, strength training, tai chi and yoga all improved knee osteoarthritis symptoms, so the best choice is often the one you will stick with. Water exercise can suit you if exercise on your feet is too painful to start with.
- Manage your weight if you carry extra. Losing weight reduces the load on the knee and inflammation, and even a 5% reduction in body weight can meaningfully reduce symptoms. Weight management and strengthening together tend to do better than either one alone.Changes you can keep up matter most.
- Judge by pain and function, not noise. Painless clicking or grinding (crepitus) is common, and the sound alone does not show whether the arthritis is getting worse. How pain and function change over weeks and months matters more.A hot, red, very swollen knee needs a same-day medical assessment, even without a fever, or go to emergency if you feel unwell.
What I use in clinic
- Therapeutic Exercise. A structured exercise program reduces pain and improves function, by about as much as anti-inflammatory medicines (NSAIDs).
- Manual Therapy. Hands-on treatment gives short-term pain relief when combined with exercise.
Recovery
How long it takes
Improvement is often seen within 6 to 12 weeks of an exercise program, and the condition needs long-term management.
Changes on X-ray tend to progress slowly, but symptoms vary a lot from person to person and often improve with exercise. Exercise is not shown to slow the joint changes themselves; its benefit is on pain and function.
What changes the timeline
- How severe the arthritis is
- Body weight
- How active you are
- Keeping up with exercise
How I track it. I track pain levels, walking distance, stair climbing ability, and quality of life
Similar conditions
Conditions that can feel similar
- Meniscal Tear (Degenerative)
- Tenderness along the joint line, true catching or brief locking, and a twist with weight on the leg. The difference matters less than people assume in older patients, because wear-related meniscus tears and early osteoarthritis frequently occur together and respond to similar rehabilitation.
- Patellofemoral Pain
- Widespread pain around or behind the kneecap that is worse with long sitting and going down stairs than with standing and walking on level ground. People are typically younger, though the two can occur together in older adults whose joint changes are mainly at the front of the knee.
- Pes Anserine Bursitis or Tendinopathy
- Tenderness in one spot on the inner shin bone, 5 to 7 cm below the joint line, rather than at the joint line itself. Bending the knee and turning the shin inward against resistance brings on the pain. It can be mistaken for osteoarthritis on the inner side of the knee (the medial compartment), and the two often occur together.
- Referred Pain from the Hip
- Pain at the front or inner side of the knee without any tenderness in the knee itself, with turning the hip inward limited or painful, and a hip test that brings on pain (FADIR). Hip osteoarthritis showing up as knee pain is a classic miss, so knee pain in any older adult warrants a quick hip check.
- Inflammatory Arthropathy (Rheumatoid or Gout)
- Morning stiffness lasting well over an hour, several joints involved, warmth and redness over the joint, whole-body symptoms like fatigue or fever, or sudden attacks of severe pain and swelling caused by crystals in the joint. It needs medical tests and input from a rheumatologist, not just physiotherapy.
- Subchondral Bone Stress Injury or Insufficiency Fracture
- Pain that suddenly gets worse over days to weeks, night pain out of proportion to activity, and a clear limp from pain. More common in older adults with lower bone density. Swelling inside the bone on MRI (bone marrow oedema) guides management, and the limits on rehab are very different from standard osteoarthritis.
Questions
What patients ask me most
Is knee osteoarthritis the end of running or active sport?
No. A diagnosis of knee osteoarthritis does not automatically mean giving up running, hiking or recreational sport. Studies that follow people over time have repeatedly failed to show that recreational running speeds up knee osteoarthritis, and several suggest recreational runners may have lower rates of painful osteoarthritis than people who are inactive. The practical issues are how much load you take on, strength, and how you build up. Patients who stay active with a structured strength program generally keep their function better than those who stop moving to 'protect' the joint.
How much does exercise actually help knee osteoarthritis?
A lot more than most people expect. The Fransen Cochrane 2015 review of land-based exercise pooled 44 trials and found a roughly 12 point reduction in pain on a 100 point scale, with benefits lasting several months after formal treatment ended. Juhl and colleagues (2014) found similar effects across aerobic, strengthening and performance exercise. Both OARSI 2019 and NICE NG226 (2022) list structured exercise and education as core treatments to start with. The dose needs to be enough, which usually means at least 2 to 3 sessions a week for 8 to 12 weeks before reassessing.
Do I need an MRI if I have knee osteoarthritis?
Usually not. NICE NG226 recommends diagnosing osteoarthritis from symptoms and examination, without imaging, in anyone 45 or older with activity-related joint pain and morning stiffness under 30 minutes. A plain x-ray can be useful if there is uncertainty, but routine MRI tends to turn up chance findings, like meniscus or cartilage changes, that are common in people over 50 with no symptoms and rarely change the plan.
When should I consider a knee replacement?
Knee replacement becomes a reasonable discussion when pain persists despite a genuine trial of exercise therapy, weight management and medication, and when function has declined enough to meaningfully limit daily life. The Skou et al. NEJM 2015 trial compared surgery plus non-surgical care against non-surgical care alone in patients judged eligible for replacement. The surgical group had better 12 month scores, but also substantially more serious complications, and most patients in the non-surgical group did not go on to have surgery during follow-up. That is worth knowing: surgery works, but a well-delivered non-surgical program is not the throwaway option.
Does weight loss really change knee symptoms?
Yes, and the effect is mechanical as well as metabolic. OARSI 2019 lists weight management alongside exercise as a core treatment. Even modest reductions in body weight meaningfully reduce the force pressing the joint surfaces together during walking and stairs, which is why weight management and strengthening together tend to do better than either one alone. This is framed as a structural change to the plan, not as a moral verdict on the patient.
Should I get a cortisone injection?
Sometimes, for short windows. OARSI 2019 lists a corticosteroid injection into the joint as conditionally recommended for short-term symptom relief of roughly 1 to 6 weeks. I see it most usefully as a way to open a window for rehab, reducing pain enough to get strength work started, rather than as a long-term strategy. Repeated injections over years are not supported by current guidance.
Does the grinding noise from my knee mean it is getting worse?
Painless clicking or grinding (crepitus) is common, and many adults without symptoms have noisy knees. The sound alone does not show whether arthritis is worsening or whether treatment is needed; pain, function, and how they change over weeks and months matter more than the noise itself. A quiet knee that hurts more is a bigger concern than a noisy knee that is functioning well.
Can I still lift weights and squat with knee osteoarthritis?
Strengthening is one of the most important things you can do, and it includes squatting and lower-body work with weights where tolerated. Depth, load and speed get tailored to how the knee is right now, but the goal is quite the opposite of avoidance. Front thigh (quadriceps) and hip strength are linked to function and symptom levels in knee osteoarthritis, and stronger muscles absorb load the joint would otherwise take.
The science
The Science of Knee Osteoarthritis
involves breakdown of cartilage, changes in underlying bone, and inflammation of the joint lining. It's not just wear and tear but an active process involving the whole joint. Quadriceps weakness is linked with a higher risk of developing knee osteoarthritis and with more pain and difficulty once it is present. Previous injuries such as tears or tears significantly increase the risk of developing knee osteoarthritis, as these injuries often lead to altered and joint . Like other conditions, knee osteoarthritis may coexist with pain syndrome, particularly when both involve similar movement pattern dysfunctions.
Contributing factors
Knee isn't simply "wear and tear". Age, previous injury, body weight, genetics and how the knee is loaded all play a part. Quadriceps weakness is linked with more pain and difficulty, and it can become a cycle: pain can make you less active, which can lead to more weakness. Pain can arise from several tissues in and around the joint, and how much it hurts does not map directly to how much cartilage has been lost. Strength training helps many people, without that proving weakness caused the arthritis.
Movement may play a part. Some people's knees drift inward () or outward during weight-bearing activities, which changes how load is shared within the joint, and stiffness at the hip or ankle can also change how you walk and how load passes through the knee.
Previous knee injuries, such as an injury or a tear, raise the risk of osteoarthritis later on. For people carrying extra body weight, it adds load to the knee during daily activities like stair climbing and getting up from chairs, and losing some weight can ease symptoms alongside exercise.
Research
What the studies show
Comparing types of exercise for knee osteoarthritis: a review of 39 trials
Across 39 trials (2,646 people), all five exercise types studied (aquatic exercise, cycling, resistance training, tai chi and yoga) improved knee osteoarthritis symptoms. Aquatic exercise ranked best for pain relief and yoga for stiffness, function and quality of life, followed by resistance training, cycling and tai chi.
Several types of exercise can help knee osteoarthritis, which leaves room to pick one that suits the person.
Mo L, Jiang B, Mei T, Zhou D. Exercise Therapy for Knee Osteoarthritis: A Systematic Review and Network Meta-analysis. Orthop J Sports Med. 2023;11(5):23259671231172773. PMID: 37346776.
International guideline (OARSI) on treating knee osteoarthritis without surgery
The core treatments were structured exercise programs on land and education about arthritis. Water-based exercise was also recommended (Level 1B or Level 2 in the guideline's grading).
Shows that an international guideline treats exercise and education as core treatments for knee osteoarthritis.
Bannuru RR, Osani MC, Vaysbrot EE, et al. OARSI guidelines for the non-surgical management of knee, hip, and polyarticular osteoarthritis. Osteoarthritis Cartilage. 2019;27(11):1578-1589. PMID: 31278997.
- Exercise Type. A review comparing results across 39 trials found that water exercise, cycling, strength (resistance) training, tai chi and yoga all improved knee osteoarthritis symptoms, so the best choice is often the one a person will keep doing
- Water-Based Exercise. A review that pooled trials found physical therapy in water reduced pain compared with control groups, and it can suit people who struggle with exercise that puts weight through the legs
- Hands-On Treatment Timing. Hands-on treatment (manual therapy) may help pain more after about 4 weeks of treatment, and its long-term benefit is uncertain, which supports using it alongside exercise rather than on its own
- Guideline Agreement. The 2019 international osteoarthritis guideline (OARSI) lists structured exercise and education as core treatments for knee osteoarthritis
Guides on knee pain
Longer explanations of symptoms and scan-report wording.
- Pain Right Below the KneecapA single tender spot below the kneecap that flares with jumping, stairs, or deep squats. Most commonly patellar tendinopathy in active adults, and growth-plate conditions in young athletes.
- Suprapatellar Effusion (Fluid on the Knee)Extra fluid inside the knee joint, seen in the pouch above the kneecap. What the size words on a report mean, the usual causes by how quickly the swelling came on, and when to see a doctor first.
- Joint Space Narrowing in the KneeThe gap between the bones looks thinner than expected on an X-ray. What medial, tricompartmental and the severity words mean, how it relates to pain, and what the guidelines recommend.
Related Conditions
Conditions I commonly see alongside, or confused with, this one.
Hip Osteoarthritis
Hip stiffness alters gait and can accelerate knee joint degeneration
ACL Injuries
ACL injuries significantly increase risk of early knee osteoarthritis
Ankle Sprains
Chronic ankle instability alters knee mechanics and can contribute to OA
Plantar Fasciitis & Heel Spurs
Foot/ankle dysfunction affects knee loading patterns
Patella Fractures
A fracture into the joint surface is one cause of osteoarthritis developing later
Getting back to it
Physiotherapy for knee osteoarthritis, built around the activity you want back.
