
Posterior Tibial Tendon Dysfunction
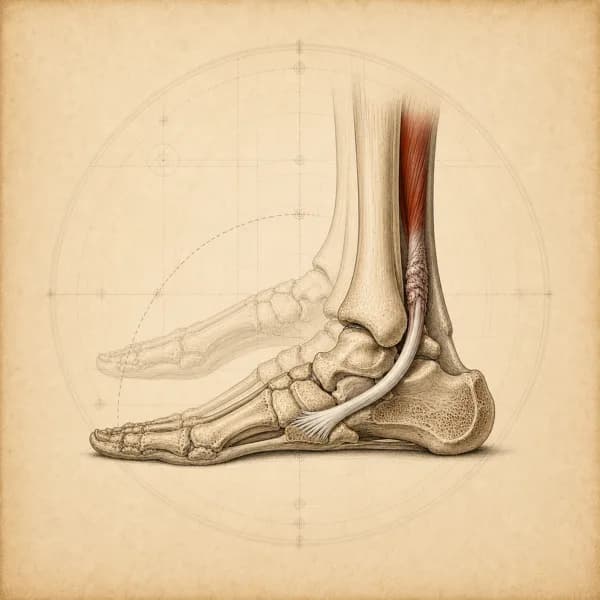
Posterior tibial tendon dysfunction affects a tendon that helps support the arch. It can cause inner ankle pain and difficulty rising onto the toes. Some people also develop changes in foot shape, called progressive collapsing foot deformity, which can involve other ligaments and joints as well as this tendon.
Key points
- What usually helps
- In the early stages, a shoe insert or brace with strengthening of the tibialis posterior muscle.
- What you can do now
- Wear your orthotic or brace consistently. Start strengthening sitting down.
- How long it takes
- Early stages often improve over a few months; later stages can take longer.
- When to see a doctor first
- Some signs need emergency care. Check the list before you start treatment.
Symptoms
Does this sound like you?
- Pain on the inner side of the ankle and in the arch, especially when standing and walking
- The arch on the inner side of the foot gradually flattening
- Not being able to rise onto your toes on one leg on the affected side (single heel rise)
- Pain and swelling along the tendon that runs behind the inner ankle bone into the arch (the posterior tibial tendon)
- Gradually managing shorter walks and finding stairs harder
- Sensation of foot giving way or instability during walking
Often alongside it
- Pinching pain on the outside of the ankle as the heel tips further outward (hindfoot valgus)
- Calf muscle weakness and early fatigue during activity
- Pain in the knee, hip or other foot from moving differently to protect the sore foot
- Visible foot deformity when standing or walking
- Shoes that no longer fit well and wear out faster
- Balance problems and increased fall risk
Pain typically creeps in gradually along the inner ankle and arch, and gets worse with long periods of standing or walking on uneven ground. Morning stiffness eases once you start moving, then worsens again as the day goes on. Over months to years the arch visibly flattens. Losing the ability to rise onto your toes on one leg at the same time is a key sign for the diagnosis.
Before using this comparison, check when these symptoms need a doctor first.
When to see a doctor first
Go to emergency
A foot that suddenly becomes unusually cold, pale, or blue, or a toe with a new colour change that persists, especially with pain, numbness, or weakness
Go to emergency now; the blood supply may be blocked
Unable to bear weight after an injury, or a visibly deformed ankle or foot
Go to emergency now to rule out a fracture or dislocation
Get seen today
A hot, red, swollen foot, especially if you have diabetes or reduced feeling in your feet
Same-day medical assessment to rule out Charcot foot or infection, and keep weight off the foot until you are seen
Numbness or weakness in the foot that is spreading or getting worse
Same-day medical assessment to check the nerves
Check with your doctor
A flat foot that has become stiff and no longer straightens when you take weight off it
See your family doctor for an orthopaedic referral; this suggests a later stage that may need a surgical opinion
Severe pain on the outer ankle with difficulty walking, or the ankle starting to tilt inward
See your family doctor promptly for an orthopaedic referral
A familiar, brief colour change in the toes triggered by cold, already diagnosed as Raynaud's
Follow your existing care plan. New, persistent or unusually severe changes need medical assessment, and the emergency signs above still apply. Do not assume an unexplained change is Raynaud's
Treatment
How it is treated
Main approach. In the early stages, a shoe insert (orthosis) or brace combined with strengthening of the muscle attached to this tendon (tibialis posterior) can relieve symptoms and restore function for many people (Alvarez et al., 2006), and may slow progression.
Alongside it. Rehabilitation of the rest of the leg and pacing your activity help limit flares while the load on the tendon is built up step by step.
Managing it over time. Acting early on inner ankle pain, along with weight management and diabetes control, may lower the chance of the deformity progressing.
A typical rehabilitation progression
Three phases, from settling symptoms to returning to full activity.
Recovery from posterior tibial tendon dysfunction is usually staged: calm the symptoms first, then rebuild the strength and capacity of the area, then return to your full activities. The phases below show how that can progress.
Phase 1Taking Load Off and Waking Up the Tendon (Weeks 1 to 6)
Protect the tendon from the arch-flattening load () that has been overwhelming it, and start getting the tibialis posterior muscle to switch on again. The programs used by Alvarez and by Kulig both start with wearing an orthotic or brace consistently as the base of the program, then add exercise with many repetitions and light load. Day to day, the aim is a clearly less painful foot at the end of a day on your feet, even if the heel rise is not back yet.
Example exercises
- Wearing a supportive foot orthosis (functional foot orthosis) or a hinged ankle-foot brace (articulated brace) consistently whenever you are on your feet, as in the Alvarez program
- Seated heel rises with the knee straight and a towel under the toes, 3 sets of 15 to 20, slow and controlled
- Seated, turning the foot inward against a long band (resisted ), 3 sets of 15 to 20, with a clean, slow movement rather than speed
- Short-foot holds: gently doming the arch without curling the toes, 3 sets of 10 with 10-second holds
- Reduce prolonged standing blocks where possible, and rotate supportive footwear rather than spending the day in flat, flexible shoes
Possible progression milestones
Possible milestones, adapted to the person rather than treated as fixed cut-offs: inner ankle pain at the end of the day down meaningfully from where it started, over several days, at least a partial heel rise on the affected side, and the orthosis or brace comfortable for the whole waking day.
Phase 2Building Load and Single-Leg Control (Weeks 6 to 16)
Build how much load the tendon can take with gradually heavier, slower work on both the lowering () and lifting () phases. In a 2009 trial by Kulig and colleagues, everyone improved with orthoses and stretching, the groups that added resistance exercise improved more, and the group that focused on the lowering phase improved most. A heel rise with the knee bent puts more of the work on the lower calf (soleus) and the tibialis posterior, and suits this condition better than a straight-knee heel rise early on.
Example exercises
- Heel rises on both feet with the heels turned slightly inward at the top, 3 sets of 12 to 15, 3 seconds up and 3 seconds down
- Progress to single-leg heel rise on the affected side, starting at partial range and building toward full height and 15 reps per side
- Turning the foot inward against a band or resistance by hand, with a slow, controlled lowering phase (eccentric inversion), starting from a turned-out position, 3 sets of 10
- Single-leg balance with a forward reach, on firm ground first, progressing to a foam pad, 3 sets of 8 per direction
- Orthotic still worn for all standing and walking, and daily stretches for both calf muscles (gastrocnemius and soleus) to keep the ankle bending up toward the shin
Possible progression milestones
Possible milestones, adapted to the person rather than treated as fixed cut-offs: a solid set of clean single-leg heel rises per side, inner ankle pain low during loading, and several weeks without next-day flares after heavier sessions.
Phase 3Return to Walking Volume and Activity (Months 4 to 6+)
Rebuild tolerance for long walks, work that keeps you on your feet and, where appropriate, low-impact running or hiking. This is not a return-to-sprint phase for most patients. The goal is a comfortable, capable foot in daily life, with the shape of the foot monitored over time. Ongoing orthotic use and twice-weekly maintenance loading can help maintain the gains.
Example exercises
- Walking volume progression on softer surfaces, in small weekly steps
- Step-ups and step-downs with controlled foot posture, 3 sets of 8 to 10
- Loaded carries and farmer's walks with the orthotic in place, to rebuild standing and carrying tolerance
- Graded low-impact cardio: cycling, swimming, or elliptical work maintained throughout, with gradual reintroduction of hiking if tolerated
- Twice-weekly single-leg heel rise work at heavier loads as maintenance, indefinitely
Possible progression milestones
Back to your usual daily standing and walking without inner ankle pain at the end of the day, scores on an ankle questionnaire (FAAM) trending toward pre-symptom levels, and no further visible flattening of the arch when rechecked in clinic over 8 weeks.
What you can do now
- Wear your orthotic or brace consistently. In the early months, wear it whenever you are on your feet. It takes over some of the work the tendon cannot do yet, which may give the tendon a chance to adapt and may help limit further flattening of the arch.Have it fitted properly, and replace it when it is badly worn. Cut down wear step by step as strength returns, not all at once.
- Start strengthening sitting down. Start with seated heel rises, knee straight and a towel under the toes, and seated inward turns of the foot against a long band, each 3 sets of 15 to 20, done slowly. Short-foot holds (gently doming the arch without curling the toes, 10 seconds, 3 sets of 10) add work for the arch.Move on to standing heel rises as your single-leg heel rise improves, and do not force through significant pain.
- Break up long spells of standing. Cut back on long periods of standing, uneven ground and high-impact activity for a while to limit flares while the tendon settles. A clearly less painful foot at the end of a day on your feet is a sign the balance is right.
- Choose firm, supportive shoes. Shoes with good arch support, a firm back around the heel (heel counter) and a curved rocker sole reduce stress on the tendon in daily activities. Rotate supportive pairs rather than spending the day in flat, flexible shoes.Avoid high heels, and replace shoes promptly when they wear out. If the shape of your foot has changed a lot, custom changes to your footwear may be worth considering.
- Choose low-impact exercise for fitness. Body weight adds load to the tendon, so losing weight may reduce it. If you are working on your weight or fitness, cycling, swimming or an elliptical keep you active without high impact.
What I use in clinic
- Orthotics with arch support. In a study that followed people with stage I to II posterior tibial tendon dysfunction (Alvarez et al., 2006), custom foot orthoses with a built-up inner arch (medial arch posting), particularly when combined with a structured strengthening program, produced good outcomes for most patients. University of California Biomechanics Laboratory (UCBL) orthoses give firmer control of the heel and rearfoot (hindfoot).
- Posterior tibial strengthening, built up gradually. Structured strengthening that works both the lowering (eccentric) and lifting (concentric) phases improves single-leg heel rise ability and reduces pain over 3 to 6 months.
- Ankle brace for later stages (ankle-foot orthosis, or AFO). A brace that crosses the ankle, such as the Arizona AFO, can give meaningful pain relief and make walking and daily activities easier in stage II to III posterior tibial tendon dysfunction. It controls the ankle in a way an in-shoe arch support alone cannot.
- Hands-on treatment and joint mobilization. Gentle movement of the midfoot and rearfoot joints (joint mobilization), combined with soft tissue work, gives short-term pain relief and easier movement when added to exercise.
Recovery
How long it takes
Early-stage posterior tibial tendon dysfunction often improves over a few months of non-surgical care. Later-stage cases where the foot is still flexible can take longer, and some people stabilise rather than fully recover. With a stiff or advanced deformity, exercise is unlikely to change the foot's shape, although a brace may still improve comfort and walking, and a foot and ankle surgeon can discuss surgical and non-surgical options.
This condition tends to progress without treatment, although the pace varies and some early cases stay stable for years. In a study that followed people with stage I and II disease treated with an orthosis and exercise, 83 percent had successful outcomes and 11 percent needed surgery (Alvarez et al., 2006). A stiff (fixed), late-stage deformity deserves a foot and ankle surgeon's opinion, and a substantial brace remains an option for people who do not want or cannot have surgery.
What changes the timeline
- Stage: a flexible foot has more room to respond to non-surgical care; with a stiff deformity, exercise is unlikely to change the shape, though a brace may still help comfort and walking
- Body weight, which adds load to the tendon
- Diabetes or inflammatory arthritis, which can affect tendon health
- Consistency with the orthosis or brace, if that is part of the plan
- How long symptoms have been present before care starts
How I track it. I monitor your pain during specific activities on your feet, measure changes in arch height and foot alignment, check how well you can rise onto your toes on one leg, and track how far you can walk and how you manage stairs
Similar conditions
Conditions that can feel similar
- Tarsal Coalition
- A stiff flat foot since childhood, very little side-to-side heel movement, and a bony bridge between foot bones seen on a scan
- Charcot Arthropathy
- A history of diabetes, a sudden onset with a warm, swollen foot, and collapse through the middle of the foot (midfoot)
- Posterior Tibial Tendinitis
- A recent flare with signs of inflammation such as swelling, no flattening of the arch, and a normal single-leg heel rise
- Deltoid Ligament Sprain
- A history of ankle injury, and tenderness on the inner side of the ankle without the arch flattening
- Accessory Navicular Syndrome
- A prominent bump on the inner midfoot (the navicular bone), pain over a small extra bone there (an accessory ossicle), and a normal arch
Questions
What patients ask me most
My arch is dropping and the inside of my ankle hurts. Is this actually treatable without surgery?
In early stages, often yes. Alvarez and colleagues reported in Foot and Ankle International (2006) that a structured non-operative protocol combining a short hinged (articulated) brace or orthosis with high-repetition strengthening of the tibialis posterior muscle gave successful outcomes in 83 percent of 47 patients with stage I or II disease, and 11 percent needed surgery. Kulig and colleagues in Physical Therapy (2009) found that adding resistance exercise, focused on either the lowering (eccentric) or lifting (concentric) phase, to orthoses and stretching further reduced pain and improved function, although a later trial by Houck and colleagues (2015) found a home exercise program added little to orthosis wear in stage II. The common thread is early recognition and consistent orthotic use paired with a real strengthening program, rather than rest alone.
Why cannot I rise up on my toes on the painful side anymore?
A single-leg heel rise depends on the posterior tibial tendon tipping the heel inward and locking the midfoot, so the calf can push through a stable lever. When the tendon has failed, the heel cannot tip inward, the midfoot stays loose, and the calf pushes into a collapsing arch rather than a rigid foot. The heel rise falters or does not happen at all. It is a useful sign in the clinic, and the gradual return of that movement is one of the first things I track as rehab progresses.
Do I really have to wear the orthotic all the time?
In the early months, often yes. The orthotic takes over some of the work the tendon currently cannot do, which may give the tendon a chance to adapt and may help limit further collapse, although that is a goal rather than a guarantee. Alvarez's protocol used a short hinged (articulated) brace for the early phase before transitioning to a functional foot orthosis. Long term, many patients taper down to wearing the orthosis only during higher-demand standing and walking, but this is a stepwise reduction as strength returns, not an immediate choice.
What is the difference between posterior tibial tendon dysfunction and plantar fasciitis?
Plantar fasciitis sits in the heel under the sole and is worst on the first steps in the morning. Posterior tibial tendon dysfunction sits along the inside of the ankle and arch, can ache throughout a long day of standing rather than just in the morning, and is often paired with a visibly dropping arch and difficulty rising onto the toes. The two can coexist, which is why a careful examination helps.
How did this even start? I do not remember an injury.
That is typical. Johnson and Strom's original 1989 description and most subsequent work describe a gradual onset with no clear injury, often in women over 40, sometimes triggered by a modest increase in standing or walking, a weight gain, or a stretch of unsupportive footwear. Diabetes, inflammatory arthritis, and prior ankle trauma raise the risk. The tendon does not fail in a single moment. It fails slowly under cumulative load until the arch begins to give and the pain pattern becomes recognisable.
Will the arch come back once I start strengthening?
Not usually. Once the spring ligament (which supports the arch from underneath) and surrounding tissues have stretched, the shape of the foot rarely reverses fully even with successful rehab. In earlier stages, I aim to improve function, get the pain down, and monitor the shape of the foot; slowing further collapse is a goal, not a guarantee. With a stiff or advanced deformity, exercise is unlikely to change the foot's shape, but a brace may still improve comfort and walking. Many people return to long walks, hiking, and standing-intensive work with a flatter foot that is strong, controlled, and comfortable, which is a very different situation from one that is flattening further every year.
When is surgery actually on the table?
Surgery enters the conversation when the deformity becomes rigid, when the heel can no longer be eased back into position by hand (it no longer corrects passively), or when conservative care has been done well for at least six months without meaningful improvement. With Stage III and IV disease, where the joint just below the ankle (the subtalar joint) or the ankle joint itself is involved, exercise is unlikely to change the foot's shape. A substantial brace may still improve comfort and walking, including for people who do not want or cannot have surgery, and a foot and ankle surgeon can discuss both routes. Before that point, the priority is giving a well-structured orthotic and loading program a genuine trial; in the Alvarez case series of stage I and II disease, 11 percent went on to surgery.
The science
The Science of Posterior Tibial Tendon Dysfunction
Posterior tibial tendon dysfunction (PTTD), now commonly termed Progressive Collapsing Foot Deformity (PCFD), represents a complex, progressive condition involving failure of the posterior tibial tendon and associated ligamentous structures. The posterior tibial tendon serves as the primary dynamic stabilizer of the medial longitudinal arch and controls motion during the stance phase of walking.
The condition begins with inflammation and changes within the tendon substance (tendinosis), often triggered by repetitive microtrauma or acute overload. As the tendon's structural integrity compromises, its strength diminishes, particularly during the loading response and terminal stance phases of gait. This leads to progressive loss of the tendon's ability to resist forces and maintain arch integrity.
Secondary to tendon failure, supporting ligamentous structures become progressively incompetent. The spring ligament complex (calcaneonavicular ligament) stretches and eventually fails, followed by attenuation of the superficial deltoid ligament, long and short plantar ligaments, and . This cascade creates a characteristic pattern of deformity: hindfoot , , midfoot collapse, and eventual ankle valgus in late-stage cases.
The condition progresses through distinct stages: Stage I involves tendinosis without deformity, Stage II presents flexible deformity that corrects with non-weight bearing, Stage III shows fixed deformity with subtalar joint , and Stage IV involves ankle valgus and deltoid ligament failure. Understanding this progression is crucial as treatment options and prognosis differ significantly between stages.
Contributing factors
The posterior tibial tendon functions as part of an integrated system that maintains the medial longitudinal arch and controls foot mechanics during weight-bearing activities. During normal gait, the tendon contracts eccentrically from heel strike through midstance to resist excessive , then concentrically during heel rise to the and lock the midfoot for efficient push-off.
When the posterior tibial tendon fails, the foot loses its primary mechanism for arch support and supination. The talus adducts and plantarflexes, the navicular drops medially, and the moves into . This creates a "too many toes" sign when viewed from behind, as the laterally deviated becomes visible.
The biomechanical changes extend beyond the foot. Hindfoot valgus causes compensatory external rotation of the tibia, affecting knee mechanics and potentially contributing to dysfunction. The inability to achieve a rigid lever arm during push-off reduces propulsive efficiency and increases energy expenditure during walking.
Weight-bearing forces that normally distribute across the entire foot concentrate on the medial structures, accelerating ligamentous failure. The loss of the due to midfoot collapse further compromises the foot's ability to become a rigid lever, perpetuating the cycle of dysfunction.
Risk factors that predispose to biomechanical failure include obesity (increasing load), diabetes (affecting tendon quality), previous ankle trauma disrupting normal mechanics, inflammatory causing tendon , and congenital flatfoot creating chronic overload of compensatory structures.
Research
What the studies show
Deep calf muscle strength and foot movement in stage II posterior tibial tendon dysfunction
In 30 people with stage II posterior tibial tendon dysfunction and 15 matched people without it, those with the condition, with or without weakness of the deep calf muscles (the deep posterior compartment), showed more rolling inward of the rearfoot (hindfoot eversion) during walking than the comparison group. Those whose strength was 20 percent or more below the other leg showed more rolling inward than those without that weakness. Strength was linked to how much the foot flattened, but flatfoot also occurred without weakness.
Strengthening is a reasonable part of non-surgical care when weakness is present, but the authors note it may only partly correct the foot position, so bracing and, for some people, surgery may also be needed.
Neville C, Flemister AS, Houck JR. Deep posterior compartment strength and foot kinematics in subjects with stage II posterior tibial tendon dysfunction. Foot Ankle Int. 2010;31(4):320-328. PMID: 20371019.
Orthoses plus resistance exercise for posterior tibial tendon dysfunction: a randomised trial
In 36 adults with early-stage posterior tibial tendon dysfunction, everyone improved over 12 weeks of orthoses and stretching. The groups that also did resistance exercise built up over time, focused on either the lowering (eccentric) or the lifting (concentric) phase, had a further drop in pain and better function, and the lowering-phase group improved most.
Supports adding resistance exercise for the tibialis posterior muscle, built up over time, to orthotic care rather than relying on orthoses and stretching alone.
Kulig K, Reischl SF, Pomrantz AB, et al. Nonsurgical management of posterior tibial tendon dysfunction with orthoses and resistive exercise: a randomized controlled trial. Phys Ther. 2009;89(1):26-37. PMID: 19022863.
Related Conditions
Conditions I commonly see alongside, or confused with, this one.
Plantar Fasciitis & Heel Spurs
Both involve medial arch support; PTTD can lead to plantar fascia overload
Ankle Sprains
Chronic ankle instability can contribute to posterior tibial tendon overuse
Achilles Tendinopathy / Tendinitis
Achilles tightness can increase stress on posterior tibial tendon
Knee Osteoarthritis
Flatfoot deformity from PTTD alters knee mechanics and loading patterns
Tarsal Tunnel Syndrome
Both involve structures around medial ankle; swelling from PTTD can compress nerves
Shin Splints
Getting back to it
Physiotherapy for posterior tibial tendon dysfunction, built around the activity you want back.
