
Hip Labral Tears
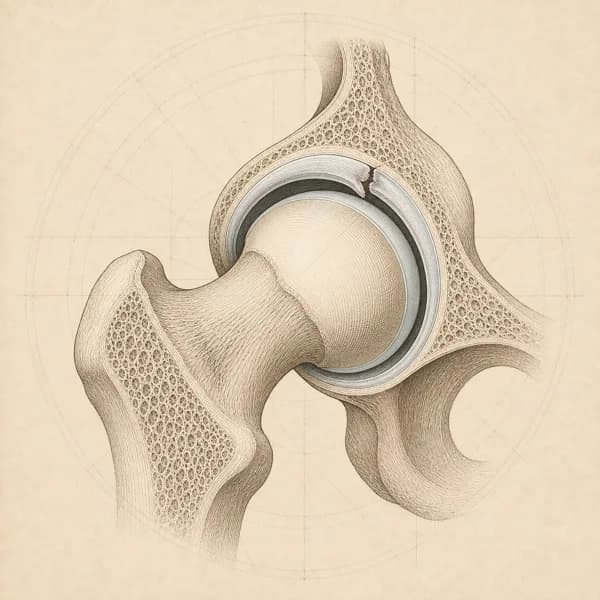
The labrum is a ring of cartilage around the rim of the hip socket that helps seal and steady the joint. A tear can cause sharp, catching groin pain with twisting or deep bending, sometimes with clicking, and often occurs alongside hip impingement. Labral tears also show up on scans of many people with no hip pain.
Key points
- What usually helps
- Hip strengthening and retraining how you move. Many people manage without surgery.
- What you can do now
- Avoid deep bending with turning for now. Choose firmer, higher seats.
- How long it takes
- A fair trial of non-surgical care is usually 3 to 4 months.
- When to see a doctor first
- Some signs need medical care the same day. Check the list before you start treatment.
Symptoms
Does this sound like you?
- Sharp, catching pain in the groin with certain movements
- Clicking, catching, or a brief locking feeling with hip movement
- Deep aching pain in the groin or buttock region
- Pain when pivoting, twisting or turning on the leg
- Difficulty with movements that bend the hip deeply (squatting, sitting in low chairs)
- Patients often trace a 'C' shape from the groin to the side of the hip to show where it hurts (the C-sign)
Often alongside it
- Pain with long periods of sitting or driving
- Stiffness after sitting still or resting
- Pain with sports that involve sudden changes of direction or pivoting
- Feeling of instability or hip 'giving way'
- Night pain in some cases
It often affects young, active adults, who may have had symptoms of hip impingement before. Pain typically comes with activity and may be linked to specific movements or positions. The C-sign is typical: people trace the pain from the groin around to the side of the hip.
Before using this comparison, check when these symptoms need a doctor first.
When to see a doctor first
Get seen today
Groin pain in a runner that builds with each run or hurts when hopping on that leg
Possible stress fracture of the hip (femoral neck). Stop running and all impact exercise, keep weight off the leg, and get medical assessment today. If you cannot put weight on the leg or the pain is severe, go to emergency. An early X-ray can look normal
A hot, swollen or very painful hip, a fever or feeling unwell, or you cannot put weight on the leg
Possible infection or fracture. Get medical assessment today, or go to emergency if you feel unwell or cannot bear weight. Infection is possible even without a fever
Check with your doctor
The hip locks and you cannot move it through its range
Possible tear that has moved out of place (displaced tear) or a loose fragment in the joint (loose body). See your family doctor or a sports medicine physician within days for an orthopaedic referral
Severe, constant pain that does not change with position
See your family doctor promptly to rule out other causes
Treatment
How it is treated
Main approach. Non-surgical care built on hip strengthening and retraining how you move can help many people with labral tears manage without surgery.
Alongside it. Limiting deep hip bending and turning, and working around any underlying hip impingement (FAI) bone shape, reduces stress on the labrum so symptoms can settle while you stay active.
Managing it over time. Keeping up hip strength, and managing how often you bend the hip deeply while turning it, can help keep symptoms settled once they have improved.
A typical rehabilitation progression
Three phases, from settling symptoms to returning to full activity.
Recovery from hip labral tears is usually staged: calm the symptoms first, then rebuild the strength and capacity of the area, then return to your full activities. The phases below show how that can progress.
Phase 1Settle the Hip and Protect the Labrum (Weeks 1 to 6)
The early goal is to calm the hip (reduce irritability) and rebuild confidence in the joint. Deep hip bending combined with turning is avoided for now. I start loading away from the pinch position, in ranges the tolerates, and spend time on switching on the buttock muscles (glutes), because weakness in the muscle on the side of the hip () can raise the load on the front of the hip joint and may increase stress on the front and top of the labrum when you stand on one leg.
Example exercises
- Lying on your back, pressing the legs outward against a band and holding ( ), 4 sets of 30 seconds, to work the deep buttock muscles without bending and turning the hip
- Lying face down, lifting the leg behind you with the buttock muscles (prone hip extension), 3 sets of 12, keeping the pelvis still
- Bridging (lying on your back, lifting the hips) with the pelvis level, 3 sets of 10, progressing to small single-leg bridges when both sides match
- Standing up from a slightly raised seat through a short range (short-arc sit-to-stand), so the hip does not bend into the painful pinch
- A review of posture and daily movement: low couches, low car seats and long cross-legged sitting are left out for now
Possible progression milestones
Sharp groin catching rare in everyday life, walking for 30 minutes without a flare, and standing on the affected leg for 30 seconds comfortably.
Phase 2Load and Control Through Range (Weeks 7 to 16)
This is real strength work, not just switching muscles on. Yazbek and colleagues (2011) and other reports on groups of patients treated without surgery (case series) describe programs built on control of the hip, lower back and pelvis, buttock (glute) strengthening, and a gradual return to everyday demands, rather than only stretching or rest. I lean into that approach here while bringing turning back in gradually.
Example exercises
- Squat to a box holding a weight at the chest (goblet box squat), to a depth that stays short of the painful pinch, 3 sets of 8 with a moderate kettlebell
- Romanian deadlift (lowering a weight by hinging at the hips) with a light to moderate load, 3 sets of 8, to load the muscles at the back of the hips and thighs
- Split squat with the back foot raised on a bench (rear-foot-elevated split squat), keeping the upper body upright, 3 sets of 8 per side
- Step-ups onto a low step with good control of the pelvis, raising the height only while the movement stays controlled and comfortable, 3 sets of 8 per side
- Standing with a band, moving the leg out to the side and back (hip abduction and extension), 3 sets of 12 per side, to keep working the muscles that make those movements
Possible progression milestones
Goblet squats and Romanian deadlifts loaded more heavily over time without groin pain, step-ups with the pelvis staying level, and a 60 minute walk without stopping that does not cause a flare the next day.
Phase 3Return to Sport and Rotation (Months 4 to 6+)
The final block rebuilds the hip's tolerance for turning and impact for your own goals, whether that is hockey, soccer, dance or weekend hiking. It builds up step by step, because labral tears in athletes who repeatedly bend and turn the hip can flare again if the amount of training jumps too quickly.
Example exercises
- Controlled turning exercises, such as cable rows with a twist and a half-kneeling press with a turn, 3 sets of 8 per side
- Single-leg Romanian deadlift (standing on one leg and hinging forward at the hip) with balance and control, 3 sets of 6 per side
- Jumping exercises built up step by step (): low hops, bounds and box jumps as tolerated
- Drills for your sport, with the amount controlled: skating stride, kicking, change of direction
- Return to training plan with a clear week-on-week progression rather than all-or-nothing comebacks
Possible progression milestones
Back to the activities that matter to you, single-leg strength tests about equal on both sides, confidence pivoting and changing direction (cutting), and a maintenance program you will keep doing.
What you can do now
- Avoid deep bending with turning for now. Bending the hip deeply while turning it often aggravates a labral tear. Taking these movements out for a while lets the hip settle while you stay active.Avoid forcing the hip to the far ends of its movement.
- Choose firmer, higher seats. Low seats put your knees higher than your hips, which bends the hip past about 90 degrees, a position many irritable hips tolerate poorly. A firmer, higher seat or a small wedge cushion often makes a large difference while you rebuild tolerance.Leave out low couches, low car seats and long cross-legged sitting for now.
- Squat to a box, hinge to lift. You usually do not need to stop squatting or deadlifting, but the range matters. Squat to a comfortable box depth and lift by hinging at the hips, as in a Romanian deadlift, which builds the hip while respecting the labrum.Leave out deep squats with turning, which often flare it early on.
- Watch for pain, not clicking. Clicking on its own, without pain, does not usually mean ongoing damage. What matters more is whether the hip feels trustworthy when you load it.If clicking comes with sharp groin pain or the hip gives way, get it reassessed. If the hip locks and you cannot move it through its range, see your family doctor or a sports medicine physician within days, as the warning signs on this page say.
What I use in clinic
- Hip Strengthening Program. Targeted hip strengthening, particularly of the buttock muscles (glutes), improves symptoms and function. Strong, coordinated hip muscles keep the joint stable as it moves. The program progresses gradually, with the focus on quality over quantity.
- Movement Pattern Training. Changing ways of moving that strain the hip reduces stress on the labrum.
Recovery
How long it takes
A fair trial of non-surgical care is usually 3 to 4 months. Many people respond well to physiotherapy.
Many labral tears can be managed without surgery. Surgery is considered if non-surgical care fails after a fair trial.
What changes the timeline
- The size of the tear and where it is
- Whether hip impingement (FAI) is behind it
- What your activities ask of the hip
- Age and how well your tissues heal
- Keeping up with rehabilitation
How I track it. I track how much the pain gets in the way of the tasks that matter to you, how well you move when I test those tasks in clinic, and how confident you feel in daily activities
Similar conditions
Conditions that can feel similar
- Femoroacetabular Impingement Syndrome
- It often occurs together with labral tears. Imaging shows extra bone at the hip joint (a cam or pincer shape), which is frequently the underlying mechanical cause. FAI without a labral injury can still cause pain at the front of the groin on the FADIR test (bending, crossing and turning the hip inward).
- Hip Osteoarthritis
- Older people, morning stiffness, and the ability to turn the hip inward (internal rotation) lost more evenly. Catching is less noticeable. Imaging shows the joint space narrowing rather than a labral finding on its own.
- Iliopsoas Tendinopathy or Internal Snapping Hip
- Pain at the front of the hip with a tendon snap you can feel or hear as the hip straightens from a bent position, pain when lifting the leg against resistance, and typically less groin catching when pivoting.
- Adductor-Related Groin Pain
- Pain on the inner groin brought on by squeezing the knees together against resistance (the adductor squeeze test), and tenderness at the pubic bone where the inner thigh muscles attach. More common in field sports.
- Hip Stress Fracture (Femoral Neck)
- Groin pain that gets worse with load rather than with particular turning positions, marked pain with single-leg hopping, and often a recent sharp jump in training or not eating enough for the energy used (relative energy deficiency).
- Lumbar Radiculopathy or L1 to L3 Referral
- Pain changes with lower back movement rather than with turning the hip, the hip moves fully when the examiner moves it, and the FADIR test does not bring on the usual groin pain.
Questions
What patients ask me most
Does a labral tear on my MRI mean I need surgery?
Not necessarily. Labral tears that cause no symptoms are common. Register et al. (AJSM 2012) found labral tears on MRI in around 69 percent of pain-free adults across a broad age range. What imaging shows needs to match your symptoms and examination. Many patients with both imaging findings and symptoms do well with loading-based physiotherapy. Surgery becomes a more reasonable conversation when progressive strength work has genuinely been tried and the hip still cannot meet life or sport demands.
Can a torn labrum actually heal?
The labrum has a limited blood supply, so a true tear does not typically heal back together. That is not the same as pain continuing. What usually changes with rehabilitation is how easily the tear is irritated, and how well the tough sleeve around the joint (the capsule) and the muscles control the joint. Many patients get back to what they need to do and are largely pain-free, without the tear itself changing shape on imaging.
What does the C-sign mean?
The C-sign is when a patient cups their hand around the side of the hip, from the front of the groin to the bony point on the side of the hip (the greater trochanter), to describe where the pain sits. It is a pattern I see frequently with pain from inside the hip joint, including labral tears, but it is not only seen with labral injuries. It is a useful starting point, not a diagnosis.
Should I avoid squats and deadlifts?
Usually no, but the range matters. Deep squatting with turning often flares it early on. I typically keep patients squatting to a comfortable box depth and lifting by hinging at the hips, such as Romanian deadlifts, which respect the labrum while still building the hip. Rebuilding strength is part of the treatment, not the enemy.
Does clicking mean my labrum is tearing further?
Clicking by itself, without pain, does not usually indicate ongoing damage. Clicking that comes with sharp groin pain, giving way, or the hip truly locking is a different story and warrants reassessment. I pay more attention to whether the hip feels trustworthy under load than to the noise it makes.
How long should I try physiotherapy before considering surgery?
A genuine trial of 3 to 4 months of progressive strengthening, mobility work and load management is fair for most patients. Hip-related pain research, including Kemp et al.'s BJSM 2020 systematic review and meta-analysis of physiotherapist-led treatments, supports physiotherapy as a reasonable first approach for hip-related pain, including when the labrum is involved. If symptoms are still significantly limiting life after that, a surgical consult is reasonable, and I am happy to coordinate.
Why does sitting on a low couch hurt my hip so much?
Low seats put your knees higher than your hips, which bends the hip further, past about 90 degrees. Many irritable hips tolerate that deep bend poorly, particularly with a cam-shaped hip. A firmer, higher seat, or a small wedge cushion, often makes a large difference while you rebuild tolerance.
The science
The Science of Hip Labral Tears
Hip labral tears involve damage to the , a ring of that runs along the rim of the hip socket (acetabulum), acting like a suction cup to enhance stability. The labrum provides a suction seal that maintains negative pressure within the joint, contributing significantly to hip stability. When torn, this can result in mechanical symptoms and altered joint .
Labral tears often occur alongside femoroacetabular (FAI). X-rays can assess bone shape and joint-space changes, but they do not show the labrum; MRI may be considered when information about the labrum or other soft tissues would change treatment. When imaging would change the plan, I flag it to your family doctor or specialist and refer you. A FAI morphology can make contact with the socket and labrum during deep hip flexion, leading to a pinching sensation and potential stress on the labrum over time.
However, not all labral tears are symptomatic: many people have labral tears without pain. The development of symptoms depends on the tear's location, size, the individual's activity demands, and importantly, the presence of underlying bony abnormalities like FAI. Treating an isolated labral tear without addressing underlying FAI morphology may lead to poor outcomes, as the mechanical cause of the tear remains unaddressed.
Contributing factors
The serves multiple mechanical functions that become compromised when torn. Research demonstrates that the labrum contributes approximately 1-2mm of depth to the hip socket and generates a suction seal that maintains negative intra-articular pressure. This seal effect contributes substantially to the hip's resistance to distraction forces, with cadaveric work showing that considerably less force is needed to distract the hip once the seal is vented or the labrum is torn, explaining why labral tears can create sensations of or "giving way." The labrum also helps spread contact forces more evenly across the cartilage of the socket, and cadaver studies show higher cartilage stress when the labrum is removed.
The mechanical pathway to labral tears typically involves repetitive forces rather than a single traumatic event. In the presence of cam-type FAI morphology, the anterosuperior labrum (the portion at the front and top of the socket) experiences abnormal shear forces during hip flexion combined with internal rotation. In individuals with , deep squatting movements concentrate elevated contact stress at the anterosuperior rim, increasing the load borne by the labrum. These repetitive micro-traumas accumulate over time, eventually leading to labral and tearing.
Movement patterns significantly influence labral stress. Activities involving combined hip flexion beyond 90 degrees with rotation, such as hockey skating, martial arts kicks, or yoga poses, create the highest labral loading. Athletes in sports requiring extreme hip range of motion show high rates of labral tears on imaging, and labral findings are also common in asymptomatic people from the general population. The specific location of tears correlates strongly with movement demands: anterosuperior tears associate with repetitive flexion-internal rotation activities, while posterior tears more commonly occur with extension-external rotation movements.
The relationship between hip joint loading and labral tears extends beyond acute impingement events. During normal walking, the hip experiences forces of approximately 238% body weight, transmitted through the femoral head into the acetabulum and labrum. Any factor that alters this load distribution, including muscle weakness, altered gait mechanics, or structural abnormalities, can contribute to progressive labral damage. weakness can raise anterior hip joint loading during single-leg stance, which may increase stress on the anterior-superior labrum, highlighting the importance of muscle function in protecting labral tissue.
Rotational sports create particularly challenging mechanical demands. The combination of axial loading (body weight compression) with torsional forces (rotational movements) generates complex stress patterns in the labrum. Soccer kicking mechanics create high peak hip internal rotation velocities, with corresponding impulsive loads transmitted through the anterosuperior labrum. Similarly, ice hockey players performing crossover skating maneuvers generate repeated impingement forces that can stress the labrum many times in a game.
The natural shock-absorbing capacity of the labrum diminishes with aging and repetitive loading. Labral tissue tends to show progressive degenerative changes with age even in asymptomatic individuals, with decreased organization and reduced cellularity. This age-related degeneration makes the labrum more susceptible to mechanical failure under loads it would have tolerated when younger, explaining why labral tears often become symptomatic in the third and fourth decades of life even without obvious injury events.
Research
What the studies show
Physiotherapist-led treatment for hip-related pain: a review of the research (Kemp et al.)
This review, which pooled the results of earlier studies, found that physiotherapist-led treatment built around strengthening the hip, lower back and pelvis, and exercises that load everyday movements (functional loading), can improve pain and function in people with hip-related pain. This supports physiotherapy as a reasonable first approach for hip-related pain, including when the labrum is involved.
Supports non-surgical care as the first treatment.
Kemp JL, Mosler AB, Hart H, et al. (2020). Improving function in people with hip-related pain: a systematic review and meta-analysis of physiotherapist-led interventions for hip-related pain. Br J Sports Med. PMID: 32376673.
How often scans find hip changes in people without hip pain (Register et al.)
In this study of adults without hip pain (prospective and blinded), MRI scans showed labral tears in around 69 percent of hips with no symptoms. Labral tears are common in people without symptoms, so scan findings need to be matched with the symptoms and examination rather than read on their own.
Emphasizes matching scan findings to your symptoms and examination.
Register B, Pennock AT, Ho CP, et al. (2012). Prevalence of abnormal hip findings in asymptomatic participants: a prospective, blinded study. Am J Sports Med. PMID: 23104610.
Related Conditions
Conditions I commonly see alongside, or confused with, this one.
Getting back to it
Physiotherapy for hip labral tears, built around the activity you want back.
