
Lateral Hip Pain & Gluteal Tendinopathy
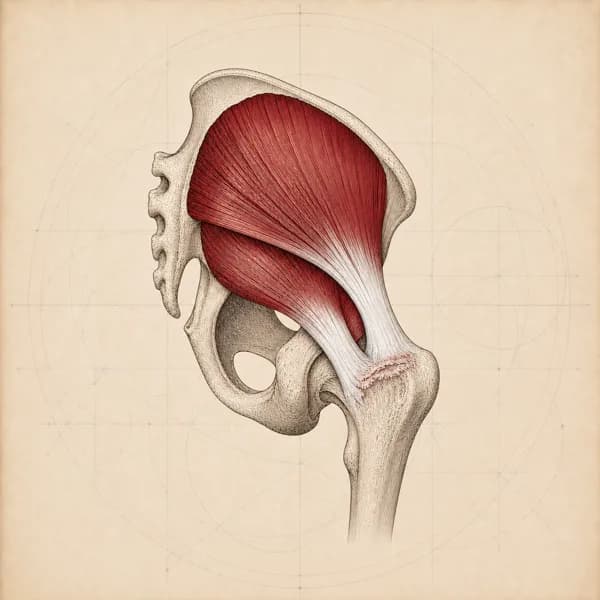
Greater trochanteric pain syndrome causes pain over the bony prominence on the outside of the hip. It often involves the gluteal tendons and sometimes nearby bursae, the small fluid-filled sacs. Lying on that side, climbing stairs or walking uphill may aggravate it. Assessment helps distinguish it from hip-joint or referred pain.
Key points
- What usually helps
- Education and exercise built up gradually. In the LEAP trial they did better overall than a cortisone injection.
- What you can do now
- Sleep on the other side, with pillows. Uncross your legs and stand evenly.
- How long it takes
- Pain often starts to ease within 4 to 6 weeks; rebuilding the tendon takes 3 to 6 months or longer.
- When to see a doctor first
- Some signs need medical care the same day. Check the list before you start treatment.
Symptoms
Does this sound like you?
- Tender, aching pain centred on the bony point on the side of the hip (the greater trochanter)
- Pain radiating down the outer thigh, sometimes as far as the knee
- Night pain, often the most troublesome symptom. Lying on the painful side presses on the area, and lying on the other side stretches it. Both can be very irritating
- Pain when you first get out of bed or up from a chair after being still ('start-up' pain)
- Pain with activities where you stand on one leg, and with walking (especially up hills or on uneven ground)
Often alongside it
- Pain with climbing stairs and standing on one leg
- Difficulty getting comfortable lying on either side
- The hip dropping on one side as you walk (Trendelenburg gait)
- Pain when crossing your legs or standing for a long time with your weight on one hip
- Simple actions like getting out of a car or standing up after sitting set the pain off
People with this condition typically point directly to the side of their hip, the bony part you can feel, known as the greater trochanter. The story is rarely about a specific injury. Instead, it's about a pain that has crept in and become a persistent, nagging ache. The most common and frustrating complaint I hear is night pain. 'I just can't get comfortable,' they'll say. 'I lie on the painful side, and it hurts. I lie on my good side, and it still hurts.' Simple actions like getting out of a car, climbing stairs, or standing up after sitting for a while set the pain off. It badly disrupts sleep and makes everyday movements a painful chore. It is common in women after menopause, but it affects all ages. It is often linked to a sudden jump in load the hip is not used to, such as a new running program or a 'boot camp' class with lots of single-leg work.
Before using this comparison, check when these symptoms need a doctor first.
When to see a doctor first
Get seen today
Sudden pain after a fall, or you cannot put weight on the leg
Possible hip fracture or tendon tear. Same-day medical assessment, or go to emergency
A hot, red or swollen outer hip, especially with a fever
Possible infected bursa. Same-day medical assessment, even without a fever, or go to emergency if you feel unwell
Check with your doctor
Severe, constant pain not relieved by position changes
Not typical of tendon pain. See your family doctor promptly to look for a stress fracture or other bone problem
Numbness, tingling or weakness spreading down the leg
See your family doctor before starting physiotherapy to check the lower back and nerves
Treatment
How it is treated
Main approach. In the LEAP trial, education plus exercise that builds up gradually gave better overall improvement than a cortisone (corticosteroid) injection at 8 weeks and at 1 year, with 77% reporting success at 8 weeks. Pain levels at 1 year were similar after the two treatments.
Alongside it. Avoiding positions that squeeze the tendon, combined with strengthening holds that do not move the joint (isometric exercises), calms the irritated tendon while building what it can handle for everyday activities.
Managing it over time. Avoiding sudden jumps in training, and sleeping in positions that stop the thigh dropping across the body (adduction), may help lower the chance of gluteal tendinopathy (irritation of the buttock tendons on the side of the hip).
A typical rehabilitation progression
Three phases, from settling symptoms to returning to full activity.
Recovery from lateral hip pain & gluteal tendinopathy is usually staged: calm the symptoms first, then rebuild the strength and capacity of the area, then return to your full activities. The phases below show how that can progress.
Phase 1Easing the Squeeze and Starting Strength Holds (Weeks 1 to 6)
Reduce the squeeze on the buttock tendons (gluteal tendons) by changing posture and sleep positions, and start holds that push the leg outward without moving it ( ) in positions that do not squeeze the tendon. This mirrors the early weeks of the education plus exercise program in the LEAP trial (Mellor and colleagues, BMJ 2018). The priority is calming the tendon by removing the ongoing squeeze, rather than chasing strength gains.
Example exercises
- Lying on your back with a band above the knees, pressing the knees outward and holding (isometric hip abduction), 5 sets of 30 to 45 seconds at moderate effort
- Side-lying holds for the muscles on the side of the hip (isometric abduction), with the top leg supported on pillows so it stays level, 5 sets of 20 to 30 seconds
- Standing side-on to a wall, pressing the leg outward into the wall and holding (isometric hip abduction), 5 sets of 30 seconds
- Sleep set-up: a pillow between the knees and a second between the ankles, so the top leg does not fall forward
- Posture habits: no crossing the legs, no standing with your weight shifted onto one hip, and standing with your feet under your hips
Possible progression milestones
Sleeping through the night more often than not for 2 weeks in a row, less start-up pain after sitting, and 30 to 45 second holds without a flare over the next 24 hours.
Phase 2Strengthening Through Movement, Step by Step (Weeks 6 to 16)
Rebuild the strength of the muscles on the side of the hip (abductors) through a controlled range, while still avoiding positions that squeeze the tendon. Exercises move from two legs to one, and from band resistance to weights, broadly following the exercise progression in the LEAP trial. How the hip responds over the following 24 hours guides each week's adjustments.
Example exercises
- Bridge on both legs (lying on your back, lifting the hips), progressing to a single-leg bridge, 3 sets of 8 to 12 reps
- Lying on your side, lifting the top leg (sidelying hip abduction) with the pelvis tilted slightly back to favour the muscle on the side of the hip (), 3 sets of 10 to 15 reps
- Standing, moving the leg out to the side against a cable or band (hip abduction), 3 sets of 10 reps per side, keeping the pelvis level
- Step-ups to a low step without letting the pelvis drop on the other side, 3 sets of 8 reps per side
- Standing up from a slightly raised seat (sit-to-stand), progressing to a standard chair and then to a lower seat
Possible progression milestones
Standing on one leg for 30 seconds to put on pants without pain, walking on level ground for 30 minutes without a flare, and climbing a flight of stairs one foot per step without the pelvis dropping or pain above 3 out of 10.
Phase 3Building Up for Daily Life and Return to Activity (Months 4 to 6+)
Rebuild what the hip can handle for hills, long walks, hiking, running and sports that rely on one leg at a time. Exercises add hip control under heavier load and controlled practice in the positions that used to set the pain off, once the tendon has clearly adapted.
Example exercises
- Split squats, and split squats with the back foot raised on a bench (rear-foot-elevated), 3 sets of 8 reps per side
- Offset single-leg bridge with pause at the top, 3 sets of 8 reps per side
- Stepping down from a moderate step while keeping the pelvis level, 3 sets of 8 reps per side
- Progressive hill walking program, starting with gentle gradients and building duration by no more than 10 percent per week
- Return to running or hiking with a schedule that builds up step by step, or to training such as group fitness classes with the load adjusted to what the hip can currently handle
Possible progression milestones
Sleeping through the night on either side, walking uphill without an ache on the outside of the hip, back to the activities you want (hiking, running, group fitness or work demands), and confidence in the hip's stability during single-leg tasks.
What you can do now
- Sleep on the other side, with pillows. Start on the side that does not hurt, with a firm pillow between your knees and another between your ankles, so the top leg stays level instead of dropping across your body and squeezing the tendon. Sleeping on your back also avoids the squeeze, and some people find a small pillow tucked behind them more comfortable than lying fully on the back.Avoid lying on the painful side for now, because it presses directly on the tendon.
- Uncross your legs and stand evenly. Crossing your legs and standing with your weight hanging on one hip both bring the thigh across the body, which squeezes the buttock tendons against the bony point of the hip. Stand with your weight even on both legs and your feet under your hips.
- Skip IT band stretches and foam rolling. Stretches that cross one leg behind the other and lean sideways pull the thigh across the body, and foam rolling over the outer hip presses on the same spot. Both squeeze the tendon and often keep the pain flared.
- Keep walking, in shorter, flatter outings. Complete rest is rarely helpful, and losing fitness makes the problem worse. Break up long walks, choose flatter routes for now, and avoid walking to the point of a flare.Hold off on hill repeats until the hip handles more, then bring hills and stairs back gradually rather than avoiding them.
- Start gentle holds against a wall. Holds that push the leg outward without moving it can start loading the tendon without squeezing it. Stand side-on to a wall and press the leg out into it for 30 seconds, 5 times.If the holds leave the hip sorer over the next 24 hours, ease the effort.
What I use in clinic
- Education and Load Management. In the LEAP trial, education plus exercise gave better overall improvement than an injection at 8 and 52 weeks; pain at 52 weeks was similar.
- Progressive Loading Exercise. Loading the tendon step by step helps it adapt and rebuild (remodel), but this needs time. It starts with holds that do not move the joint (isometric exercises) and progresses very gradually, and you stop if symptoms rise sharply.
- Manual Therapy. Hands-on soft tissue work for related muscle tension, avoiding pressure directly on the tendon.
Recovery
How long it takes
Pain often starts to ease within 4 to 6 weeks of managing the load on the tendon. Fully rebuilding what the tendon can handle takes 3 to 6 months or longer. Doing the exercises regularly matters more than doing them hard.
It often improves with load management and exercise, while rest alone rarely settles it. An injection may ease pain in the short term but does not rebuild the tendon.
What changes the timeline
- How long you had symptoms before treatment
- Sticking with the changes that ease the load on the tendon
- Being able to change the activities that aggravate it
- Strength and movement control at the start
- Hormones (women after menopause may take longer)
- Other hip or pelvic conditions
How I track it. I track how much the pain gets in the way of the tasks that matter to you, how well you move when I test those tasks in clinic, and how confident you feel in daily activities
Similar conditions
Conditions that can feel similar
- Hip Osteoarthritis
- Groin pain with activity is the main symptom, rather than tenderness in one spot on the outer hip. Morning stiffness is absent or usually lasts no more than 30 minutes, turning the hip inward (internal rotation) is reduced on examination, and it is often in people aged 45 or older. Sometimes the person cups the hip from groin to side to show where it hurts (the C-sign).
- Femoroacetabular Impingement
- Pain at the front of the groin when the hip bends deeply and turns, pain on a test that bends, crosses and turns the hip inward (FADIR), and catching with squatting or getting out of a low car seat. Typically in younger, active people.
- L5 or S1 Radiculopathy Referring to the Lateral Hip
- Back pain now or recently, pain that goes below the knee or into the foot, and pain brought on by nerve tension tests (slump or straight leg raise). There may be changed reflexes, or numbness in the strip of skin supplied by one nerve root (a dermatome).
- Meralgia Paresthetica
- Burning, tingling or numbness along the front and side of the thigh, rather than a deep ache at the bony point of the hip. Symptoms get worse with tight belts or long standing, and pressing directly on the bony point is not tender.
- External Snapping Hip (Coxa Saltans Externa)
- A snap you can hear or feel as the IT band flicks over the bony point of the hip when the hip bends and straightens. It is often more of a snapping problem than a pain at rest, and the snap can be reproduced on examination.
- Iliotibial Band Syndrome
- Pain on the outside of the knee rather than the hip, brought on by downhill running and repeated knee bending around 30 degrees, with no tenderness over the bony point of the hip itself.
- Deep Gluteal Syndrome Including Piriformis Involvement
- Deep buttock pain rather than tenderness in one spot on the outer hip, worse with long sitting, and sometimes pain down the back of the thigh along the path of the sciatic nerve. A seated piriformis stretch, or a test that bends, crosses and turns the hip inward (FAIR test), brings it on.
- Lumbar Facet Joint or Sacroiliac Joint Referral
- The pain changes when the lower back bends backward or twists, and there is tenderness over the small joints of the lower back (facet joints) or the sacroiliac joint. The outer hip is not tender, or not consistently, and a group of tests that stress the sacroiliac joint is often positive.
Commonly confused with
Side-by-side comparisons for patterns that often get mistaken for lateral hip pain & gluteal tendinopathy.
Questions
What patients ask me most
Why does my outer hip hurt at night?
Night pain is one of the most typical features of gluteal tendinopathy, and it is often linked to the tendon being squeezed against the bony point of the hip (the greater trochanter) for long periods. Lying on the painful side presses directly on the tendon. Lying on the other side with the top knee falling forward stretches the IT band across the tendon. Both positions squeeze the tendon for hours, at exactly the time the tissue needs to recover. Changing how you sleep is often the fastest way to reduce overall symptoms.
Can I sleep on my side with GTPS?
Yes, with some setup. Start on the non-painful side with a firm pillow between the knees and a second pillow between the ankles, keeping the top leg level with the pelvis rather than falling across the body. Some patients find a small pillow tucked behind them more comfortable than sleeping fully on the back. The goal is to stop the thigh crossing towards the other leg (adduction), the position that squeezes the gluteal tendons.
Why is walking uphill worse for my hip?
Walking uphill, climbing stairs and stepping onto a curb all ask more of the muscles on the side of the hip (abductors), which keep the pelvis level while you stand on one leg. In gluteal tendinopathy the tendon can be less tolerant of load for a while, so these tasks can push it past what it currently handles. Bergmann's study of four people with hip implants that measured force (Journal of Biomechanics, 2001) recorded roughly 238% of body weight through the hip joint during normal walking, and more on stairs. That is joint load rather than tendon load, but it shows how hard the hip muscles work. This is part of why building up exposure gradually, rather than avoiding these tasks, is the rehabilitation approach.
Are cortisone injections good for GTPS?
The LEAP trial (Mellor et al., BMJ 2018) compared education plus exercise with a single corticosteroid injection and with a wait-and-see approach. Education plus exercise gave better overall improvement than the injection at 8 weeks and at 52 weeks, and less pain at 8 weeks; by 52 weeks pain levels were similar. An injection can reduce pain in the short term, but it does not rebuild the tendon. I reserve injections for cases where pain is preventing someone from engaging with loading rehabilitation at all.
How long does gluteal tendinopathy take to heal?
Most patients see symptoms start to ease within 4 to 6 weeks of starting load management and isometric exercises (holds that do not move the joint). Building real tendon capacity typically takes 3 to 6 months, sometimes longer when symptoms have been present for over a year. Women after menopause may take longer because hormones affect tendon tissue. Sleeping through the night and walking uphill without an ache are the two markers I lean on to confirm the tendon has rebuilt meaningful capacity.
Should I stretch my IT band if I have lateral hip pain?
Generally no. Classic IT band stretches, like crossing one leg behind the other and leaning sideways, pull the thigh across towards the other leg (adduction), the exact position that squeezes the gluteal tendon against the bony point of the hip. Foam rolling directly over the outer hip does the same. Well-intentioned, but it often keeps the pain flared. Load management, strengthening that does not squeeze the tendon, and changes to posture are more productive.
Is walking safe with lateral hip pain?
Usually, in some form. Complete rest is rarely helpful, and losing fitness makes the problem worse. What helps is reducing what sets it off: avoid walking to the point of a flare, break up long walks, choose flatter routes in early rehab, and hold off on hill repeats until tolerance builds. I usually prescribe a specific daily walking dose and adjust it weekly based on how your symptoms respond.
Is GTPS more common in women?
Yes. Population research by Segal et al. (2007) reported an odds ratio of roughly 3.4 for women compared with men in adults aged 50 to 79. It is commonly seen in middle age and around menopause. Possible contributors include a wider pelvis, which increases the squeezing force through the IT band, and hormonal shifts that affect tendon collagen. The treatment approach is the same, but it does shape the conversation about timeline and expectations.
The science
The Science of Lateral Hip Pain & Gluteal Tendinopathy
Greater Pain Syndrome (GTPS), previously called "trochanteric ," is primarily a gluteal affecting the and minimus tendons at their insertion on the greater trochanter. For years, this condition was called "trochanteric bursitis," and the presumed treatment was rest, ice, and anti-inflammatory injections. Research has shifted this understanding: the primary issue is frequently not an inflamed but an irritated gluteus medius or minimus tendon (a gluteal tendinopathy). The bursa can become secondarily irritated, but it's rarely the main driver. That changes the treatment: a tendinopathy is managed by reducing compression and progressively strengthening the tendon, and rest on its own rarely settles it.
The condition involves a load-capacity imbalance where compressive forces (from positions that bring the IT band across the trochanter) and tensile loads exceed the tendon's ability to adapt. Postures that bring your thigh across the midline of your body can cause the (IT) band to compress the gluteal tendons against the hip bone, a key source of irritation in GTPS.
Weakness in the gluteus medius and minimus doesn't just cause local pain; it degrades movement quality throughout the . When these muscles aren't doing their job of stabilizing the pelvis, you can develop a "hip drop" or pattern. This leads to compensations everywhere: the tensor latae (TFL) and IT band may become overworked and tight, the low back can be subjected to shearing forces, and the knee can collapse inwards (), potentially contributing to pain.
Chronic tendon pain is frustrating because the pain is often worse with rest (like at night), creating a cycle of anxiety and poor sleep. Poor sleep, in turn, is known to increase pain sensitivity.
Contributing factors
The muscle functions as your hip's primary dynamic stabilizer during single-leg weight-bearing activities. During the stance phase of walking, your gluteus medius must generate enough force to prevent your pelvis from dropping toward the opposite side, a mechanical challenge that becomes more demanding as you walk faster, climb hills, or navigate uneven terrain. A small study using instrumented hip implants in four people measured joint contact forces of roughly 238% of body weight during normal walking (Bergmann et al., 2001). That is the load through the joint itself, not the load on the gluteal tendons, so it does not show the exact force on an individual tendon. What it does show is how hard the muscles around the hip work during ordinary walking.
In GTPS, the primary mechanical problem involves compression of the gluteal tendons against the . This compression occurs most significantly when your hip moves into adduction, bringing your thigh across your body's midline. Common culprits include standing with weight shifted predominantly to one side ("hanging on one hip"), crossing your legs while sitting, and particularly during side-lying sleep where the top leg falls forward across the midline. positions substantially increase compressive loads on the gluteal tendons compared to neutral alignment.
The (IT) band plays a crucial mechanical role in GTPS. When your hip adducts, the IT band moves posteriorly and compresses the gluteal tendons against the greater trochanter like a bowstring. This compression mechanism explains why activities involving repetitive hip adduction, such as running on banked surfaces, stairs, or prolonged standing on one leg, frequently trigger or worsen symptoms. Studies using dynamic ultrasound imaging show visible tendon compression under the IT band during hip adduction movements in symptomatic patients.
Single-leg loading amplifies these forces dramatically. When you stand on one leg, your gluteus medius must contract forcefully to prevent the opposite side of your pelvis from dropping, generating tensile loads through the tendon while simultaneously experiencing compressive forces from the IT band. This explains why activities like climbing stairs, running, or standing on one leg to put on shoes frequently reproduce pain. Strength, changes in activity and movement habits may all affect symptoms, and pain itself can reduce strength, so weakness can be both a contributor and a consequence.
Body weight can add to the load: the heavier the body, the more force the gluteus medius has to produce to keep the pelvis level when walking. The link between body mass index and GTPS is not consistent, though; in one large study (Segal et al., 2007) body mass index was not associated with GTPS once other factors were accounted for.
Sleep positioning creates sustained compression that explains the characteristic night pain in GTPS. When lying on the affected side, direct pressure compresses the tendon against the trochanter. When lying on the opposite side, if the top leg falls forward into hip adduction and internal rotation, the IT band tightens and compresses the gluteal tendons. This sustained compression during the hours you should be resting prevents tissue recovery and explains why GTPS patients often report that night pain is their most debilitating symptom.
Research
What the studies show
LEAP trial: education and exercise compared with an injection (Mellor et al., BMJ)
In 204 people with gluteal tendinopathy (irritated buttock tendons on the side of the hip), education plus exercise gave better overall improvement than a cortisone (corticosteroid) injection at 8 weeks and at 1 year, and less pain at 8 weeks. At 1 year pain was similar after the two treatments, and both were better than waiting.
Supports education and exercise as the first treatment, with an injection kept for selected cases.
Mellor R, Bennell K, Grimaldi A, et al. (2018). Education plus exercise versus corticosteroid injection use versus a wait and see approach on global outcome and pain from gluteal tendinopathy: prospective, single blinded, randomised clinical trial. BMJ. PMID: 29720374.
Gluteal tendinopathy: how it develops and how to manage it (Grimaldi and Fearon)
Describes how squeezing of the buttock tendons against the bony point of the hip (the greater trochanter), in positions where the thigh crosses towards the other leg (adduction), is a key contributor to gluteal tendinopathy. This supports managing load and avoiding positions that squeeze the tendon.
Guides the changes to daily positions and activities.
Grimaldi A, Fearon A (2015). Gluteal Tendinopathy: Integrating Pathomechanics and Clinical Features in Its Management. J Orthop Sports Phys Ther. PMID: 26381486.
Related Conditions
Conditions I commonly see alongside, or confused with, this one.
Getting back to it
Physiotherapy for lateral hip pain & gluteal tendinopathy, built around the activity you want back.
