
Femoroacetabular Impingement (FAI)
Femoroacetabular impingement (FAI) syndrome involves hip symptoms associated with contact between the ball and socket during movement. Groin pain may occur with squatting, low seats or turning. Diagnosis considers symptoms, examination and imaging together, because the same bone shapes are common in people who have no pain.
Key points
- What usually helps
- Physiotherapy that changes how you move and strengthens the hip, as the usual first step.
- What you can do now
- Get out of low cars one leg first. Sit higher for long stretches.
- How long it takes
- Pain often eases within 4 to 6 weeks; non-surgical care usually takes 3 to 6 months.
- When to see a doctor first
- Some signs need emergency care. Check the list before you start treatment.
Symptoms
Does this sound like you?
- Sharp, pinching groin pain when the hip bends deeply (not the constant, dull ache of arthritis)
- Pain with squatting, getting out of cars, or prolonged sitting in low chairs
- Clicking or catching: a click you can feel or hear with certain movements
- Gradually losing the ability to turn the hip inward (difficulty bringing the knee towards the opposite shoulder)
- Pain that appears with specific movements, particularly bending the hip deeply or turning it
Often alongside it
- Stiffness or loss of rotation in the hip
- Pain with sports that bend the hip deeply (soccer, hockey, yoga, dance)
- Showing where it hurts by curving a hand in a C shape from the groin to the side of the hip (the C-sign)
- Pain may spread to the buttock or the side of the hip
- Feeling like 'something is getting caught in there' or 'bony block'
- Growing difficulty sinking into deep squats or yoga poses
Often a story of frustration for young, active people. It's the soccer player who feels a sharp, pinching pain deep in their groin every time they strike the ball. It's the yoga enthusiast who can no longer sink into a deep squat without a block in the front of their hip. The pain is not a constant, dull ache like arthritis. It's a sharp, almost 'bony' block that appears with specific movements, particularly bending the hip deeply or turning it. Patients often tell me, 'It feels like something is getting caught in there,' and they'll make a 'C' sign with their hand, wrapping it from the front of the hip to the side to show me exactly where they feel it. It only hurts with specific movements, especially deep squatting, getting out of a car, or sitting for long periods in a low chair.
Before using this comparison, check when these symptoms need a doctor first.
When to see a doctor first
Go to emergency
A limping child or teenager with sudden hip, thigh or knee pain, who cannot put weight on the leg, whose leg looks deformed, or who has a fever and feels unwell
Go to emergency now
A suspected slipped growth plate at the hip (SCFE)
Do not let the child walk on the leg, and seek emergency assessment today. In a teenager this can show up as a limp with hip, groin, thigh or knee pain, even when they can still walk
Get seen today
Groin or hip pain in a runner or athlete that builds with each session, hurts when hopping on that leg, or follows a sudden jump in training
Possible stress fracture of the hip (femoral neck). Stop running and all impact exercise, keep weight off the leg, and get medical assessment today. If you cannot put weight on the leg or the pain is severe, go to emergency. An early X-ray can look normal
A hot, swollen or very painful hip, a fever or feeling unwell, or you cannot put weight on the leg
Possible infection or fracture. Get medical assessment today, or go to emergency if you feel unwell or cannot bear weight. Infection is possible even without a fever
Check with your doctor
A child or teenager with a new limp that has no clear explanation
Get a prompt medical assessment before starting exercises. A hip problem can be felt only in the thigh or knee
The hip locks or gives way
Possible loose fragment in the joint (loose body) or a significant tear of the rim of cartilage around the socket (labral tear). See your family doctor or a sports medicine physician
Severe, constant pain that does not change with movement, or night pain with weight loss
See your family doctor promptly to rule out other causes
Treatment
How it is treated
Main approach. Physiotherapy built on changing how you move and gradually strengthening the hip can improve symptoms for many people with hip impingement (FAI syndrome), and it is the usual first step. In the UK FASHIoN trial, keyhole hip surgery (arthroscopy) gave a modestly larger improvement at 12 months.
Alongside it. Changing activities to stay out of the positions that pinch, together with rebalancing the strength of the hip muscles, reduces pain and lets you return to sport within safe ranges of movement.
Managing it over time. Keeping up hip strength, and managing how often you bend the hip deeply while turning it, can help keep symptoms settled once they have improved.
A typical rehabilitation progression
Three phases, from settling symptoms to returning to full activity.
Recovery from femoroacetabular impingement is usually staged: calm the symptoms first, then rebuild the strength and capacity of the area, then return to your full activities. The phases below show how that can progress.
Phase 1Settling the Painful Pinch (Weeks 1 to 6)
The 2016 international agreement on hip (the Warwick Agreement, Griffin and colleagues) defines FAI as a syndrome that needs symptoms, examination findings and imaging findings together, and lists non-surgical care, including physiotherapy-led rehabilitation, as a main treatment option. This first block is about finding the positions that reliably bring on the pain, taking them out for a while, and rebuilding good control of the buttock muscles (glutes) away from deep hip bending and turning the hip inward (internal rotation). Most patients see a meaningful drop in day-to-day catching within 4 to 6 weeks.
Example exercises
- Lying face down, lifting the leg behind you with the buttock muscles (prone hip extension), 3 sets of 12, keeping the pelvis still so the lower back does not take over
- Lying on your side, lifting the top leg (sidelying ) with the pelvis tilted slightly back, which favours the muscle on the side of the hip () over the small muscle at the front and side of the hip (tensor fasciae latae), 3 sets of 12 per side
- Pushing the leg out to the side and back against a band and holding still ( hip abduction and extension), 4 sets of 30 seconds, to load the back of the hip without going into the painful pinch range
- Practising the hip hinge (bending forward from the hips with a straight back) to a bench, in place of deep squats for now, 3 sets of 10
- Checking the height of your car seat, desk chair and couch so you are not sitting in the pinch position for hours each day
Possible progression milestones
Catching and sharp pinching rare in normal daily movement, sitting through an hour-long meeting without shifting, and balancing on one leg for 30 seconds without bringing on groin pain.
Phase 2Building Strength at the Back of the Hips and Thighs (Weeks 7 to 16)
The evidence on non-surgical care for FAI syndrome is still developing. The UK FASHIoN trial (Griffin and colleagues, Lancet 2018) reported that keyhole surgery (arthroscopy) gave larger improvements than personalised hip therapy at 12 months, while a trial by Mansell and colleagues (2018) found no clear difference between arthroscopy and physical therapy at 2 years. These trials compared specific rehabilitation programs with surgery and reached different results, and they do not establish the best amount of exercise for every person. A structured program that builds up gradually remains a reasonable first option, with reassessment if progress is limited. I treat this phase as real strength work, not just drills to switch muscles on, while keeping the range short of the painful pinch.
Example exercises
- Squat to a box holding a weight at the chest (goblet box squat), with the box high enough that the hip stops bending before the painful pinch, 3 sets of 8 with a 6 to 12 kilogram kettlebell
- Split squat with the back foot raised on a bench (rear-foot-elevated split squat), foot flat, staying tall so the hip does not bend forward, 3 sets of 8 per side
- Romanian deadlift (lowering a weight by hinging at the hips, knees fairly straight) with a light to moderate load, focusing on the hip hinge and the muscles at the back of the hips and thighs, 3 sets of 8
- Step-ups onto a low step with control of the pelvis, raising the height only while the movement stays controlled and comfortable, 3 sets of 8 per side
- Standing with a band, moving the leg out to the side and back (hip abduction and extension), 3 sets of 12 per side, to keep working the muscles that make those movements
Possible progression milestones
Loading a goblet squat and Romanian deadlift at loads relative to body weight without groin pain, step-ups with the pelvis staying level, and weekly training that does not leave a flare the next day.
Phase 3Returning to Sport and Tasks at the Ends of the Range (Months 4 to 6+)
Once strength is solid, the program adds turning, speed and controlled practice in the ranges your sport or daily life actually demands. If physiotherapy has been progressed properly for about 3 to 6 months and you still cannot load the hip or play, that is when I refer for a surgical opinion. This fits the Warwick Agreement's view that the choice between non-surgical care and keyhole surgery (arthroscopy) is a shared decision with the patient.
Example exercises
- Controlled turning exercises, such as rows with a twist on a cable machine or medicine ball throws with a turn, 3 sets of 6 per side
- Gradually deeper split squats and single-leg squats, staying short of the painful pinch
- Sport drill exposure: skating stride, kicking, change of direction, built up across weeks
- Jumping exercises () when appropriate: box jumps, bounds and low hops
- Full return to training with a plan that builds up step by step, rather than a single all-out session
Possible progression milestones
Back to sport, work or your chosen activity at the amount you want, confidence pivoting and changing direction (cutting), and managing flares yourself with the exercises you already have.
What you can do now
- Get out of low cars one leg first. A low car seat plus turning to get out bends the hip deeply, brings the knee across your body and turns the hip inward all at once, which is the combination this hip shape tolerates poorly. Raise the seat, slide one leg out first, and stand up before you turn.
- Sit higher for long stretches. Low chairs, low couches and low car seats keep the hip bent into the pinch position. Check the height of your car seat, desk chair and couch so you are not sitting in that position for hours each day.
- Squat to a box, hinge to lift. You usually do not need to stop squatting or deadlifting, just change the range. Squat to a box that stops your hip before the painful pinch, and lift by hinging at the hips with the knees fairly straight, as in a Romanian deadlift, which tends to be well tolerated.If a squat brings on the sharp pinch, use a higher box.
- Swap hard hip flexor stretches for strength work. Stretches pushed to the limit, such as the couch stretch or a deep lunge, often flare an irritable FAI hip. Controlled strength work that moves the leg backward, such as lying face down and lifting the leg behind you, takes the front of the hip through a useful range and is less likely to flare it.If stretching helps the other side or your lower back, keep it there, but not hard into the painful hip.
- Adjust yoga and pilates, do not force depth. Deep or forced hip positions, including some versions of pigeon or lotus, can aggravate an irritable hip. Changing the depth and adding support usually let you keep practising.Do not force the hip into a painful end position.
What I use in clinic
- Glute and Deep Hip Strengthening. Strengthening the buttock (glute) and deep hip muscles improves control of the ball of the hip joint (the femoral head), makes the hip more stable as it moves, and reduces compensating movement patterns. It starts with holds that do not move the joint (isometric exercises) and progresses gradually, with the focus on quality over quantity.
- Manual Therapy. Hands-on soft tissue work and joint mobilization can improve movement and ease protective muscle tension (guarding).
Recovery
How long it takes
Non-surgical care usually takes 3 to 6 months. Pain often eases within 4 to 6 weeks of changing how you move. Getting back to high-level activity requires building enough strength and control.
Many people with FAI syndrome improve with physiotherapist-led care. A surgical opinion is usually considered when a well-progressed program of about 3 to 6 months has not given enough improvement.
What changes the timeline
- How marked the changes in bone shape are
- Whether the labrum (the rim of cartilage around the socket) is also injured
- What your sport or activities ask of the hip
- Sticking with the changes to how you move
- Hip muscle strength and control
- How long you have had symptoms
How I track it. I track how much the pain gets in the way of the tasks that matter to you, how well you move when I test those tasks in clinic, and how confident you feel in daily activities
Similar conditions
Conditions that can feel similar
- Hip Osteoarthritis
- Older people, a constant groin ache rather than sharp catching, longer morning stiffness, and rotation lost more evenly in every direction when the examiner moves the hip.
- Isolated Labral Tear Without FAI Morphology
- Similar catching and C-sign, but imaging shows no significant extra bone at the hip joint (cam or pincer shape). Symptoms may have started more clearly with an injury.
- Iliopsoas Tendinopathy or Snapping Hip
- Pain at the front of the hip when lifting the leg against resistance, often with a snap you can hear or feel as the tendon crosses the ball of the hip (the femoral head). It is typically worse with repeated hip bending rather than deep bending combined with turning.
- Adductor-Related Groin Pain
- Pain on the inner thigh and at the front of the pelvis where the two pubic bones meet (the pubic symphysis). Squeezing the knees together against resistance (the squeeze test) brings it on, rather than the FADIR hip test. Common in field sports.
- Athletic Pubalgia (Core Muscle Injury)
- Pain in the lower abdomen and groin crease, worse with straining or bearing down (the Valsalva manoeuvre), sprinting and kicking, rather than with deep hip bending. Pressing over the lower abdominal muscle (rectus abdominis) and the pubic bone (pubic tubercle) is tender.
- Lumbar Referral from L1 to L3
- Pain at the front of the thigh that changes when the lower back bends backward, the hip moves fully when the examiner moves it, and the FADIR test does not bring on the usual pain.
Questions
What patients ask me most
If I have cam or pincer morphology on imaging, do I definitely have FAI?
No. The Warwick Agreement is explicit that FAI is a syndrome that needs symptoms, plus findings on examination, plus findings on imaging. A large portion of adults without symptoms have a cam or pincer bone shape and live without hip pain. Shape alone does not diagnose this. What matters is whether the hip is painful every time it is put in the pinch position, and whether that matches your day-to-day complaints.
Should I just have hip arthroscopy?
Sometimes that is the right call, but not as a first step. The UK FASHIoN trial (Griffin et al., Lancet 2018) favoured keyhole surgery (arthroscopy) over personalised hip therapy at 12 months. Mansell et al. (AJSM 2018) found no significant difference between arthroscopy and physical therapy at 2 years, although many people switched between groups. The trials tested specific rehabilitation programs and reached different results, so neither settles the question for every person. My approach, consistent with the Warwick Agreement, is about 3 to 6 months of genuinely progressed loading and movement retraining first, and surgery considered only if that fails or the patient's life demands do not allow waiting.
Why does getting out of a low car hurt so much?
A low car seat plus turning to get out bends your hip deeply, brings the knee across your body and turns the hip inward, all at the same time. That is the exact combination that a cam-type bone shape does not tolerate well. Raising the seat, sliding one leg out first before turning, and standing up before turning often makes a big difference until strength catches up.
Should I stop squatting and deadlifting?
Usually not stop, just change the range. Squats to a box that stops your hip bending as far as the painful pinch are often well tolerated. Romanian deadlifts, which focus on hinging at the hips and keep the knee fairly straight, tend to be well tolerated. I treat lifting as part of the rehab rather than something to avoid.
Are hip flexor stretches safe for FAI?
Hard hip flexor stretches taken to the limit, such as the couch stretch or a deep lunge, push the front of the hip to its limit and often flare an irritable FAI hip, even though the pinch itself happens when the hip bends and turns. I usually swap them for controlled strength work that moves the leg backward (hip extension), which works the front of the hip through a useful range and is less likely to flare it. If stretching is helping the other side or the lower back, keep it there, just not aggressively into the painful hip.
Can I still do yoga or pilates?
Often yes, with edits. Deep or forced hip positions, including some versions of pigeon or lotus, can aggravate an irritable hip. Changing the depth, adding support, and not forcing a painful end range usually let people keep practising. I coach patients to own the modifications rather than stop the practice.
How long before I know if conservative care is going to work?
Most patients with FAI syndrome notice a meaningful change in day-to-day catching within 4 to 6 weeks of proper load management and targeted strengthening. Full strength gains and confident return to sport typically take 3 to 6 months. If after about 3 to 6 months I still cannot progress your loading without flaring the hip, that is when a surgical opinion becomes relevant.
The science
The Science of Femoroacetabular Impingement (FAI)
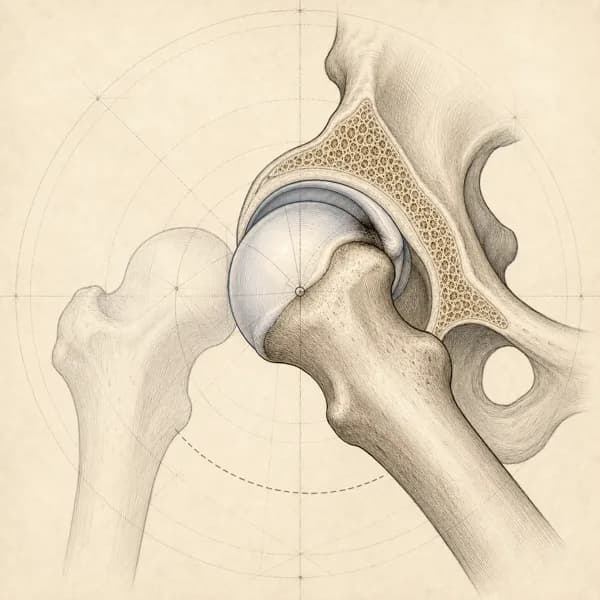
Femoroacetabular (FAI) syndrome involves abnormal contact between the femoral neck and rim during hip movement, specifically during deep hip flexion and internal rotation. The biggest misconception is that having a certain hip shape (a "" or "" morphology on an X-ray) automatically means you will have pain. It does not: many elite athletes and pain-free individuals have these shapes. FAI syndrome means a specific hip shape plus symptoms plus clinical signs. The shape alone does not explain the pain; how the hip is loaded in its painful positions matters too.
Two main types exist: CAM (extra bone on femoral head-neck junction creating a "bump" that makes contact with the socket during deep flexion) and PINCER (a socket that covers too much of the ball, so the rim meets the femoral neck earlier in the movement). Mixed types with both morphologies are common. The cam shape can make contact with the socket and (cartilaginous ring around the socket) during deep hip flexion, leading to a pinching sensation and potential stress on the labrum.
To avoid the pinching sensation, the body develops compensation strategies. A common one is to create extra movement through the low back and pelvis: instead of flexing at the hip to squat, a person might excessively round their (butt-winking). Over time, this can lead to low back pain. Similarly, a stiff and painful hip can cause the knee to collapse inwards during activities like running or landing, potentially contributing to knee pain.
When a specific movement consistently causes sharp pain, the brain learns to fear and avoid it. This leads to protective muscle guarding, where muscles around the hip (like hip flexors and ) become chronically tense in anticipation of pain. This tension can then become a secondary source of pain itself.
Contributing factors
The relationship between hip shape and symptoms in FAI is fundamentally about mechanical load in specific positions. Biomechanical research indicates that hip and pelvis can be altered in FAI syndrome even during tasks that don't reproduce the anterior position, meaning movement patterns can change more globally, not just in deep flexion positions.
During deep hip flexion beyond approximately 90 degrees, common in activities like squatting, getting into cars, or certain yoga poses, the (bony prominence on the femoral head-neck junction) makes premature contact with the rim and . This creates abnormal shear forces on the labrum, which can lead to progressive damage over time. Research using motion capture and pressure sensors shows that in cam-type FAI, peak stress occurs during the transition from hip flexion to extension, particularly when combined with internal rotation.
The (acetabular over-coverage) creates a different mechanical problem: the deeper socket provides excessive anterior coverage, causing the acetabular rim to contact the femoral neck earlier in the flexion range. This can trap the labrum between the two bony surfaces, creating a pinching mechanism. Studies show that even moderate hip flexion angles (70-90 degrees) can generate impingement in pincer-type morphology.
Your body develops sophisticated compensation strategies to avoid these painful positions. One of the most common patterns I observe is excessive flexion during squatting (often called "butt-winking"), where instead of achieving the required hip flexion, you create extra movement through your lower back. This compensatory pattern explains why many FAI patients develop concurrent low back pain. Research demonstrates that FAI patients exhibit significantly reduced hip flexion range during functional tasks like squatting, with compensatory increases in anterior pelvic tilt and lumbar flexion.
The altered loading extends beyond the hip joint itself. Studies on gait mechanics in FAI show reduced hip extension during walking and running, leading to compensatory strategies including increased pelvic drop on the affected side and altered knee mechanics. These adaptations can create a cascade of issues up and down the : knee collapse, reduced push-off power, and increased reliance on the quadriceps rather than the posterior chain muscles.
Activity demands significantly influence symptom development. Athletes in sports requiring repeated deep hip flexion and rotation, such as ice hockey goalies, soccer players and dancers, load the hip in the impingement position over and over. A hockey goalie drops into a deep butterfly position many times in a game, and each repetition can stress the hip if cam or pincer morphology is present.
Research
What the studies show
International agreement on hip impingement syndrome (Warwick Agreement)
An international panel of 22 clinicians from nine countries and five specialties, with one patient, agreed that diagnosing FAI syndrome needs symptoms, positive findings on examination and imaging findings together. It described non-surgical care, rehabilitation, and keyhole (arthroscopic) or open surgery as suitable treatments, without ranking them.
Sets the standard for diagnosis, so a hip shape seen on imaging is not enough on its own, and lists non-surgical care and rehabilitation alongside surgery as accepted options.
Griffin DR, Dickenson EJ, O'Donnell J, et al. (2016). The Warwick Agreement on femoroacetabular impingement syndrome (FAI syndrome): an international consensus statement. Br J Sports Med. PMID: 27629403.
UK FASHIoN trial: keyhole hip surgery or physiotherapy (Griffin et al., Lancet)
Both keyhole hip surgery (arthroscopy) and a personalised physiotherapist-led program improved hip-related quality of life at 12 months. Arthroscopy gave a modestly larger improvement, 6.8 points more on a hip quality-of-life questionnaire.
Both approaches improved symptoms, and surgery gave a modest extra benefit at 12 months, so the choice between them is a shared decision rather than one clear answer.
Griffin DR, Dickenson EJ, Wall PDH, et al. (2018). Hip arthroscopy versus best conservative care for the treatment of femoroacetabular impingement syndrome (UK FASHIoN): a multicentre randomised controlled trial. Lancet. PMID: 29893223.
Related Conditions
Conditions I commonly see alongside, or confused with, this one.
Getting back to it
Physiotherapy for femoroacetabular impingement (FAI), built around the activity you want back.
