
PCL Injuries
The PCL (posterior cruciate ligament) helps steady the knee by resisting backward movement of the shinbone. A fall onto a bent knee or a blow to the front of the shin can injure it, causing pain, swelling or unsteadiness. Assessment checks for other injuries; the exercise phases here cover an isolated injury managed without surgery.
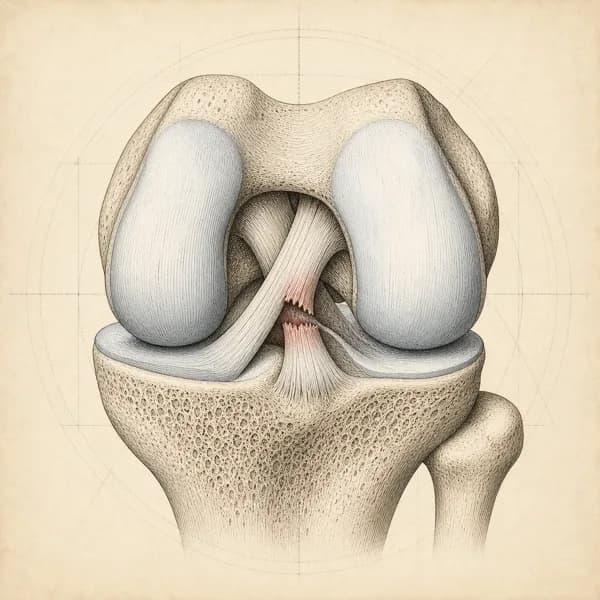
Key points
- What usually helps
- Rehab built around the front thigh muscle. Most PCL injuries on their own avoid surgery.
- What you can do now
- Keep the knee moving, without forcing it. Skip hamstring exercises early on.
- How long it takes
- Return to sport is typically possible after 3 months; full function often within 4 to 6 months.
- When to see a doctor first
- Some signs need emergency care. Check the list before you start treatment.
Symptoms
Does this sound like you?
- Pain at the back of the knee that may be vague and hard to pinpoint
- A sense that the knee is unstable, especially when slowing down or going downhill
- Difficulty with activities that bend the knee deeply, like squatting or kneeling
- Pain and stiffness after sitting or resting for a long time
- Swelling that may be minimal compared to other knee injuries
Often alongside it
- Weakness and loss of bulk in the front thigh muscle (quadriceps)
- Hip or ankle problems from moving differently to protect the knee
- Pain around the kneecap (patellofemoral pain) because the knee moves differently
- General sense of knee 'looseness' during activity
- Difficulty with sudden changes of direction
I often see patients who can describe a specific injury but had fairly mild symptoms at first. Many do not realize how serious the injury is at the start, because PCL tears can cause less dramatic symptoms than ACL injuries. The instability shows up during activities that strain the structures at the back of the knee.Book an assessment for PCL injuries
When to see a doctor first
Go to emergency
After a major injury, the knee looked dislocated or shifted out of place, or it feels grossly unstable or loose in more than one direction
Possible knee dislocation or injury to more than one ligament. Go to emergency now, even if the knee has moved back into place, so the blood vessels and nerves behind the knee can be checked
A cold, pale or numb foot, or foot drop, after the injury
Possible damage to the artery or nerve behind the knee. Go to emergency now
Calf pain, swelling or warmth, especially while in a brace or after surgery
Possible blood clot. Same-day medical assessment; sudden shortness of breath or chest pain means go to emergency now
Get seen today
You cannot put weight on the leg after the injury
Possible fracture or more serious knee injury. Same-day medical assessment
After surgery: a fever, or a wound that is red, hot, leaking or increasingly painful
Possible infection. Contact your surgical team the same day, or go to emergency
Check with your doctor
The knee locks and will not straighten
Possible meniscus tear blocking movement. See your family doctor or a sports medicine physician within a few days
No functional improvement after 3 months of appropriate rehabilitation
I flag it to your family doctor so you can be referred for imaging and an orthopaedic opinion
Treatment
How it is treated
Main approach. Most injuries to the PCL alone do well with rehab built around the front thigh muscle (quadriceps), and surgery is avoided in the majority of cases.
Alongside it. Early on, protecting how much weight goes through the leg and not strengthening the back thigh muscles (hamstrings) lets the ligament heal, while strengthening the quadriceps helps make up for the lost stability.
Managing it over time. Training in landing technique and knee control (neuromuscular training) may reduce the risk of PCL injury in higher-risk sports.
A typical rehabilitation progression
Three phases, from settling symptoms to returning to full activity.
Recovery from PCL injuries is usually staged: calm the symptoms first, then rebuild the strength and capacity of the area, then return to your full activities. The phases below show how that can progress.
Phase 1Protect the Ligament and Wake Up the Quadriceps (Weeks 0 to 6)
Limit the shin bone sagging backward (posterior tibial translation), keep the knee moving without forcing a deep bend, and get the front thigh muscle (quadriceps) contracting confidently again. The rehab protocol from Pierce and colleagues (2012) emphasizes lying face down (prone positioning), exercises led by the quadriceps, and avoiding contracting the hamstrings on their own during this window.
Example exercises
- Quad sets (tightening the thigh muscle with the leg straight) and straight leg raises lying on your back, with a small towel roll under the ankle to support the knee fully straight
- Protected knee bending lying on your front, done passively or with a therapist's help within the range your clinician or surgeon has set, with no active hamstring pulling until you are cleared and no forcing into deep bending
- Gently moving the kneecap in all four directions (patellar mobilizations) to keep the thigh muscle and its tendon gliding
- Mini-squats and wall sits with only a slight bend, keeping the shin bone forward rather than letting it sag backward
- A brace that pushes the shin bone forward (dynamic PCL brace) for walking and daily activity, for Grade II and III injuries
Possible progression milestones
The knee straightens fully, matching the other side, and bends to about 110 to 120 degrees; little or no swelling in the joint; the thigh muscle contracts cleanly with no sag when you lift the straight leg; and pain-free walking in the brace, as your surgical or non-surgical protocol allows.
Phase 2Strength, Single-Leg Control, and Return to Running (Weeks 6 to Month 4)
Build real strength in the front thigh and hip, slowly bring back controlled loading of the hamstrings, and prepare the knee for running. Non-surgical rehab protocols that steadily build up exercises with the foot on the ground (closed-chain), while keeping the shin bone supported forward, are associated with good function.
Example exercises
- Leg press, squats with the heels raised, and Bulgarian split squats (a split squat with the back foot on a bench), led by the front thigh muscle with the shin bone kept forward
- Step-ups and step-downs, watching that the knee stays in line and the shin bone does not sag backward
- Hip thrust or bridge variations selected by your clinician once this loading is permitted. These exercises can also load the hamstrings, so the position and dose must fit your protection plan
- Bringing back hamstring work gradually, starting with holds with the leg straighter (long-lever isometrics) and moving to curls (lowering your body forward from kneeling, with the ankles held) in the late phase only
- Return-to-running program beginning with treadmill walk-jog intervals once strength criteria are met, typically around month 3
Possible progression milestones
Front thigh strength approaching 85 to 90 percent of the other leg on a strength-testing device, a pain-free single-leg squat to 60 degrees with the knee in line, straight-line jogging without swelling afterward, and acceptable stability when the knee is tested in clinic.
Phase 3Return to Sport and Performance (Month 4 to 6+)
Complete hop and strength testing, bring back cutting and slowing down, and add the demands of your sport. Measurable discharge criteria drive clearance, not the calendar.
Example exercises
- The full set of hop tests (single hop, triple hop, crossover hop and 6 metre timed hop), aiming for the injured leg to reach at least 90 percent of the other leg
- Front thigh strength testing with a handheld device or a machine (isokinetic testing), aiming for at least 90 percent of the other leg
- Jumping and landing drills (), from two-leg to one-leg landings, adding slowing down and bounding
- Change-of-direction work, starting with planned cuts at 45 and 90 degrees and progressing to cutting in reaction to a partner or signal
- Sport-specific drills and graded return-to-contact progression for collision athletes
Possible progression milestones
At least 90 percent of the other leg on strength and hop tests, acceptable stability when tested in clinic (some looseness can remain after a PCL injury even when function is good), clean movement when changing direction, no joint swelling after training, and feeling confident in the knee during sport-specific loads.
What you can do now
- Keep the knee moving, without forcing it. Bending and straightening the knee within the range you have been given helps prevent stiffness. Avoid forcing it into a deep bend early on, including deep squats.In the early weeks, knee bending is done passively or with help, and active hamstring exercise waits until you are cleared.
- Skip hamstring exercises early on. The back thigh muscles (hamstrings) pull the shin bone backward, which strains the healing PCL. In the first several weeks, leave out hamstring curls and heavy Romanian deadlifts; hamstring work comes back later, when it is appropriate.After PCL surgery, your surgeon's protocol sets when hamstring work can start.
- Do your quadriceps exercises consistently. The front thigh muscle (quadriceps) resists the shin bone sliding backward, which is the movement a damaged PCL fails to stop. Keeping up your quadriceps exercises helps the shin bone stay where it should during walking, stairs and squatting.
- Use your PCL brace as advised. For Grade II and III injuries, a brace that pushes the top of the shin bone forward can help in the first 6 to 12 weeks, by reducing the backward sag of the shin bone while loading begins. The aim is to rely on your own strength and control later on, rather than the brace.
- Watch for calf swelling or warmth. Calf pain, swelling or warmth, especially while you are in a brace or after surgery, needs a same-day medical assessment for a possible blood clot. Sudden shortness of breath or chest pain means go to emergency now.
What I use in clinic
- Quadriceps-Focused Strengthening Program. Strong front thigh muscles (quadriceps) help hold the shin bone forward and can partly make up for a stretched or torn PCL. The focus is on good-quality muscle contractions.
- Treatment Without Surgery. Most injuries to the PCL alone are managed without surgery, and long-term follow-up shows good knee function in many people.
- Progressive Functional Training. Jumping and landing drills (plyometrics) and sport-specific drills are added in the later phases to prepare the knee for sport.
- Support Bracing in Early Phase. PCL braces that push the shin bone forward during the early healing phase can help your confidence as loading begins, alongside a physiotherapy-led exercise program.
- Hamstring Avoidance Protocol. Not actively working the back thigh muscles (hamstrings) in the early stages stops them pulling the shin bone backward, which strains the healing PCL.
Recovery
How long it takes
Without surgery, return to sport is typically possible after 3 months, and full recovery of function is often reached within 4 to 6 months.
Unlike the ACL, the PCL has some capacity to heal, and many isolated injuries regain good function with rehabilitation even if some looseness remains on testing.
What changes the timeline
- Grade I and II injuries to the PCL alone usually have an excellent outlook with non-surgical treatment
- Getting front thigh (quadriceps) strength back to more than 90% of the other leg (the leg symmetry index) matters a great deal for return to sport
- Starting appropriate rehabilitation early improves outcomes
- Keeping up with the strengthening program matters a great deal
- A meniscus or other ligament injury at the same time may affect the timeline
How I track it. I track how your front thigh (quadriceps) strength builds, how stable the knee is during everyday and sport movements, and your confidence with activities that used to make the knee feel unstable
Similar conditions
Conditions that can feel similar
- ACL Tear
- A large amount of bleeding into the joint soon after injury (hemarthrosis), an audible pop, the shin bone moving too far forward or the knee shifting on testing (positive Lachman and pivot shift tests), and marked twisting instability when changing direction. PCL tears typically show less dramatic swelling, and the shin bone moves or sags backward on testing (posterior drawer test or sag sign) rather than forward.
- Posterolateral Corner Injury
- The outer side of the knee opens up when the knee is pushed outward (varus instability), the shin turns outward further than normal with the knee bent 30 degrees (dial test), and it often happens together with a PCL injury. When the shin turns out too far at both 30 and 90 degrees of knee bend, it suggests both the PCL and the posterolateral corner (PLC) are injured, which changes decisions about surgery.
- Posterior Meniscal Root Tear
- Pain at the back of the knee with catching or locking, without the typical way a PCL is injured. Imaging shows the meniscus pushed out of place (extrusion) or torn from its anchor point (the root), and the posterior drawer test is normal. It can feel like the vague ache at the back of the knee from a PCL injury, but the shin bone does not move backward on examination.
- Proximal Tibiofibular Joint Injury
- Pain and tenderness at the top of the thin outer shin bone (the proximal fibula) rather than in the hollow at the back of the knee (the popliteal fossa). The top of the fibula moves too far forward or backward when pressed, and the injury is often a twist with the knee bent and the foot turned in. It can happen together with an LCL or posterolateral corner injury.
- Baker's Cyst or Posterior Capsule Strain
- Fullness and tightness at the back of the knee, often caused by a problem inside the joint such as a meniscus tear or arthritis, without the backward shin movement of a PCL injury on testing. It usually comes on gradually or after activity, rather than from a specific dashboard-type injury.
Questions
What patients ask me most
Do I need surgery for a PCL tear?
Grade I and II injuries to the PCL alone respond well to treatment without surgery in most cases, and even many Grade III tears of the PCL alone do surprisingly well with a quadriceps-focused program. Pierce et al. (KSSTA 2012) and Wang et al. (Curr Rev Musculoskelet Med 2018) both support non-surgical care as the default when only the PCL is injured, reporting good function and high return-to-sport rates. Surgery becomes more likely when the PCL injury comes with ACL, posterolateral corner or inner-side ligament damage, or when the knee keeps slipping backward and limits daily life after a full rehabilitation trial.
Why is my knee pain less dramatic than my friend's ACL tear?
PCL injuries tend to be quieter than ACL tears, which is part of why they are missed. Swelling is often modest, the classic pop is less common, and many people describe a vague ache behind the knee with a sense of looseness rather than obvious instability. The usual causes are a direct blow to the front of a bent knee, a dashboard-style impact, or a fall onto a bent knee with the foot pointed down. If any of that matches your story and the knee has not felt right, it is worth a careful exam, including tests that check whether the shin bone moves or sags backward (posterior drawer test and sag sign).
Why is the rehab so quadriceps-focused?
Your front thigh muscle (quadriceps) actively resists the shin bone (tibia) sliding backward, which is exactly the movement a damaged PCL fails to stop. Stronger quadriceps means the shin bone stays where it should during walking, stairs, squatting and sport, even if the ligament itself never becomes fully tight again. That mechanical logic is why most of the evidence, and the Logerstedt JOSPT clinical practice guideline, rely heavily on progressive quadriceps loading as the central treatment.
Why am I being told to avoid hamstring exercises early on?
The hamstrings pull the shin bone (tibia) backward, which is the exact direction of strain the healing PCL cannot tolerate well. In the first several weeks I avoid hamstring curls on their own and heavy Romanian deadlifts, not because hamstrings are bad but because the timing is wrong. As healing progresses, hamstring work is introduced when it is appropriate and progressed in ways that limit strain on the healing ligament, and by the later phases of rehabilitation they are trained normally. After PCL surgery, your surgeon's protocol sets when hamstring work can start.
How long until I can return to sport?
For Grade I and II injuries to the PCL alone, return to sport is often possible around 3 months once strength and control criteria are met. Grade III injuries to the PCL alone typically take 4 to 6 months, sometimes longer for sports with sudden changes of direction and twisting. The timeline depends more on measurable markers than on a calendar: front thigh (quadriceps) strength above 90 percent of the other leg, pain-free single-leg work, and a return-to-running progression the knee tolerates.
Do I need a brace?
Dynamic PCL braces that push the top of the shin bone forward can be useful during the first 6 to 12 weeks of healing, particularly for Grade II and III injuries, because they reduce the shin bone sagging backward while loading begins. I do not use them forever. The aim is to rely on quadriceps strength and balance and control by the later phases rather than on external support.
Will I get arthritis from this?
Long-term data show a modest rise in osteoarthritis seen on X-ray after PCL injury, even with treatment without surgery, more so when there is also meniscus or cartilage damage. That said, many people keep good function, as they rate it themselves, for more than a decade after a PCL-only injury when rehabilitated well. This is part of why I take the quadriceps program seriously. Using the muscles to control where the shin bone sits is the most practical tool for protecting the joint surface over time.
The science
The Science of PCL Injuries
(PCL) injuries involve damage to the ligament that prevents excessive backward movement of your tibia relative to your femur. The PCL is the strongest ligament in your knee and has a better blood supply than the ACL, giving it better healing potential when injured.
PCL injuries are graded from I to III based on severity: Grade I involves stretching with microscopic tears, Grade II involves partial tearing with some functional loss, and Grade III represents complete rupture. Unlike ACL injuries, isolated PCL tears have an excellent capacity for healing due to their rich vascular supply.
The mechanism of injury typically involves a posteriorly directed force on the proximal tibia, such as falling onto a bent knee or the shin striking a hard edge. Sports injuries often occur during hyperflexion or hyperextension movements, particularly in contact sports.
The PCL works in conjunction with other knee structures to provide stability. When injured, the quadriceps muscle becomes crucial as it can partially compensate for PCL function by preventing excessive posterior tibial translation during functional activities.
Contributing factors
Your PCL serves as the primary restraint against posterior translation of the tibia, particularly when your knee is flexed beyond 30 degrees. Unlike the , which is tight in extension, the PCL becomes increasingly tight as the knee flexes, with maximum tension occurring at 90 degrees of flexion.
The quadriceps muscle group, particularly the vastus medialis and vastus lateralis, can provide some functional replacement for a damaged PCL by preventing the femur from sliding forward on the tibia. This is why quadriceps strengthening is the cornerstone of PCL rehabilitation.
During normal gait, the PCL experiences loads of 0.5-1 times body weight, but during activities like squatting or climbing stairs, these forces can increase to 2-3 times body weight. Understanding these loading patterns is crucial for designing appropriate rehabilitation programs.
The posterior drawer test demonstrates the primary dysfunction in PCL injuries: when you sit with your knee bent and someone pushes your shin backward, there's excessive movement compared to the uninjured side. However, this may not translate to significant functional problems in daily activities.
Research
What the studies show
Good long-term knee function after treatment without surgery for an injury to the PCL alone
A study followed 68 people with a recent injury to the PCL alone, treated without surgery (Shelbourne and colleagues, American Journal of Sports Medicine, 2013). At an average of 17 years later, their average score on a knee questionnaire they rated themselves was 73.4 out of 100. Front thigh (quadriceps) strength averaged 97% of the other leg, everyone kept full knee movement, and 11% had moderate to severe osteoarthritis on X-ray.
Supports non-surgical rehab focused on the front thigh muscle for an injury to the PCL alone, while being honest that some people develop arthritis changes over the long term.
Shelbourne KD, Clark M, Gray T. Minimum 10-year follow-up of patients after an acute, isolated posterior cruciate ligament injury treated nonoperatively. Am J Sports Med. 2013;41(7):1526-1533. PMID: 23652263.
Guides on knee pain
Longer explanations of symptoms and scan-report wording.
- Pain Right Below the KneecapA single tender spot below the kneecap that flares with jumping, stairs, or deep squats. Most commonly patellar tendinopathy in active adults, and growth-plate conditions in young athletes.
- Suprapatellar Effusion (Fluid on the Knee)Extra fluid inside the knee joint, seen in the pouch above the kneecap. What the size words on a report mean, the usual causes by how quickly the swelling came on, and when to see a doctor first.
- Joint Space Narrowing in the KneeThe gap between the bones looks thinner than expected on an X-ray. What medial, tricompartmental and the severity words mean, how it relates to pain, and what the guidelines recommend.
Related Conditions
Conditions I commonly see alongside, or confused with, this one.
Getting back to it
Physiotherapy for PCL injuries, built around the activity you want back.
