
Ankle Sprains
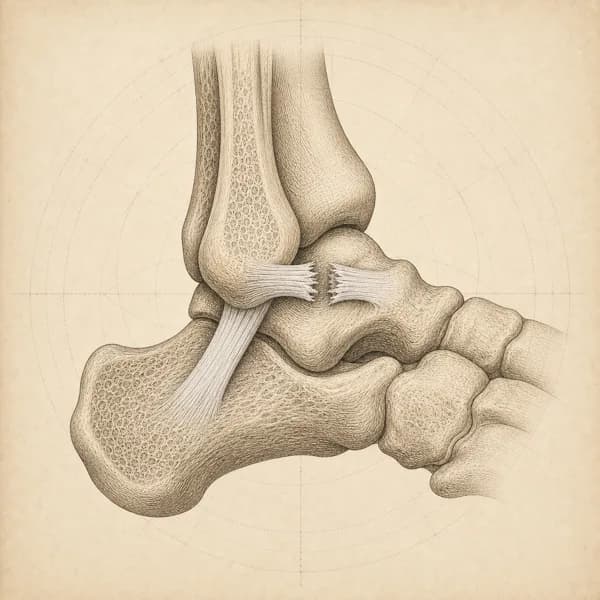
An ankle sprain is a stretch or tear of the ligaments that steady the ankle, most often on the outside when the foot rolls inward. It causes pain, swelling and bruising and can make walking hard at first. Some people are left with an ankle that keeps giving way, called chronic ankle instability, which this page also covers.
Key points
- What usually helps
- Early movement and exercise built up gradually, rather than a cast or boot for most sprains.
- What you can do now
- Keep walking on it, within comfort. Wrap it, raise it, use brief cold packs.
- How long it takes
- Mild: 1 to 3 weeks. Partial tear: 3 to 6 weeks. Complete tear: 6 to 12 weeks.
- When to see a doctor first
- Some signs need emergency care. Check the list before you start treatment.
Symptoms
Does this sound like you?
- Pain on the outside of the ankle when you stand or walk on it
- Immediate swelling and bruising after injury
- Difficulty bearing weight or walking
- Feeling of ankle instability or giving way
- Tenderness when the ligaments on the outside of the ankle are pressed (the ATFL and CFL)
Often alongside it
- Stiffness in the morning, and an ankle that does not move as far as usual
- Pain in the knee, hip or other ankle from moving differently to protect the injured one
- Fear of re-injury affecting confidence
- Doing less activity and sport than before
- Balance difficulties on uneven surfaces
- Feeling of ankle weakness during activities
- Recurrent minor ankle turns or near-sprains
It starts with a clear moment when the foot rolls inward, followed straight away by pain and swelling. The first symptoms improve within days to weeks. Without proper rehabilitation, though, the ankle can stay unstable and the risk of another sprain remains high. Many people have episodes of the ankle 'giving way' during daily activities.Book an assessment for ankle sprains
When to see a doctor first
Go to emergency
A cold, pale, or blue foot, or numbness that does not settle
Go to emergency now
Get seen today
Either of these after the injury: you could not take 4 steps (even limping) straight afterwards and still cannot, or you are tender on the back edge or tip of either ankle bone, the base of the fifth toe bone, or the bone on the inner midfoot
Get assessed the same day at urgent care or by your family doctor for an X-ray (Ottawa ankle rules) before loading the ankle. Either sign on its own is enough
Calf swelling, warmth, or tenderness in the days or weeks after the injury, especially after time in a boot or on crutches
Same-day medical assessment to rule out a blood clot (DVT)
A pop at the back of the ankle and difficulty pushing off
Same-day medical assessment for a possible Achilles tendon rupture
Check with your doctor
Deep ankle pain, catching, or locking that persists beyond 6 to 8 weeks
I flag it to your family doctor, who can arrange imaging to check the cartilage and tendons
Treatment
How it is treated
Main approach. For most sprains, current guidelines favour early movement and exercise that builds up gradually over keeping the ankle still in a cast or boot (immobilization). The evidence supports a faster return to activity this way.
Alongside it. Balance training, including work on your sense of where the ankle is (proprioception), combined with strengthening can reduce the risk of spraining it again. It also targets the balance and control changes linked to an ankle that keeps giving way (chronic ankle instability).
Managing it over time. Structured balance and coordination programs (neuromuscular training) that include balance work, hopping and jumping drills (plyometrics) and movements from your sport can help reduce repeat sprains in people at higher risk. The evidence that they prevent a first sprain is more limited.
A typical rehabilitation progression
Three phases, from settling symptoms to returning to full activity.
Recovery from ankle sprains is usually staged: calm the symptoms first, then rebuild the strength and capacity of the area, then return to your full activities. The phases below show how that can progress.
Phase 1Early Protection and Gentle Loading (First 7 to 14 Days)
Protect the ankle at first, then get back to standing and walking on it with support, and to gentle movement, as the injury allows. Compression and raising the leg (elevation) may help swelling, and brief, wrapped cold packs can be used for comfort alongside exercise. Ask a doctor or pharmacist whether pain medication is suitable for you. The 2021 clinical guideline for ankle sprains (Martin et al., 2021) supports early movement and exercise, with a brace or tape for a short time if needed. A severe sprain may need a short period of greater protection before this phase.
Example exercises
- Putting weight on the ankle as far as pain allows, using crutches only if you are limping because of pain, and coming off them as soon as you can walk normally, heel to toe
- Ankle pumps (pointing the foot up and down) and tracing the alphabet with your toes, moving in every direction, to prevent stiffness and keep the ankle moving smoothly
- Calf stretches with a towel around the foot, and seated stretches bringing the foot up toward the shin (), within a pain-free range, to get back the up-and-down movement of the ankle
- Pushing the foot outward and inward against a wall or something solid without moving it ( and ), to switch on the muscles on the outside of the lower leg (peroneals) and the deep muscles that turn the foot in, without irritating the healing ligament
- A compression wrap or ankle sleeve to help with swelling, and advice on raising the ankle when you sleep
Possible progression milestones
Walking without pain or a limp, the foot bending up toward the shin (dorsiflexion) to within about 5 degrees of the uninjured side, swelling going down day by day, and a heel raise on both feet without sharp pain.
Phase 2Building Up Load, Balance and Strength (Weeks 2 to 6)
Build up load, confidence and exercise as the ankle allows. This phase targets the balance and strength changes linked to an ankle that keeps giving way (chronic ankle ). Balance and coordination training (neuromuscular training) has consistent support for reducing repeat sprains (Martin and colleagues' 2021 guideline; Doherty and colleagues, 2017).
Example exercises
- Standing on one leg, first on a firm surface and then on a wobbly one (a foam pad or BOSU), building up to eyes closed and to drills where you recover from an unexpected push or wobble (perturbation drills)
- Turning the foot outward and inward against a resistance band (resisted eversion and inversion), adding repetitions and resistance as strength improves
- Single-leg heel raises, building from part of the way up to all the way up, 3 sets of 12 to 15 repetitions per side
- Standing on one leg and reaching the other foot forward, back and in, and back and out (Star Excursion or Y-Balance reaches), to rebuild control while moving
- Hopping in place on both feet, then on one, progressing to forward, sideways and diagonal hops once pain-free
Possible progression milestones
Possible milestones, adapted to the person rather than treated as fixed cut-offs: steady single-leg balance on a firm surface with eyes closed, single-leg heel raises close to the uninjured side, reach tests (such as the Y-Balance) close to the uninjured side, and pain-free hopping in place.
Phase 3Return to Sport and Changing Direction (Weeks 4 to 12+)
Get back to fast movements in every direction with confidence. The 2021 clinical guideline for ankle sprains (Martin et al., 2021) bases return to sport on meeting set checks rather than on time alone. Pooled evidence suggests balance and coordination programs (neuromuscular training) can reduce repeat sprains, which is why prevention work carries on into the maintenance phase rather than stopping when the pain has gone.
Example exercises
- Hopping and jumping drills () that build up step by step: from two-leg to single-leg hops, from straight-line to sideways to turning hops, and landings from a small drop (drop landings), with the quality of each landing scored
- Change-of-direction drills, starting with planned cuts at 45 degrees and progressing to 90 and 180 degree cuts, then cuts in response to a signal (reactive cutting)
- Sport-specific agility ladder, T-drill, and shuttle runs built around the specific demands of your sport
- Balance and single-leg work placed at the end of a session, when you are tired, to mimic late-game demands when re-injury rates rise
- An ongoing balance and coordination program 2 to 3 times per week, modelled on injury prevention warm-ups such as the FIFA 11+
Possible progression milestones
Possible milestones, adapted to the person rather than treated as fixed cut-offs: ankle strength in all directions close to the uninjured side, hop tests close to the other side, completing reactive cutting (changing direction in response to a signal) and sport-specific drills without feeling wary of the ankle, and no ongoing feeling of the ankle giving way (a short questionnaire such as the Cumberland Ankle Instability Tool can help track this).
What you can do now
- Keep walking on it, within comfort. For many mild and moderate sprains (grade 1 and 2), guidelines favour early, protected walking over strict rest. Use crutches only if you are limping because of pain, and come off them once you can walk normally, heel to toe.If you could not take 4 steps straight after the injury and still cannot, or a bone is tender at one of the spots listed in the warning signs on this page, get assessed the same day at urgent care or by your family doctor for an X-ray before loading the ankle. A severe sprain may need a short period in a brace or boot first.
- Wrap it, raise it, use brief cold packs. A compression wrap or ankle sleeve and raising the ankle, including when you sleep, may help the swelling. Brief cold packs can ease pain alongside your exercises, and a doctor or pharmacist can tell you whether pain medication is suitable for you.Wrap cold packs in a cloth and keep each use brief. Calf swelling, warmth or tenderness in the days or weeks after the injury, especially after time in a boot or on crutches, needs a same-day medical assessment to rule out a blood clot.
- Move the ankle gently every day. Ankle pumps (pointing the foot up and down), tracing the alphabet with your toes and a calf stretch with a towel around the foot help prevent stiffness while the ligament heals. Keep each one within a pain-free range.
- Add balance work once the limp goes. Stand on the injured leg on a firm floor, then build up to doing it with your eyes closed. This rebuilds balance and your sense of where the ankle is (proprioception), which a sprain can disturb.Move on to a wobbly surface only once standing on one leg on a firm floor feels steady.
- Keep going after the pain settles. Feeling normal is not the same as being fully rehabilitated, and another sprain is common when people stop at that point. Keep up your balance and strength work, and base your return to sport on checks such as pain-free hopping and steady single-leg balance rather than on time alone.Deep ankle pain, catching or locking that lasts beyond 6 to 8 weeks is a reason to get it checked; I flag it to your family doctor, who can arrange imaging.
What I use in clinic
- Balance training. In high-quality trials, balance training is linked with a meaningful drop in the risk of spraining the ankle again.
- Early movement and loading. For most sprains, current guidelines favour early movement and exercise over keeping the ankle still in a cast or rigid boot (immobilization) (Vuurberg et al., 2018).
Recovery
How long it takes
Recovery of everyday function depends on the grade: grade 1 (a mild stretch) 1 to 3 weeks, grade 2 (a partial tear) 3 to 6 weeks, and grade 3 (a complete tear) 6 to 12 weeks. The ligament keeps rebuilding (remodelling) for 6 to 12 months, a period when the risk of another sprain is higher.
In a study that followed people forward from a first-time sprain, about 40 percent had an ankle that kept giving way (chronic ankle instability) a year later (Doherty et al., 2016). Rehabilitation that includes balance and coordination training can lower the risk of another sprain. A small number who still have an unstable ankle despite good rehabilitation are referred for a surgical opinion.
What changes the timeline
- How severe the first injury was, and whether the joint has been left loose (mechanical instability)
- Age, body weight (BMI) and any earlier ankle sprains
- How much it hurts early on: more pain at 3 to 4 weeks predicts a longer recovery
- Fear of moving the ankle, and how you are coping with the injury emotionally
- How consistently you do the rehab early on, and when you return to activity
How I track it. I track how much the pain gets in the way of the tasks that matter to you, how well you move when I test those tasks in clinic, and how confident you feel in daily activities
Similar conditions
Conditions that can feel similar
- Syndesmotic (High Ankle) Sprain
- Pain sits higher, just above the ankle joint, over the ligaments that bind the two shin bones together (the tibiofibular ligaments). It often follows the foot being twisted outward or forced up toward the shin. Squeezing the two shin bones together partway up the leg, or turning the foot outward, brings on the pain (squeeze and external rotation stress tests). Return to sport takes longer, typically 2 to 3 times longer than an ordinary outer ankle sprain. It is often missed at first and benefits from being picked up early.
- Peroneal Tendon Injury (Tear or Subluxation)
- Pain sits behind the outer ankle bone, along the peroneal tendons, rather than over the ligament at the front of the ankle (the ATFL). Turning the foot outward can bring pain or a snapping feeling, and sometimes the tendons can be felt slipping out of place behind the outer ankle bone (the lateral malleolus). It often develops after an outer ankle sprain that was not rehabilitated.
- Isolated ATFL vs Combined ATFL plus CFL Sprain
- When only the front ligament (ATFL) is hurt, the ankle slides forward more than normal when the heel is drawn forward (anterior drawer test), but it does not tip inward too far when tilted (talar tilt test). When the lower ligament (CFL) is hurt as well, the ankle both slides forward too far and tips inward further than normal. These combined sprains tend to bruise and swell more, and take longer to recover.
- Osteochondral Lesion of the Talus
- Deep ankle pain that lasts longer than a sprain should, often with catching, clicking or locking inside the joint. Bouncing on the heel may bring on the pain (bounce test), as may bending the ankle up toward the shin with weight on it. It is worth suspecting if pain and swelling inside the joint (effusion) last beyond 6 to 8 weeks despite appropriate rehabilitation.
- 5th Metatarsal Fracture (Avulsion or Jones)
- The bone is tender at the base of the long bone on the outer edge of the foot (the 5th metatarsal), and you may not be able to put weight on the foot. Both are checks in the Ottawa Foot Rules, which decide whether an X-ray is needed. A Jones fracture of this bone is known for healing poorly and needs a medical referral. A small piece of bone can also be pulled off the base of the 5th metatarsal (an avulsion fracture) by the same rolling-in movement that causes a sprain.
- Fibular Avulsion Fracture
- The bone is tender at the lower end of the outer leg bone (the fibula), especially the tip of the outer ankle bone, after the foot rolls inward. The Ottawa Ankle Rules flag who needs an X-ray, and a plain X-ray shows it. It is often managed much like a grade 2 or 3 sprain, but the X-ray needs to confirm it before heavy loading starts.
- Posterior Tibial Tendon Dysfunction
- Pain on the inner side of the ankle and foot, an arch that gradually flattens, and trouble rising onto your toes on one leg (single-leg heel raise). It usually builds from gradual overload rather than a sudden roll of the ankle, but an outer ankle sprain that changes how the foot moves can bring it to light or make it worse.
Questions
What patients ask me most
Is it a sprain or a fracture?
The Ottawa Ankle Rules are the standard screening tool to decide if X-rays are needed. An X-ray is warranted if the bone is tender along the back edge or tip of either ankle bone (the malleoli), if it is tender at the navicular (a bone on the inner midfoot) or at the base of the 5th metatarsal (the outer edge of the foot), or if you could not take 4 steps on it both straight after the injury and in the clinic. The rules pick up close to 100 percent of clinically significant fractures (their sensitivity). If any of those criteria are present, I send you to urgent care or your family doctor for an X-ray before loading the ankle.
Should I keep walking on a sprained ankle?
For many grade 1 and grade 2 outer ankle sprains, yes, within pain tolerance. Educational frameworks such as PEACE and LOVE (Dubois and Esculier, BJSM 2020) emphasise early protected loading rather than strict rest, and current guidelines favour early protected weight bearing and gradual loading over prolonged immobilization for most sprains (Vuurberg et al., 2018; Martin et al., JOSPT 2021). Brief, wrapped cold packs can still be used for comfort alongside exercise. A severe sprain may need a short period of greater protection in a brace or boot first. If you cannot bear weight at all or a fracture is suspected, that is different and needs screening first.
How long does a sprained ankle take to heal?
Grade 1 sprains typically recover in 1 to 3 weeks, grade 2 in 3 to 6 weeks, and grade 3 in 6 to 12 weeks for baseline function. Tissue remodelling continues for 6 to 12 months. More severe initial injury and higher pain levels have been associated with slower recovery, and ongoing pain when the ankle bends up toward the shin with weight on it, along with restricted ankle movement, are reasons I monitor recovery closely (Thompson et al., BMC Musculoskelet Disord 2017). Feeling normal is not the same as being fully rehabilitated, which is why reinjury is common when people stop at symptom resolution.
Why does my ankle still feel weak months after I sprained it?
Roughly 40 percent of people who sustain a first-time outer ankle sprain go on to develop chronic ankle instability at 12 month follow-up (Doherty et al., AJSM 2016). This is not just ligament laxity. It involves damage to the position sensors in the ligaments (mechanoreceptors), slower timing in the muscles on the outside of the ankle (the peroneals), and changes in how the hip and trunk move to make up for it. What often helps is targeted balance and coordination training (neuromuscular training), strength work for the peroneals and hip, and progressive loading of sport-specific tasks, not more rest.
Do I need an MRI for a sprained ankle?
Usually no. Most outer ankle sprains are diagnosed from the examination and do not require MRI. I flag it to your family doctor or specialist and refer you for imaging when symptoms are not improving as expected at 6 to 8 weeks, when there is suspicion of a high ankle (syndesmotic) injury, damage to the cartilage and bone surface inside the ankle joint (an osteochondral lesion of the talus), a peroneal tendon tear, or when mechanical symptoms like locking or catching persist. X-rays per Ottawa Ankle Rules are the appropriate first imaging step if indicated acutely.
When can I return to sport after an ankle sprain?
Return to sport is based on criteria rather than time alone, in line with the JOSPT clinical practice guideline (Martin et al., 2021). Possible milestones, adapted to the person rather than treated as fixed cut-offs: pain-free hopping and cutting, single-leg balance and reach tests close to the other side, ankle strength close to the uninjured side, and completing progressive agility and sport-specific drills without apprehension. Depending on grade, this is often 2 to 8 weeks for simple sprains and longer for grade 3 or high ankle sprains.
The science
The Science of Ankle Sprains
Ankle sprains involve stretching or tearing of ligaments, usually the lateral ligaments (ATFL, CFL). This damages mechanoreceptors, affecting . The condition represents a complex injury that affects both structural integrity and neurological function.
Lateral ankle sprains occur when the foot rolls inward (), placing excessive stress on the outer ankle ligaments. The anterior talofibular ligament (ATFL) is typically injured first, followed by the calcaneofibular ligament (CFL) in more severe cases. The injury disrupts the mechanoreceptors within the ligament tissue, which normally provide critical position and movement feedback to the brain.
In a prospective study of people with a first-time sprain, about 40 percent had developed chronic ankle (CAI) a year later (Doherty et al., 2016), characterized by persistent symptoms of pain, swelling, perceived instability, and recurrent sprains for at least one year after the initial injury. This progression is not simply due to structural damage but involves complex changes in neuromuscular control and movement patterns throughout the entire lower extremity.
Contributing factors
Most ankle sprains happen when your foot lands in an position (turned inward) with your body weight shifted over the outside edge of your ankle. This classic mechanism occurs because your lateral ankle ligaments are much weaker than the medial ones, making them vulnerable when your center of gravity moves over the lateral border of your foot. The dangerous moment happens when your foot makes contact with the ground while inverted, because there is not enough time for your muscles to react and correct the position.
Poor landing mechanics significantly increase your risk. When you land on an unstable surface or with poor body control, your foot may contact the ground in excessive inversion before your peroneal muscles can fire to correct it. Your peroneal muscles normally act as a protective mechanism, but a sprain can happen faster than they can respond to a sudden roll.
Previous ankle sprains create a vicious cycle of . The initial injury damages the mechanoreceptors in your ligaments that provide balance and position feedback to your brain. Without this proprioceptive input, you're much more likely to land awkwardly or lose balance, leading to repeat sprains. This is why people often say their ankle "gives out" or feels weak. Strength is part of it, but balance control and position sense from the damaged ligament receptors matter just as much.
With chronic ankle instability, the entire lower limb adapts through compensatory strategies. You develop reduced and delayed activation of the peroneal muscles, maintaining a more inverted foot position during activities. The knee becomes stiffer to compensate for ankle instability, while the hip adopts more flexion and altered control patterns. These adaptations increase your risk of other injuries, including tears and hip problems.
Research
What the studies show
The 2021 American Physical Therapy Association guideline for ankle sprains
Recommends a brace or tape early on, with gradually more weight through the ankle, rather than keeping it still for a long time, followed by structured exercise and balance training. Bracing and balance training lower the risk of spraining the ankle again. To prevent a first sprain, the guideline recommends bracing, particularly for people with risk factors; evidence that balance training helps prevent a first sprain is limited, although clinicians may consider it.
Sets out a framework for ankle sprain rehabilitation built on early movement and exercise, with balance training as a core part.
Martin RL, Davenport TE, Fraser JJ, et al. Ankle Stability and Movement Coordination Impairments: Lateral Ankle Ligament Sprains Revision 2021. J Orthop Sports Phys Ther. 2021;51(4):CPG1-CPG80. PMID: 33789434.
Diagnosis, treatment and prevention of ankle sprains: update of an evidence-based clinical guideline
Treatment that gets the ankle moving and working early can support a faster return to work and activity than keeping it still, and supervised exercise can help reduce the risk of repeat sprains. Balance and coordination training (neuromuscular and proprioceptive training) is recommended during rehabilitation.
Provides a guideline that favours early movement and supervised exercise over keeping the ankle still for a long time after a recent sprain on the outside of the ankle.
Vuurberg G, Hoorntje A, Wink LM, et al. Diagnosis, treatment and prevention of ankle sprains: update of an evidence-based clinical guideline. Br J Sports Med. 2018;52(15):956. PMID: 29514819.
Related Conditions
Conditions I commonly see alongside, or confused with, this one.
Achilles Tendinopathy / Tendinitis
Ankle instability affects Achilles tendon mechanics and loading patterns
Shin Splints
Ankle instability can alter lower leg mechanics contributing to shin splints
Turf Toe
Both are ligament sprains from sport with the same graded return to running and cutting
Growth Plate Injuries
In children the same twisting injury often affects the growth plate rather than the ligament
IT Band Syndrome
Ankle dysfunction affects entire lower limb chain including IT band stress
Getting back to it
Physiotherapy for ankle sprains, built around the activity you want back.
