
Degenerative Disc Disease
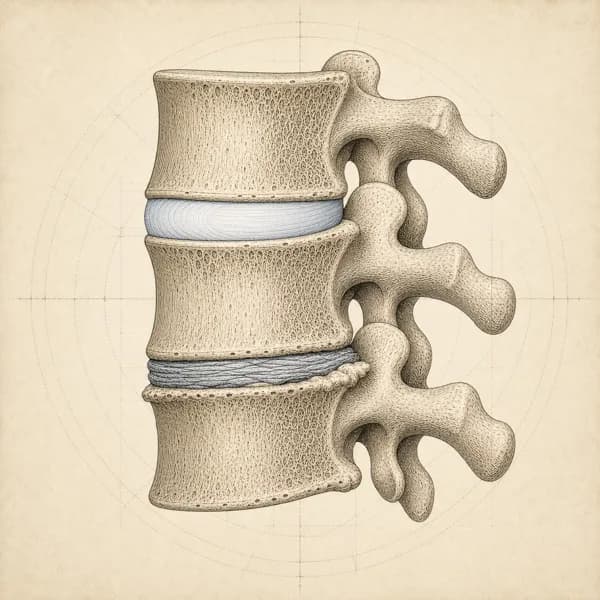
Degenerative disc disease is a label for changes in spinal discs, such as loss of water and height, that become more common with age. They also appear on scans of people without pain. A scan alone cannot establish the cause of symptoms, so it is considered alongside your history and examination.
Key points
- What usually helps
- Exercise, with clear information about what disc changes on a scan mean.
- What you can do now
- Walk little and often. Break up long sitting.
- How long it takes
- Flare-ups usually settle within 2 to 6 weeks; learning to manage it usually takes 3 to 6 months.
- When to see a doctor first
- Some signs need emergency care. Check the list before you start treatment.
Symptoms
Does this sound like you?
- Variable pain that can range from mild aching to severe episodes
- Pain that worsens with long sitting or bending forward
- Stiffness and less movement, especially in the morning
- Pain relief with walking or changing positions
- Flare-ups that come and go and may last days to weeks
Often alongside it
- Pain that spreads into the buttocks or thighs, without nerve symptoms down the leg
- Muscle spasms in the back
- A feeling that the back is unstable or weak
- Difficulty finding comfortable sleeping positions
- Tiredness from moving differently to protect the back
I often see patients who describe good days and bad days with their symptoms. The pain may be minimal for weeks, then flare significantly with activities like prolonged sitting, lifting, or even something as simple as a sneeze. Many tell me their pain is worse in the morning until they 'get moving' and often improves with walking.Book an assessment for degenerative disc disease
When to see a doctor first
Go to emergency
New trouble starting to pass urine or feeling it pass, new loss of bladder or bowel control, new numbness between the legs or around the back passage, new loss of genital sensation or sexual function, or severe or rapidly worsening weakness in both legs
Go to emergency now. These can be signs of cauda equina syndrome
Sudden unexplained weakness or numbness in an arm or leg, even if it improves
Call 911 now. This can be a stroke. Do not wait for a physiotherapy appointment
Get seen today
Pain that suddenly starts down both legs, or spreads from one leg to both, even without the signs above
Contact a medical clinician today for a same-day assessment
A new foot drop (the foot catches or slaps when you walk), or new or worsening weakness in one leg
Same-day medical assessment
Fever or feeling generally unwell with back pain
Same-day medical assessment
Back pain after a fall, or after a minor strain if you have osteoporosis or take long-term steroids
Same-day medical assessment to rule out a fracture
Check with your doctor
Leg pain below the knee that keeps spreading or getting worse
See your family doctor. I flag it and refer you when imaging would change the plan
Constant, severe pain that does not ease with rest or position, a history of cancer, or unexplained weight loss
See your family doctor before starting physiotherapy
Treatment
How it is treated
Main approach. Exercise combined with clear information about what disc changes mean can help reduce pain and improve function, and no single type of exercise has been shown to be best.
Alongside it. Hands-on treatment and short-term changes to activity may ease a flare while you keep moving.
Managing it over time. Keeping up regular exercise after a flare settles may lower the chance of another episode of back pain.
A typical rehabilitation progression
Three phases, from settling symptoms to returning to full activity.
Recovery from degenerative disc disease is usually staged: calm the symptoms first, then rebuild the strength and capacity of the area, then return to your full activities. The phases below show how that can progress.
Phase 1Calming Symptoms and Building Confidence in Movement
Make the back less sensitive, get basic movement comfortable again, and explain what the disc disease label does and does not mean. Education, and getting back into movement step by step, are consistently recommended first steps in the 2021 physiotherapy clinical guideline for low back pain (George and colleagues), the American College of Physicians guideline (Qaseem and colleagues, 2017) and the NICE guideline (NG59).
Example exercises
- Cat-cow (slowly rounding and arching your back on hands and knees) and pelvic tilts, 10 slow repetitions, as a morning routine to get moving
- Supported child's pose (kneeling and sitting back towards your heels with your arms reaching forward) or lying propped on your elbows, 2 to 3 minutes, guided by comfort
- Short, frequent walking bouts of 10 to 15 minutes rather than one long walk
- Slow belly breathing (diaphragmatic breathing) and a simple plan to pace your day and break up long sitting
- A plain-language explanation of your scan findings and what degenerative disc disease is and is not
Possible progression milestones
Pain at rest at 2 out of 10 or lower, daily walking reaching 20 to 30 minutes comfortably, and being able to name one or two activities you are doing more of rather than less.
Phase 2Building Trunk and Hip Strength
Rebuild strength and tolerance in the trunk, hips and legs so the back handles daily and work loads without repeated flare-ups. Strengthening exercises and load built up step by step are supported as a first treatment across the major low back pain guidelines.
Example exercises
- Bird dog (on hands and knees, reaching out the opposite arm and leg) and dead bug (on your back, lowering the opposite arm and leg), 2 to 3 sets of 8 to 10 per side, keeping your back steady in its natural middle position
- Glute bridges progressing to single-leg bridges, 2 to 3 sets of 10
- Goblet squat to a box (holding a weight at your chest), 3 sets of 8 to 10, with depth guided by how your symptoms respond
- Practising the hip hinge (bending forward from the hips with a flat back), from a broomstick to a kettlebell deadlift, progressed by adding weight
- Side plank and suitcase carry (walking with a weight in one hand) to train the trunk to resist bending sideways and twisting
Possible progression milestones
A full workday without a meaningful flare-up, hip hinging and squatting at comfortable training weights, and flare-ups, when they happen, settling within days rather than weeks.
Phase 3Returning to Full Activity and Managing It Long Term
Match training to the real demands of your life, whether that is gardening, heavy lifting at work, running or recreational sport. The aim is a back that holds up over time and a realistic plan for managing it yourself, since the disc changes do not go away on scans.
Example exercises
- Trap-bar or conventional deadlift, built up gradually from light weights, 3 to 4 sets of 5
- Squats with the weight held in front (front-loaded squats) or split squats, at your training weights, matched to your goals
- Farmer and suitcase carries (walking with a weight in both hands, or in one hand) for trunk and grip, 3 to 4 rounds of 30 to 40 metres
- Return to running or sport built up step by step, starting with walk-run intervals
- A maintenance routine two to three days a week that you can keep up on your own
Possible progression milestones
Managing full work, home and leisure demands with minimal symptoms, confidence handling flare-ups yourself, and a simple written plan of your own.
What you can do now
- Walk little and often. Walking often eases this kind of back pain. Try short, frequent walks of 10 to 15 minutes rather than one long walk.Leg pain below the knee that keeps spreading or getting worse needs a visit to your family doctor.
- Break up long sitting. Long sitting and bending forward often make the pain worse, and changing position often eases it. Plan regular breaks and vary how you sit, stand and move, which helps prevent stiffness.
- Start the day with a gentle back routine. Pain is often worse in the morning until you get moving. Cat-cow (slowly rounding and arching your back on hands and knees) and pelvic tilts, 10 slow repetitions, make a simple morning routine.
- Ease back during a flare, then rebuild. Flare-ups are common and do not mean damage. During one, pull back for a short time on heavy lifting and lifting from a deep bend, then build back up step by step rather than giving up lifting or running.A foot that catches or slaps when you walk, new or worsening weakness in one leg, or pain that spreads to both legs needs a same-day medical assessment. Signs such as new trouble passing urine, loss of bladder or bowel control, or numbness between the legs or around the back passage mean go to emergency now, as the warning signs on this page explain.
- Notice what sets off your flares. Long sitting, lifting, even a sneeze, as well as physical or emotional stress, can set off a flare, and sleep quality affects pain sensitivity. Knowing your own triggers helps you plan your day around them.If stress feels overwhelming, consider professional support.
What I use in clinic
- Spinal stabilization exercise. Exercises for the deep muscles that support the spine. Evidence supports them for improving movement control and reducing pain.
- Hands-on treatment with exercise. Moderate evidence supports gentle hands-on movement of the spinal joints (spinal mobilization) combined with exercise, as part of a non-surgical plan.
- Cognitive functional approach. Work on beliefs about the spine and pain, combined with relearning how to move, reduced disability more than usual care in a large trial.
Recovery
How long it takes
Flare-ups usually settle within 2 to 6 weeks. Learning to manage the condition well usually takes 3 to 6 months.
Age-related disc changes are common in people with and without back pain, and a scan finding alone cannot tell whether it explains your symptoms. With appropriate management, function can be maintained despite these changes.
What changes the timeline
- Understanding that disc degeneration is not dangerous improves recovery
- Staying active helps you avoid losing fitness (deconditioning) and keeps you functioning
- Previous episodes may mean a longer recovery, but do not mean the spine is getting worse
- Overall health and fitness level influence recovery
- Fear of moving, and avoiding activity because of it (fear-avoidance), affects recovery
How I track it. I track what you can do in daily activities, how often flares come and how strong they are, and how confident you feel managing them
Similar conditions
Conditions that can feel similar
- Mechanical Low Back Pain (Non-Specific)
- The more common name for the same picture. Most backs labelled DDD on a scan behave like ordinary low back pain: the pain varies, changes with movement, has no leg symptoms, and checks of the nerves are normal. Treatment is essentially the same, which is why the DDD label often adds fear without changing the plan.
- Lumbar Radiculopathy
- Leg pain that follows the path of one nerve, brought on by lifting the straight leg or by sitting slumped and straightening the knee (straight leg raise or slump test), often with weakness in particular muscles or a changed reflex. If the leg truly hurts more than the back, the likely diagnosis shifts from DDD toward a disc irritating a nerve root (radiculopathy).
- Facet Joint Pain
- Pain beside the spine that is worse leaning back and twisting and better bending forward, often pointed to with one or two fingers just to the side of the spine. It may spread to the buttock or back of the thigh but rarely past the knee, and checks of the nerves are normal.
- Spinal Stenosis
- Pain or heaviness mainly in the legs that builds with walking and standing and eases with sitting or leaning forward (neurogenic claudication). More common in people over 60. Standing upright drives the symptoms, rather than the bending forward that typically aggravates DDD.
- Sacroiliac Joint Pain
- One-sided pain near the bony bump at the back of the pelvis (the PSIS), brought on by a group of tests that press on or stretch the joint (distraction, compression, thigh thrust, FABER and Gaenslen tests). Pain rarely spreads below the knee and does not follow the path of one nerve.
- Vertebral Compression Fracture
- Pain in one spot, often sore to press, after a fairly minor fall or strain, or coming on gradually in people at risk of osteoporosis or on long-term steroid medicine (corticosteroids). Sharp pain with straining or bearing down, standing up from sitting, or sneezing. This needs a doctor and a scan, not a DDD plan.
Questions
What patients ask me most
What does 'degenerative disc disease' actually mean?
It is a descriptive imaging label, not a disease in the usual sense. It describes age-related changes in the discs such as loss of height, reduced water content, and small changes in the disc's tough outer ring (the annulus). Brinjikji et al. (AJNR 2015) found disc degeneration in 37% of completely pain-free 20-year-olds and 96% of pain-free 80-year-olds. The finding is so common in healthy people that it is closer to a description of the spine getting older than a diagnosis that explains symptoms on its own.
My MRI looks scary. How worried should I be?
Usually much less worried than the report sounds. Terms like 'disc desiccation,' 'mild bulging,' 'facet arthropathy,' and 'degenerative changes' show up on the scans of many people with zero back pain. Jensen et al. (NEJM 1994) found disc bulges in 52% and protrusions in 27% of pain-free adults. I pay close attention to warning signs and to the match between the scan and your actual symptoms, not to scary sounding words in isolation.
Will this get worse over time?
Disc imaging findings generally accumulate with age, but symptoms do not reliably follow the same curve. Plenty of people develop more imaging findings over the years without getting worse, and some feel better as flares become less frequent with conditioning. Worsening pain is not inevitable, and it is not a foregone conclusion that DDD seen in your 40s means disability in your 60s.
Is there a cure for DDD?
Age-related disc changes usually remain visible on scans, and no treatment reverses them. Treatment instead focuses on helping you move more comfortably, have fewer and shorter flares, and do the activities that matter to you. Exercise, strength work, education and sensible load management are how I work on that, and the ACP (Qaseem and colleagues, 2017) and NICE NG59 guidelines both recommend active, non-drug care first.
Should I stop lifting weights or running?
Usually not. Strength training and running can be good long-term investments for a back with DDD, provided load and progression are managed. Stopping them can lead to a loss of fitness (deconditioning), which can make flares more frequent rather than less. During a flare I temporarily pull back on heavy or deeply bent loading, then rebuild step by step.
Do I need surgery for degenerative disc disease?
Very rarely. NICE NG59 explicitly recommends against spinal fusion for low back pain outside of a trial and against disc replacement for low back pain. Surgery can have a role in nerve root pain (radiculopathy) or stenosis that has not responded to thorough non-surgical care, but DDD alone is not typically a surgical problem.
Will a back brace or corset help?
Not meaningfully for DDD. NICE NG59 recommends against belts and corsets, foot orthotics, and rocker sole shoes for low back pain. They can feel reassuring short term, but they do not build the capacity that actually reduces flares.
When should I worry about back pain with DDD?
Go to emergency now for new trouble starting to pass urine or feeling it pass, new loss of bladder or bowel control, new numbness between the legs or around the back passage, or severe or rapidly worsening weakness in both legs. New loss of genital sensation or sexual function with back or leg pain also needs emergency assessment. These can be signs of cauda equina syndrome. Contact a medical clinician today if pain suddenly starts down both legs or spreads from one leg to both, even without those signs. A new foot drop (the foot catches or slaps when you walk), worsening weakness in one leg, or fever with back pain needs a same-day medical assessment. Sudden unexplained weakness or numbness in an arm or leg, even if it improves, can be a stroke: call 911 now. Unexplained weight loss or severe, unrelenting night pain need a doctor's assessment before physiotherapy. None of these are typical DDD patterns.
The science
The Science of Degenerative Disc Disease
disc disease represents the natural aging process of your intervertebral discs, though it can occur prematurely due to various factors. Your discs are composed of an outer fibrous ring () and an inner gel-like core () that normally acts as a shock absorber between vertebrae.
As discs age, they lose water content and the nucleus pulposus becomes less gel-like, reducing the disc's ability to distribute loads evenly. This dehydration process leads to decreased disc height and can result in small tears in the annulus fibrosus. When the disc loses height, it alters the of the entire spinal segment.
The , which normally share load with the discs, begin to bear a greater proportion of the forces passing through that level of the spine. This can lead to accelerated wear of these joints and may contribute to the development of and other arthritic changes. Despite the name, degenerative disc disease isn't truly a disease but rather a description of the structural changes that occur over time.
It's important to understand that these structural changes don't always predict pain levels. Many people have significant disc degeneration visible on imaging scans but experience no symptoms whatsoever. Conversely, some individuals with minimal structural changes may have considerable pain. This disconnect between imaging findings and symptoms highlights why treatment focuses on function and symptoms rather than structural abnormalities.
Contributing factors
Your spine functions as an integrated system where each level works with adjacent levels to allow movement while maintaining stability. When disc occurs, this system becomes altered in ways that can contribute to symptoms.
The disc and two at each level form what is called the three-joint complex. Normally, the disc carries most of the compressive load, while the facet joints guide movement and limit rotation. When disc height decreases, the facet joints take a larger share of the load.
This increased load on the facet joints can lead to inflammation and pain. Additionally, loss of disc height can narrow the spaces where exit the spine, potentially causing nerve-related symptoms. The supporting muscles often respond to these changes by increasing tension to provide additional stability, which can contribute to muscle-related pain and stiffness.
Research
What the studies show
Exercise probably reduces pain in long-lasting low back pain
A 2021 Cochrane review of 249 trials found that exercise probably reduces pain in long-lasting (chronic) low back pain compared with no treatment, usual care or a placebo, with a smaller effect on function and no single best type of exercise. The evidence is moderately certain.
The trials covered long-lasting low back pain in general, not age-related disc changes alone. Most people with this scan label belong to that wider group.
Hayden JA, Ellis J, Ogilvie R, et al. Exercise therapy for chronic low back pain. Cochrane Database Syst Rev. 2021;9(9):CD009790. PMID: 34580864.
The McKenzie method may reduce pain and disability when one direction of movement eases back pain
A 2025 review of five trials (743 people) with long-lasting low back pain that eased with one direction of movement (a directional preference) found that the McKenzie method reduced pain in the short term, and disability in the medium term, more than other treatments grouped together. The certainty of the evidence is low, and differences compared with hands-on treatment (manual therapy) were small.
When a particular direction of movement eases the pain, exercises in that direction can help. The certainty of the evidence is low, so I use it as one option rather than a rule.
Hennemann V, Ziegelmann PK, Marcolino MAZ, et al. The McKenzie Method delivered by credentialed therapists for chronic low back pain with directional preference: systematic review with meta-analysis. J Man Manip Ther. 2025;33(2):96-111. PMID: 39383118.
Related Conditions
Conditions I commonly see alongside, or confused with, this one.
Getting back to it
Physiotherapy for degenerative disc disease, built around the activity you want back.
