Shoulder Instability and Dislocation
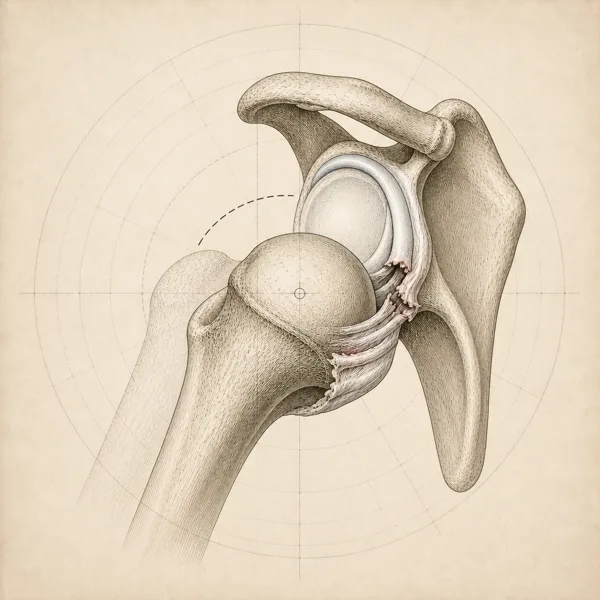
Shoulder instability means the ball of the shoulder slips partly or fully out of its socket, or feels as if it might. It can follow a dislocation or develop gradually without a clear injury. This page covers these different patterns and rehabilitation after stabilisation surgery, which follows the surgical team's restrictions.
Does this sound like you?
- Sensation of the shoulder 'giving way' or feeling loose during activities
- Worry or fear in overhead movements or certain positions
- Episodes where the shoulder partly slips out (subluxation) or fully dislocates
- Pain that is often activity-related rather than constant
- Difficulty with overhead activities, throwing, or swimming motions
Often alongside it
- Muscle fatigue in the shoulder region during activities
- Clicking, popping, or grinding sensations with movement
- Weakness turning the arm outward or lifting it out to the side
- Moving differently elsewhere in the body to protect the shoulder
- Poor sleep when lying on the affected side
I typically see two distinct patterns: young athletes whose shoulder keeps dislocating after an injury, and people whose shoulder became loose without an injury (atraumatic instability), who describe looseness and a worry that it will slip, building gradually. You may find yourself avoiding certain positions or activities because the shoulder feels like it might pop out.Book an assessment for shoulder instability and dislocationNextSee a doctor first
When to see a doctor first
The arm or hand changes colour, or there is no pulse at the wrist
Go to emergency now. This can be an injury to a blood vessel
A shoulder that is still out of place, or a first dislocation that has not been X-rayed
Go to emergency now for the shoulder to be put back and imaged to rule out a fracture
A hot, red, swollen shoulder, or fever after an injury or surgery
Go to emergency now. This can be an infection
Numbness over the outer upper arm, weakness, or a heavy, dead arm after a dislocation
Same-day medical assessment. This can be a nerve injury
How it is treated
Structured exercise programs can improve pain, function and the sense of stability for many people whose shoulder became loose without an injury (atraumatic instability). After a first dislocation caused by an injury in a young athlete, an early surgical opinion is often worthwhile.
Exercises for your sense of where the arm is (position sense) and for shoulder blade control can help, while the positions that bring on the feeling of slipping are avoided early on.
Keeping up shoulder strengthening and building sport-specific load gradually may lower the chance of another episode.
A typical rehabilitation progression
Recovery from shoulder instability and dislocation is usually staged: calm the symptoms first, then rebuild the strength and capacity of the area, then return to your full activities. The phases below show how that can progress.
Phase 1 · Weeks 0 to 6
Building Control in Safe Positions
Rebuild a safe base of and shoulder blade control while the joint capsule and the rim of cartilage around the socket () calm down. The Derby and Watson programs both start with loading in safe positions, avoiding the end of the range with the arm out to the side and turned outward in the early weeks. The aim is plenty of pain-free repetitions that restore control between the brain and the shoulder, not maximal load.
Example exercises
- Static holds turning the arm inward and outward ( internal and external rotation) with the arm at your side, 5 sets of 5 to 10 second holds at 50 to 70% effort
- Shoulder blade setting drills (low row, and the scapular clock: moving the shoulder blade toward points on an imagined clock face) with a mirror to check quality
- Wall push-ups with the hands fixed on the wall (closed-chain), letting the shoulder blades slide apart and back together under control
- Pendulum swings and small movements of the arm, done yourself within a pain-free range
- Advice on positions to avoid for now, usually the arm forced to turn outward while raised 90 degrees out to the side, and reaching overhead with a load
Phase 2 · Weeks 6 to 16
Strengthening Through Movement and Position Sense
Add loading through movement for the rotator cuff, the deltoid (the muscle over the outside of the shoulder) and the muscles that steady the shoulder blade, in positions that get more demanding step by step. Position-sense work, and exercises with the hand fixed on a wall or the floor (closed-chain), are central. Programs for that began without an injury, such as the Derby and Watson programs, work on shoulder blade control and coordination as well as strength.
Example exercises
- Turning the arm outward against a band, first with the elbow at your side, then with the arm raised 45 degrees out to the side, 3 sets of 10 to 12 reps
- Y, T, W and I arm lifts lying face down, for the muscles at the back of the shoulder blade
- Rhythmic stabilisation drills (holding the arm steady against quick, changing pushes) in varied arm positions, with a training partner or a wall
- Half-kneeling bottoms-up kettlebell holds and presses (the kettlebell held upside down by its handle), to challenge your sense of where the arm is
- Diagonal pulls across the body with a cable or band (the D1 and D2 patterns) as tolerance grows
Phase 3 · Months 4 to 6+
Return to Sport or High-Demand Activity
Rebuild the shoulder's ability to handle unplanned, fast and contact demands. Later rehabilitation helps prepare the shoulder for the demands you want to return to, and progression is based on how the shoulder performs, as in the Watson and Derby programs. A dislocation can still happen again after a well-completed program, particularly when the injury itself or the sport carries a higher risk, so I use your progress and goals to decide whether further rehabilitation or a surgical opinion is the right next step.
Example exercises
- Fast throw-and-catch drills (): ball slams, rebounding a ball off a wall, and medicine ball throws in positions you use in sport or daily life
- Loaded overhead work, starting with a landmine press and moving on to barbell or dumbbell overhead pressing
- Practising your sport's skills with the amount built up gradually (throwing program, swim intervals, tackling drills without contact, then with contact)
- Tasks that train quick reactions to unexpected pushes (perturbations), including work on unstable surfaces and rhythmic stabilisation drills with a partner
- A check of your confidence in the shoulder before full return to competition (after stabilisation surgery, the SIRSI questionnaire is one way to measure it)
What you can do now
- After a dislocation, get it checked firstA first dislocation needs to be put back in place, X-rayed to rule out a fracture and assessed before you start loading the shoulder. After stabilisation surgery, follow your surgeon's protocol rather than the general advice on this page.If the shoulder is still out of place, or a first dislocation has not been X-rayed, go to emergency now. Numbness over the outer upper arm, weakness, or a heavy, dead arm after a dislocation needs a same-day medical assessment, as the warning signs on this page describe.
- Avoid the positions that feel unsafeFor now, avoid the positions that bring on the feeling of slipping, usually the arm forced to turn outward while raised out to the side, and reaching overhead with a load. Avoiding them for a while gives the muscles that steady the shoulder time to get stronger.Avoid only those positions, not all activity, and bring them back gradually as your rehab progresses.
- Start with static holds at your sideEarly rehab uses static holds for the rotator cuff with the arm at your side, pressing inward and outward without moving, plus shoulder blade control drills. Phase 1 uses 5 sets of 5 to 10 second holds at 50 to 70% effort, without pain.After a recent dislocation, start these only once the shoulder has been put back, X-rayed and assessed.
- Practise control in front of a mirrorLearning to sense and control where your shoulder is can help prevent episodes in daily activities. Doing your shoulder blade drills in front of a mirror lets you check the quality of each movement.
- Rebuild confidence a step at a timeWorry about the shoulder slipping can make you tense up and move differently, which keeps the problem going. As your strength and control build, gradually take on the movements you have been avoiding out of fear.After a recent dislocation, leave the positions that feel unsafe until your rehab reaches them.
What I use in clinic
- Structured exercise programsStructured programs such as the Derby and Watson programs have reported improvements in pain, function and stability for instability that began without an injury (atraumatic).
- Rotator cuff and shoulder blade strengtheningProgressive strengthening of the muscles that hold the shoulder in place can help function and confidence.
- Position-sense and control training (proprioceptive and neuromuscular training)Exercises that sharpen your sense of where the arm is and how you control it may help joint control alongside strengthening.
- Whole-body movement trainingWorking on the trunk and legs as well as the shoulder may help in throwing and overhead sport.
- Gradual return to activityBuilding up step by step to the demands of your sport, with the load managed carefully, can reduce the risk of it happening again.
Treatments on this site
Book an assessment for shoulder instability and dislocationNextRecovery timeHow long it takes
- Weeks 0 to 6Building Control in Safe Positions
- Weeks 6 to 16Strengthening Through Movement and Position Sense
- Months 4 to 6+Return to Sport or High-Demand Activity
For a loose shoulder without a clear injury, rehab usually gets about 6 months before surgery is considered. After a first dislocation caused by an injury in a young athlete in contact or overhead sport, an early surgical opinion is often worthwhile. Improvement is usually gradual.
Instability that began without an injury often responds well to treatment without surgery. If rehab has not helped enough after 6 months, surgery may be considered.
What changes the timeline
- Type of instability (instability that began without an injury responds better than instability after one)
- Age at first dislocation and the type of sport affect the risk of it happening again
- Keeping up the exercise program affects recovery
- Age and activity level affect how well treatment helps
- Being very flexible in many joints (generalized hypermobility) may mean longer treatment
Progress. I track your confidence with daily activities, how often the shoulder slips or feels like it might, strength gains in key muscle groups, and whether you can do the activities that used to cause symptoms
Conditions that can feel similar
- Rotator Cuff Tear or Tendinopathy
- Weakness turning the arm against resistance and a painful arc, typically without a clear feeling of the shoulder slipping. Tests for the slipping feeling (apprehension and relocation tests) do not bring it on. It is more common as the main cause over age 40.
- SLAP Lesion or Labral Tear Without Frank Instability
- Deep clicking, pain with overhead loading, and pain in tests that load the labrum (O'Brien or dynamic labral shear tests). It often feels like a vague catching deep inside rather than the ball leaving the socket.
- Multidirectional Instability with Hypermobility
- Symptoms in more than one direction, a flexibility check across several joints (Beighton score) showing general looseness, and no clear injury. It frequently affects both shoulders and often responds well to the Watson or Derby-style programs.
- Cervical Radiculopathy
- Arm symptoms follow the path of one nerve and are brought on by tilting the head and pressing down on it (Spurling's test) rather than by shoulder positions. Shoulder instability tests do not bring on symptoms.
- Suprascapular Neuropathy
- An ache at the back and side of the shoulder with weakness and wasting of the cuff muscles over the shoulder blade (supraspinatus or infraspinatus), often in volleyball players or in people with a fluid-filled cyst beside the labrum on a scan (paralabral cyst). There is no worry that the shoulder will slip.
- Posterior Shoulder Instability
- Pain and slipping with the arm forward, across the body and turned in (bench press or push-up positions). Tests that push the ball backward in those positions bring on pain or a clunk (jerk and Kim tests). It is common in contact athletes and weightlifters, and easy to miss if only forward instability is tested.
What patients ask me most
Age at first dislocation is one of the strongest predictors. Hovelius's 25-year follow-up published in JBJS (2008) followed 255 patients after a first forward shoulder dislocation initially treated without surgery and found roughly half of shoulders in the 12 to 25 year age group eventually needed surgery to stabilise them or kept dislocating, while outcomes in patients 26 to 40 years were noticeably better. Data from the West Point and US military cohorts show similarly high re-dislocation rates in young contact athletes. If you are under 25, in-season in a collision sport, or a scan showed a large piece of bone broken off the front of the socket (bony Bankart lesion), the odds of re-dislocation without surgery are genuinely high and worth discussing with an orthopaedic surgeon early.
Not always. The choice between rehabilitation and a surgical referral depends on your age, activities and pattern of instability. For a young contact or overhead athlete with a dislocation from a clear injury and a tear of the front of the socket rim on MRI (Bankart lesion), early surgical stabilisation is increasingly supported by the literature. For an older person, someone with lower demands on the shoulder, or someone whose instability began without an injury or goes in several directions (atraumatic or multidirectional instability), a structured rehabilitation trial is the appropriate first step.
Atraumatic instability, including multidirectional instability, often responds well to structured rehabilitation. The Derby Shoulder Instability Program led by Bateman and colleagues, and the Watson MDI program, both report meaningful improvements in pain, function, and perceived stability with progressive shoulder blade and rotator cuff retraining. Surgery is reserved for those who do not respond to an adequate rehabilitation trial, typically six months or more.
For atraumatic instability managed without surgery, three to six months of progressive rehabilitation before unrestricted return to collision or overhead sport is a realistic window. The shoulder can still slip or dislocate again after returning, especially in collision sports. After surgery to repair the socket rim (Bankart repair), return usually takes four to six months or longer, following your surgeon's protocol. In athletes after stabilisation surgery, those who were not psychologically ready at six months, measured with the SIRSI questionnaire, had more recurrences (Pasqualini and colleagues, 2024). That study did not include people managed without surgery.
For many people, yes. Rebuilding the rotator cuff, the muscles around the shoulder blade, and the chain of muscles from the trunk down meaningfully improves how well the muscles hold the shoulder steady. This works well for atraumatic and multidirectional instability, and as part of rehab after surgery. It is less reliable when a large structural defect is causing the dislocations, such as a significant piece of bone missing from the socket rim (bony Bankart) or a dent in the ball that catches on the socket (engaging Hill-Sachs lesion).
Subluxation, where the ball partly slips out and then goes back in, and simply feeling that it might slip (apprehension) are both common. A labral tear, a loose, stretched joint capsule, or changed muscle control can all cause this. On examination I check whether placing the arm in the at-risk position brings on that worry and whether pressing the ball back eases it (apprehension and relocation tests), look for general looseness in the joints (generalised ligamentous laxity), and check shoulder blade control under load. Imaging is useful when the pattern does not fit, but the clinical picture usually drives the plan.
A SLAP tear is a tear of the superior labrum, the rim of cartilage at the top of the socket where the biceps tendon anchors. Burkhart and Morgan's 'peel-back' work described how the arm's position when it is cocked back to throw can extend these tears toward the back. SLAP lesions can cause deep clicking, pain with overhead loading, and a feeling of slight looseness (microinstability), but they are a distinct problem from the full dislocation pattern most people mean by shoulder instability. Treatment is usually non-surgical first.
Early work is static holds for the rotator cuff (isometrics) in safe positions with the arm at the side, plus shoulder blade control drills to rebuild the base the ball-and-socket joint needs. From there I progress to moving rotator cuff exercises, stability exercises with the hand on a wall or the floor (closed-chain), and position-sense challenges. Later phases bring back loading at the end of the range, jumping and throwing-type drills (plyometrics), and sport-specific demands in a controlled way. The whole program is built on the Derby and Watson frameworks with adjustments for your specific pattern.
The science of shoulder instability and dislocation
Shoulder occurs when the structures that normally keep your shoulder joint stable are compromised, allowing excessive movement or displacement of the humeral head within the glenoid socket. Your shoulder joint has more mobility than built-in stability, which makes it prone to instability.
The stability of your shoulder depends on both static restraints (joint capsule, ligaments, , and bony architecture) and dynamic restraints (muscle activation patterns and proprioceptive feedback). When these systems fail, your shoulder may (partially dislocate) or fully dislocate.
Atraumatic instability typically develops gradually due to repetitive microtrauma, generalized ligamentous , or muscle imbalances. This type often affects multiple directions and responds well to non-surgical treatment. Traumatic instability usually results from a specific injury that damages static restraints, most commonly anterior dislocations that tear the anterior capsule and labrum.
The neuromuscular system plays a crucial role in dynamic stabilization. When proprioceptive feedback is impaired or muscle activation patterns are altered, your shoulder may feel unstable even without structural damage.
Your shoulder's stability depends on the coordinated function of multiple muscle groups working together. The muscles provide dynamic compression and centering of the humeral head, while larger muscles like the latissimus dorsi and pectoralis major generate power for movement.
Scapular positioning and movement are critical for shoulder stability. Your scapula must provide a stable platform for the joint while allowing for coordinated movement during arm elevation. When occurs, it alters the mechanics of the entire shoulder complex and can contribute to .
In multidirectional instability, the joint capsule is often enlarged, allowing excessive translation in multiple directions. This creates a mechanical disadvantage for the dynamic stabilizers and requires enhanced neuromuscular control to maintain joint stability during functional activities.
The from your feet to your fingertips influences shoulder stability. Poor core stability, hip weakness, or altered movement patterns can create compensatory stresses that contribute to shoulder instability, particularly in overhead athletes.
What the studies show
Feeling ready to return to sport was linked to fewer repeat episodes after stabilisation surgery
A 2024 study followed 149 athletes for at least 2 years after surgery to stabilise the shoulder (Bankart repair or Latarjet surgery). The shoulder became unstable again in 20% of those who were not psychologically ready to return at 6 months (a score below 55 on the SIRSI questionnaire), compared with 4.3% of those who were.
Confidence in the shoulder is part of return to sport, so I check it alongside strength and control before clearing you for contact or overhead sport.
Pasqualini I, Rossi LA, Hurley ET, et al. Shoulder Instability-Return to Sports After Injury scale shows that lack of psychological readiness predicts outcomes and recurrence following surgical stabilization. Arthroscopy. 2024;40(12):2815-2824. PMID: 38735414.
Keep reading
Guides on shoulder pain
Related conditions
 Shoulder Impingement SyndromeInstability can cause secondary impingement from altered shoulder mechanics
 AC Joint SprainsTraumatic dislocations can involve both glenohumeral and AC joints
 Biceps TendinopathyShoulder instability can stress biceps tendon as secondary stabilizer
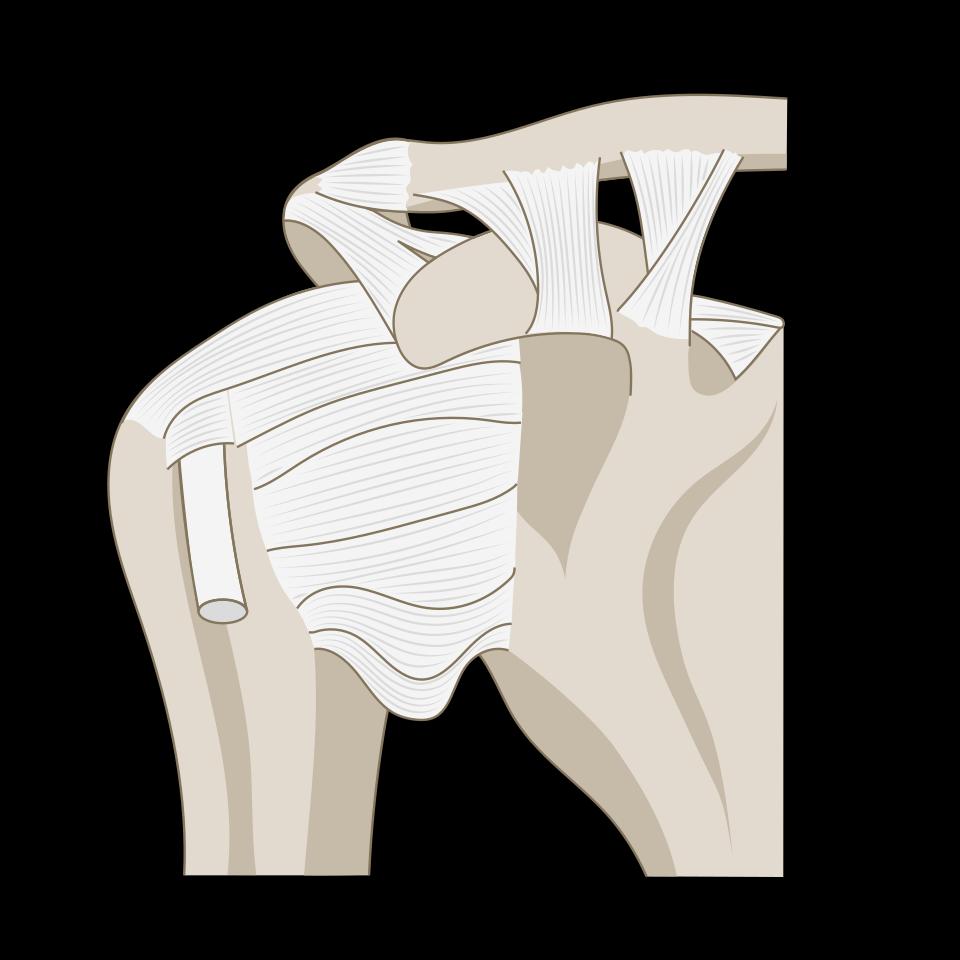 Frozen ShoulderPost-dislocation stiffness can develop into adhesive capsulitis
I write and review every page on this site myself, and the review date at the top is the last time I checked this one. If something here is out of date, tell me.
Getting back to it
Physiotherapy for shoulder instability and dislocation, built around the activity you want back.