
Sciatica
Sciatica is pain travelling from the lower back or buttock down the leg, usually from irritation of a nerve root in the lower back. Numbness, tingling or weakness can accompany it. Sitting, bending or coughing may aggravate symptoms; for others, standing or walking does. The pattern depends on the underlying problem.
Key points
- What usually helps
- Staying active, and the movements that ease the leg pain or draw it back toward the spine.
- What you can do now
- Keep moving and keep working if you can. Walk in short, frequent bouts.
- How long it takes
- Many people improve within 4 to 6 weeks, and most recover within about 3 months.
- When to see a doctor first
- Some signs need emergency care. Check the list before you start treatment.
Symptoms
Does this sound like you?
- Pain that travels from the back through the buttock and down the leg
- Sharp, burning or electric-like sensations
- Numbness or tingling in the leg or foot
- Weakness in particular leg muscles
- Worse with sitting, bending, or coughing
Often alongside it
- Back pain along with the leg symptoms
- Difficulty finding comfortable positions
- A change in the way you walk
- Night pain affecting sleep
- Muscle cramps in the affected leg
Often starts in the back, then travels down the leg. The same positions bring it on each time. It may be constant, or come and go with positions and activities.
Before using this comparison, check when these symptoms need a doctor first.
When to see a doctor first
Go to emergency
New trouble starting to pass urine or feeling it pass, new loss of bladder or bowel control, new numbness between the legs or around the back passage, new loss of genital sensation or sexual function, or severe or rapidly worsening weakness in both legs
Go to emergency now. These can be signs of cauda equina syndrome
Sudden unexplained weakness or numbness in an arm or leg, even if it improves
Call 911 now. This can be a stroke. Do not wait for a physiotherapy appointment
Get seen today
Pain that suddenly starts down both legs, or spreads from one leg to both, even without the signs above
Contact a medical clinician today for a same-day assessment
A new foot drop (the foot catches or slaps when you walk), or weakness in one leg that is getting worse
Same-day medical assessment
Fever or feeling generally unwell with back and leg pain
Same-day medical assessment
Back and leg pain after a fall or other trauma
Same-day medical assessment to rule out a fracture
Check with your doctor
Leg pain with a history of cancer, unexplained weight loss, or constant pain at night
See your family doctor before starting physiotherapy
Treatment
How it is treated
Main approach. Staying active, and using movements that ease the leg pain or draw it back up toward the spine, can help. When one direction of movement clearly eases it (a directional preference), that often goes with a quicker recovery.
Alongside it. Gentle nerve gliding exercises, which slide the nerve back and forth, may help pain and movement when the nerve is sensitive to stretch.
Managing it over time. Keeping up regular exercise and walking after the leg settles may lower the chance of another episode.
A typical rehabilitation progression
Three phases, from settling symptoms to returning to full activity.
Recovery from sciatica is usually staged: calm the symptoms first, then rebuild the strength and capacity of the area, then return to your full activities. The phases below show how that can progress.
Phase 1Calming the Nerve and Finding the Direction That Eases It
Calm the irritated nerve, find positions and movements that draw symptoms back up toward the spine ( them), and get basic movement comfortable again. Testing which direction of movement eases symptoms, and using it when one clearly does (), is supported by the low back pain clinical guideline published in the Journal of Orthopaedic and Sports Physical Therapy.
Example exercises
- Press-ups lying on your stomach (Cobra), 10 repetitions every 2 to 3 hours, if arching back draws the symptoms back toward the spine
- sliders (gentle movements that slide the nerve back and forth), sitting with your legs out straight or lying on your back, 10 to 15 slow repetitions, stopping before leg symptoms come on
- Short, frequent walking bouts of 5 to 10 minutes rather than one long walk
- Resetting your sitting position with a small rolled support behind your lower back ( roll), and standing breaks every 30 minutes
Possible progression milestones
Leg symptoms easing or moving back toward the back, numbness and any weakness stable or improving, only mild pain at rest, and sitting for 20 to 30 minutes without a flare-up.
Phase 2Building Up Load and Trunk Control
Rebuild strength and tolerance in the trunk and hips, get confident bending from the hips (hinging) and squatting again, and move nerve exercises on from sliders to tensioners (which put gentle stretch on the nerve) as you can manage them. The Lancet series on low back pain recommends exercise built up step by step, and education, over treatments that are done to you (passive treatments).
Example exercises
- Bird dog (on hands and knees, reaching out the opposite arm and leg) and dead bug (on your back, lowering the opposite arm and leg), 2 to 3 sets of 8 to 10 per side, keeping your back steady in its natural middle position
- Hip hinge progressions (bending forward from the hips with a flat back): broomstick hinge, kettlebell deadlift, then single-leg Romanian deadlift
- Goblet squat to a box (holding a weight at your chest), 3 sets of 8 to 10, progressed in depth and load as symptoms allow
- Glute bridges and side-lying leg lifts () to strengthen the buttock muscles, which are often weak in this group
- Sciatic nerve tensioners lying on your back or sitting slumped, in short ranges, 8 to 10 controlled repetitions
Possible progression milestones
Hip hinging and squatting with weight, with only mild discomfort that settles, a full workday with normal sitting, and walking for 30 minutes or more without a flare-up.
Phase 3Return to Full Activity and Resilience
Rebuild strength and tolerance for what you are going back to, whether lifting at work, running or sport. The focus shifts to heavier loads and faster tasks. Another episode in the first year is common, and a maintenance plan of regular exercise may lower the chance of it.
Example exercises
- Barbell or trap-bar deadlift, built up gradually from light weights, 3 to 4 sets of 5
- Squats with the weight held in front (front-loaded squats) or split squats, at your training weights, matched to your goals
- Farmer and suitcase carries (walking with a weight in both hands, or in one hand) for trunk and grip, 3 to 4 rounds of 30 to 40 metres
- Return to running or sport built up step by step, starting with walk-run intervals
- Strengthening twice a week to maintain your gains, which you can keep up on your own
Possible progression milestones
Managing full work, home and leisure demands with minimal or no pain, confidence handling minor flare-ups yourself, and a written maintenance plan for ongoing strength work.
What you can do now
- Keep moving and keep working if you can. Staying active, and at work in some form, is linked to better outcomes than bed rest. In the early weeks, adjust how long you sit, how much you lift and how far you drive rather than stopping, because complete rest beyond a day or two tends to slow recovery.Signs such as new trouble passing urine, loss of bladder or bowel control, or numbness between the legs or around the back passage mean go to emergency now, as the warning signs on this page explain.
- Walk in short, frequent bouts. Take walks of 5 to 10 minutes rather than one long walk. Gentle walking helps keep the nerve moving and keeps you out of long sitting; if it reliably makes the leg worse, try a shorter distance, a different pace or a different posture.
- Break up sitting every 30 minutes. Long sitting and slumped driving aggravate many people's sciatica. Stand up every 30 minutes, and try a small rolled support behind your lower back when you sit.
- Use the positions that ease your leg. Sitting and bending aggravate some people, while standing and walking aggravate others. Use the positions that ease your leg symptoms for now and gradually rebuild your tolerance for the others; pain in one position does not by itself mean the nerve is being squeezed more.
- Watch which way the leg pain moves. Pain moving back up the leg toward the spine (centralizing) tends to go with a faster recovery. Symptoms spreading further down the leg are a sign to ease off whatever brought them on.Leg weakness that is new or getting worse, a foot that catches or slaps when you walk, or pain that spreads to both legs needs a same-day medical assessment.
What I use in clinic
- Nerve mobility exercises (neural mobilization). Gentle movements that slide the nerve back and forth. They may help reduce nerve sensitivity, though the evidence is limited.
- Exercises in the direction that eases you (directional preference). These can help when one direction of movement clearly eases the leg symptoms.
- Education and Advice. Knowing what is happening and that most sciatica settles can make it easier to stay active.
Recovery
How long it takes
Many people see meaningful improvement within 4 to 6 weeks, and most recover within about 3 months without surgery. Leftover symptoms can take 3 to 6 months to settle fully.
Many people improve without surgery. Surgery is considered for worsening weakness, cauda equina syndrome, or leg pain that stays severe and disabling despite appropriate care.
What changes the timeline
- How much pressure there is on the nerve affects the timeline
- Moving and staying active early helps recovery
- Breaking up long periods of sitting often helps
- Worry, low mood and stress (psychological factors) influence recovery
How I track it. I track how much the pain gets in the way of the tasks that matter to you, how well you move when I test those tasks in clinic, and how confident you feel in daily activities
Similar conditions
Conditions that can feel similar
- Lumbar Radiculopathy (Disc or Foraminal)
- Pain runs down the leg along the path of one nerve (a dermatomal pattern). Lifting the straight leg, or sitting slumped and straightening the knee, brings it on (straight leg raise or slump test). Often particular muscles are weak or a reflex is changed. Symptoms typically get worse with sitting, bending forward, coughing or sneezing.
- Piriformis Syndrome / Deep Gluteal Syndrome
- Deep buttock pain that can spread down the back of the thigh without clear back pain. Brought on by long sitting, by stretching the deep buttock muscles in set positions (FAIR or seated piriformis stretch tests), and by pressing deep in the buttock. Checks of the nerves are usually normal.
- Sacroiliac Joint Dysfunction
- Pain just below the lowest bone of the lower back (L5), near the bony bump at the back of the pelvis (the PSIS), often pointed to with one finger. A group of tests that press on or stretch the joint helps confirm it (distraction, compression, thigh thrust, FABER and Gaenslen tests). The pain rarely spreads below the knee and does not follow the path of one nerve.
- Hip Osteoarthritis
- Pain in the groin or front of the thigh, and turning the hip inward is limited and painful (hip internal rotation). Worse standing and walking on the leg, not with back positions. Checks of the nerves are normal, and moving the back neither draws the pain up toward the spine nor pushes it further down the leg.
- Proximal Hamstring Tendinopathy
- Pain in one spot on the sitting bone (ischial tuberosity), worse sitting on firm surfaces, lunging or sprinting. Pressing where the hamstring attaches is tender, and working the hamstring against resistance brings the pain on. Stretching the nerve or leaning the back backward does not.
- Facet-Mediated Referred Pain
- Pain spreads into the buttock or back of the thigh, typically not past the knee. Worse leaning back and twisting rather than bending forward. Checks of the nerves are normal, and lifting the straight leg does not bring on true nerve pain down the leg.
Commonly confused with
Side-by-side comparisons for patterns that often get mistaken for sciatica.
Questions
What patients ask me most
How long does sciatica take to heal?
Most people see meaningful improvement within 4 to 6 weeks, and the majority recover within 3 months without surgery. Recovery is rarely linear. Leg symptoms often improve in stages, and some residual sensations can linger for several months even as function returns. The most useful signal I track is whether the pain is moving back up the leg toward the spine (centralizing), which tends to predict a faster recovery.
Can I still work with sciatica?
For most people, yes. Staying active and at work in some capacity is linked to better outcomes. NICE and the Lancet Low Back Pain Series both recommend continued activity rather than bed rest. What usually helps is adjusting how long you sit, how much you lift and how far you drive in the early weeks. Complete rest beyond a day or two tends to slow recovery, not speed it up.
Do I need an MRI for sciatica?
Usually not in the first 4 to 6 weeks. NICE NG59 and the American College of Physicians guidance both recommend reserving MRI for cases with warning signs, weakness that keeps getting worse, or symptoms that do not improve with non-surgical care, where a scan would actually change the plan. Imaging too early often shows disc changes that are present in pain-free people and can lead to treatment you do not need.
Is walking good for sciatica?
Usually yes, as long as it does not send symptoms further down the leg. Regular, gentle walking helps keep the nerve moving, reduces stiffness, and keeps you out of long sitting, which is one of the biggest aggravators I see. If walking draws the leg pain back toward the spine or eases it, that is a positive sign. If it reliably worsens leg symptoms, I adjust distance, pace, or posture.
What positions make sciatica worse?
Long periods of sitting, slumped driving and deep forward bending aggravate many people's sciatica, while standing or walking aggravates others. Coughing, sneezing and straining can spike it too. The response depends on what is irritating the nerve: disc-related sciatica is often worse with sitting and bending, while narrowing around the nerve's exit is more often brought on by standing and arching back. I use the positions that ease your symptoms and gradually rebuild your tolerance for the others. Pain in one position does not by itself mean the nerve is being squeezed more.
When should I worry about sciatica?
Go to emergency now for new trouble starting to pass urine or feeling it pass, new loss of bladder or bowel control, new numbness between the legs or around the back passage, or severe or rapidly worsening weakness in both legs. New loss of genital sensation or sexual function with back or leg pain also needs emergency assessment. These can be signs of cauda equina syndrome. Contact a medical clinician today if pain suddenly starts down both legs or spreads from one leg to both, even without those signs. A new foot drop (the foot catches or slaps when you walk) or worsening weakness in one leg needs a same-day medical assessment. Sudden unexplained weakness or numbness in an arm or leg, even if it improves, can be a stroke: call 911 now. Severe, unrelenting night pain, unexplained weight loss or a history of cancer need a medical review before physiotherapy, and fever with back pain needs one the same day.
Does sciatica always come from a disc?
No. A herniated disc is the most common cause, but sciatic-type pain can also come from narrowing of the opening where the nerve leaves the spine (foraminal stenosis), the deep buttock muscles such as piriformis, sacroiliac joint irritation, or pain referred from the hip. Sorting out which structure is actually driving symptoms matters, because the plan changes significantly depending on the source.
Do I need surgery for sciatica?
Surgery is rarely the first step, and many people improve without it. For selected people with persistent, disabling disc-related leg pain, surgery can give faster relief. The SPORT trial (Weinstein and colleagues, JAMA 2006) found substantial improvement with both surgery and non-surgical care, but so many people switched groups that its randomised comparison is hard to interpret, and analyses based on the treatment people actually received favoured surgery, including at eight years (Lurie and colleagues, Spine 2014). Surgery is considered when there is worsening nerve weakness or cauda equina syndrome, or when leg pain stays severe and disabling after 6 to 12 weeks of appropriate treatment. The decision depends on your symptoms, nerve function, scan findings and preferences.
The science
The Science of Sciatica
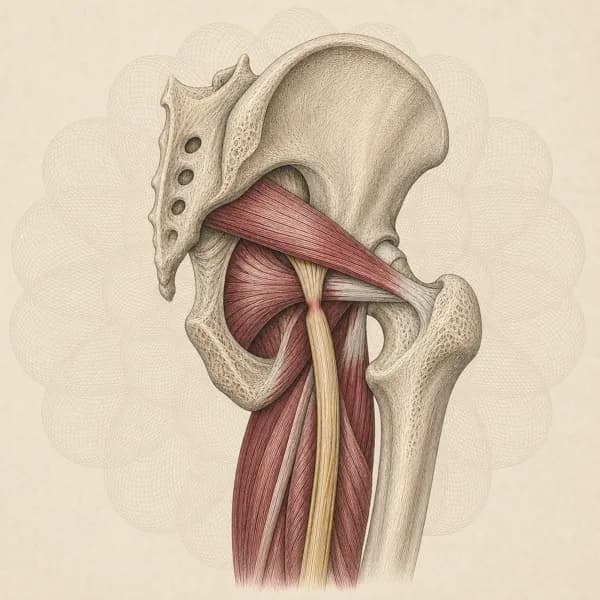
Sciatica describes pain along the path, usually from compression or irritation at the spine level. The nerve can be affected by disc material, , or tight muscles along its path. Similar to general low back pain, sciatica often involves disc dysfunction, but with the added complexity of compression or irritation.
When the nerve is irritated, it can cause pain, numbness, or weakness anywhere along its path from the back to the foot. The location and type of symptoms help identify where the problem originates. In some cases, sciatica occurs alongside disc disease or spinal , so the assessment looks at all of them.
Contributing factors
Long spells of sitting are the most common aggravator I see once sciatica has started. A slumped sitting position puts the irritated nerve on more stretch and keeps it there, which is why getting up often helps more than finding the perfect chair.
Sciatica often starts with an ordinary movement, such as bending to pick something up, after a period of heavier load, poor sleep or less activity than usual. That does not mean bending is dangerous. Early on it helps to ease off deep, loaded bending, especially in the first hour after waking, and then bring it back gradually as the leg settles.
Strength and fitness matter for recovery and for the next flare. A back and hips that are used to load, and a habit of walking most days, give the nerve the best conditions to settle.
Research
What the studies show
Physiotherapy for sciatica: what a review of 18 trials found
This review of 18 trials (2,699 people) found that the evidence on physiotherapy for sciatica is limited and varied, and most trials had a high risk of bias (flaws that can skew the results). Physiotherapy did better than minimal care, such as advice alone, for pain in the long term. Overall, the authors concluded there is not yet enough good-quality evidence to make firm recommendations.
Sets realistic expectations: physiotherapy can help, particularly compared with advice alone, but the evidence base is still uncertain, so care is tailored to the individual presentation.
Dove L, Jones G, Kelsey LA, et al. How effective are physiotherapy interventions in treating people with sciatica? A systematic review and meta-analysis. Eur Spine J. 2023;32(2):517-533. PMID: 36580149.
Related Conditions
Conditions I commonly see alongside, or confused with, this one.
Getting back to it
Physiotherapy for sciatica, built around the activity you want back.
