
Plantar Fasciitis & Heel Spurs
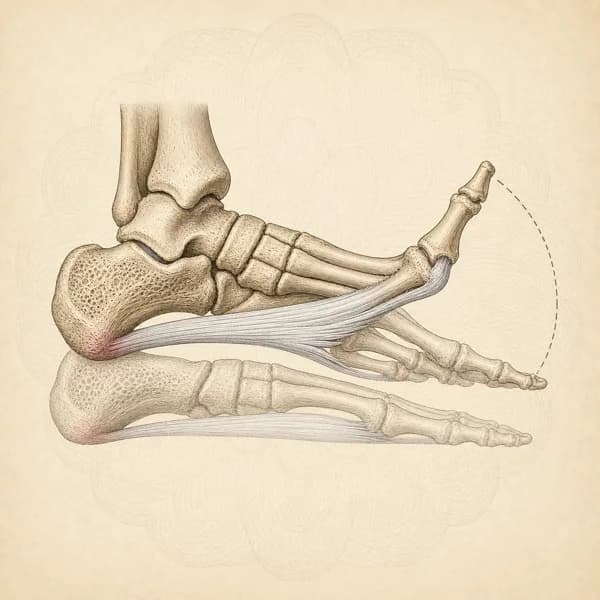
Plantar fasciitis, also called plantar fasciopathy, is pain where the thick band of tissue under the foot (the plantar fascia) attaches to the heel. It is usually sharpest with the first steps in the morning or after sitting and eases as you move. Heel spurs can show on X-rays, including in people without heel pain.
Key points
- What usually helps
- Stretching the sole and the calf, done consistently, with calf strengthening and supportive shoes.
- What you can do now
- Stretch the sole before your first steps. Stretch both calf muscles twice a day.
- How long it takes
- Usually months rather than weeks; many see clear improvement within 6 to 12 months.
- When to see a doctor first
- Some signs need medical care the same day. Check the list before you start treatment.
Symptoms
Does this sound like you?
- Sharp heel pain with your first steps in the morning
- Pain after prolonged sitting
- Pain worse at beginning of activity
- Tenderness along arch or heel
- Difficulty with prolonged standing
Often alongside it
- Arch fatigue or cramping
- Knee or hip pain from walking differently to protect the heel
- Walking differently to keep weight off the sore heel
- Calf tightness
- Occasional burning sensation in heel
The typical pattern is pain with the first steps in the morning that eases once you get moving, then builds again with long periods on your feet. It often comes on gradually.
Before using this comparison, check when these symptoms need a doctor first.
When to see a doctor first
Get seen today
Unable to put weight on the foot after a fall, jump, or twist
Go to urgent care or emergency for an X-ray to rule out a fracture
A hot, red, swollen heel, or fever
Same-day medical assessment for a possible infection
Check with your doctor
Heel pain that is there at rest or at night, or pain when the heel is squeezed from both sides, especially after a jump in training
See your family doctor before starting physiotherapy, to rule out a stress fracture of the heel bone
Numbness, burning, or tingling in the sole or toes
Tell me at the assessment; if it is spreading or getting worse, see your family doctor to check for a nerve problem
Pain in both heels with swelling in other joints, back stiffness in the morning, or eye inflammation
See your family doctor to check for an inflammatory arthritis
Treatment
How it is treated
Main approach. A stretch aimed at the band of tissue under the foot (plantar fascia-specific stretching), together with calf stretching, can meaningfully reduce morning pain when done consistently over 8 to 12 weeks.
Alongside it. Strength training that builds up to heavy loads stimulates the tissue to rebuild (remodelling) and improves how much load it can take. Foot orthoses (shoe inserts) provide pain relief and better function in the medium term, as one part of a combined plan.
Managing it over time. An assessment of how your foot and ankle move, working on foot posture, ankle flexibility and the strength of the small muscles inside the foot (intrinsic muscles), may lower the chance of it coming back, alongside supportive footwear and gradual changes in how much you stand and run.
A typical rehabilitation progression
Three phases, from settling symptoms to returning to full activity.
Recovery from plantar fasciitis & heel spurs is usually staged: calm the symptoms first, then rebuild the strength and capacity of the area, then return to your full activities. The phases below show how that can progress.
Phase 1Easing Pain and Building Tolerance (Weeks 1 to 4)
Reduce morning pain and pain when the foot takes load, while starting gentle loading of the tissue. A stretch aimed at the (plantar -specific stretching), supported by a 2003 study by DiGiovanni and colleagues, is the core of the morning routine. Stretching both calf muscles (gastrocnemius and soleus) addresses the most common limitation noted in the 2023 clinical guideline for heel pain (Koc et al.): the ankle not bending up toward the shin as far as it should (limited ). Loading is light and focused on consistency.
Example exercises
- Plantar fascia-specific stretch, done sitting before you stand: cross the sore foot over the opposite knee, pull the toes back toward the shin, hold 10 seconds, repeat 10 times, 3 times a day, including every morning before your first steps
- Calf stretch with the knee straight (gastrocnemius), 30 seconds, 3 repetitions per side, twice a day
- Lower calf stretch with the knee bent (soleus), 30 seconds, 3 repetitions per side, twice a day
- Seated heel raises with the knee bent to roughly 90 degrees, for the lower calf muscle (soleus), 3 sets of 15
- Pacing your day: shorten long spells of standing, rotate between supportive shoes, and take short walking breaks during long periods of standing
Possible progression milestones
Possible milestones, adapted to the person rather than treated as fixed cut-offs: morning first-step pain low and settling over several days, a longer walk tolerated without escalating pain, and no next-day symptom rise after stretching and early loading sessions.
Phase 2Heavy Strength Training (Weeks 4 to 12)
Rebuild how much load the fascia and calf can handle, with a program adapted from a 2015 heavy-loading study by Rathleff and colleagues. The main exercise is a slow single-leg heel raise with the toes bent upward (dorsiflexion), done every second day: 3 seconds up, a 2-second pause, 3 seconds down. Load builds from body weight toward carrying a backpack or using a calf-raise machine, moving from sets with more repetitions toward heavier sets with fewer across the block. Stretching continues to maintain the gains rather than as the main treatment.
Example exercises
- Heavy single-leg heel raise on a step with a towel rolled under the toes, 3 sets every second day: 3 sets of 12 repetitions in weeks 1 to 2, progressing to 3 sets of 10, 3 sets of 8, then 3 sets of 6 with added load by weeks 8 to 12
- Continued calf and plantar fascia-specific stretching as maintenance, daily
- Strengthening for the muscle that supports the inner arch (tibialis posterior) and the small muscles inside the foot, such as short-foot holds (gently raising the arch without curling the toes) and turning the foot inward against resistance (resisted ), 3 sets of 10 to 15
- Strengthening for the muscles on the side of the hip (hip ) and the main buttock muscle (gluteus maximus), to help share the load through the leg, 3 sets of 10 to 12
- Supportive shoes during the busier standing parts of your day, with or without an over-the-counter shoe insert (orthosis)
Possible progression milestones
Possible milestones, adapted to the person rather than treated as fixed cut-offs: scores on a foot questionnaire (the Foot Function Index) improving meaningfully from the start, loaded single-leg heel raises tolerated with low pain, and normal walking and standing managed consistently without flare-ups the next day.
Phase 3Return to Running, Sport, and Prevention (Months 3 to 6+)
Rebuild tolerance for impact and return to running, work that keeps you on your feet, or sport. Loading continues twice a week to keep the gains and lower the chance of it coming back. Training volume rises in small weekly steps, with hills and speed work brought back last. For people who do not run, the aim is to stand and walk as much as you need without limits.
Example exercises
- Walk-run progression starting at 1 minute run, 2 minutes walk, building toward continuous running on soft surfaces over 3 to 4 weeks
- Hopping drills (), progressing from small, springy two-leg hops (pogo hops) to single-leg hops on a soft surface, 3 sets of 10 to 20
- Continued heavy calf raise work, 3 sets of 6 to 12 with load, twice weekly as maintenance
- Gradual reintroduction of hills, speed work, and harder surfaces once continuous easy running is symptom-free
- Training log tracking volume, surface, and symptoms to catch load spikes early
Possible progression milestones
Running, walking or standing as much as you want without pain on your first steps in the morning, scores on the foot questionnaire (Foot Function Index) steady at or near pre-injury levels, and 4 or more weeks in a row of training or work without symptoms.
What you can do now
- Stretch the sole before your first steps. Before you stand up in the morning, and before long spells of standing, sit and cross the sore foot over the opposite knee. Pull your toes back toward the shin until you feel a stretch along the sole, hold 10 seconds and repeat 10 times, 3 times a day.First-step pain usually eases within 10 to 15 minutes. If it stays sharp for longer, or comes with tingling or burning, tell me at your assessment, and see your family doctor if the tingling is spreading or getting worse.
- Stretch both calf muscles twice a day. Stretch the calf with the knee straight and again with the knee bent, holding each for 30 seconds, 3 times per side. This helps the ankle bend up toward the shin, the most common limitation in heel pain.A stretch should feel firm, not sharp; do not force through sharp pain.
- Load the calf with slow heel raises. Loading generally does better than rest. Start with seated heel raises, knee bent to about 90 degrees, 3 sets of 15; the slow single-leg heel raise with a towel bunched under the toes, every second day, is the main strengthening exercise later on.If the heel is more sore the next day, ease back and build up more slowly.
- Break up standing, wear supportive shoes. Shorten long periods on your feet where you can, take short walking breaks, and rotate between supportive shoes, with or without an over-the-counter insert. Shoes and inserts can ease symptoms while calf and foot strength rebuilds; they add to the exercises rather than replace them.Avoid going barefoot at first.
- If you run, keep within clear limits. Once the heel has been assessed, you can often keep running with adjustments, as long as pain during a run stays mild, settles within 24 hours and does not rise from week to week. Cut back volume, use softer surfaces and leave hard hill and speed work for later.These are example limits, not proof that running is safe for every cause of heel pain; if the pain goes beyond them, a short break with cross-training often gets runners back to normal volume faster than pushing through. Heel pain at rest or at night, or pain when the heel is squeezed from both sides, especially after a jump in training, needs your family doctor before physiotherapy, to rule out a stress fracture of the heel bone.
What I use in clinic
- Calf and Plantar Fascia Stretching. Consistent stretching can reduce pain and improve function.
- Progressive Loading. High-load heel raises reduced pain and improved function sooner than stretching in a randomised trial (Rathleff et al., 2015), with similar results by 6 and 12 months.
- Hands-on treatment (manual therapy). Gentle joint movement (joint mobilization) and soft tissue work can give short-term relief when added to stretching or strengthening.
- Taping. Supportive taping of the arch can ease pain in the short term and is supported in the 2023 clinical guideline for heel pain (Koc et al.).
Recovery
How long it takes
Recovery usually takes months rather than weeks. Most people who keep up consistent treatment without surgery see clear improvement within 6 to 12 months. In a long-term study of people referred to a hospital clinic, though, close to half still had some symptoms 10 years after it started (Hansen et al., 2018). Recovery often has ups and downs, with periods of improvement followed by flare-ups.
Most people improve with consistent non-surgical care, although it often takes many months. A small number who still have significant pain after a thorough trial of non-surgical care go on to discuss an injection or surgery with a physician.
What changes the timeline
- How long you have had symptoms before starting treatment: a shorter history predicts a better outcome
- Being female, and having pain in both heels, are associated with poorer long-term outcomes
- Body weight (BMI) and an unusual foot shape or posture influence how recovery goes
- Calf strength (the muscles that point the foot down), and pain easing with taping, predict whether orthotics will help
How I track it. I track your morning pain, how long you can stand and walk, and the everyday activities that matter to you
Similar conditions
Conditions that can feel similar
- Calcaneal Stress Fracture or Calcaneal Bone Stress
- Squeezing the heel bone from both sides brings on the pain, while bending the toes back does not. Standing and walking hurt at any time of day, and the sharp first-step pain typical of plantar fasciitis is absent or minor compared with the pain of being on your feet. A recent quick rise in training, or risk factors for poor bone health, point toward a bone stress injury rather than the fascia.
- Fat Pad Contusion or Atrophy
- Pain sits directly under the centre of the heel, rather than slightly further forward where the fascia attaches to the heel bone. It worsens with walking barefoot on hard surfaces and eases with well-cushioned shoes, and classic morning first-step pain is often mild or absent. Older adults, and athletes who land hard on their heels, are more commonly affected.
- Baxter's Nerve (First Branch of Lateral Plantar Nerve) Entrapment
- The pain burns or tingles. The tender spot is on the inner side of the heel, over a small muscle there (abductor hallucis), rather than where the fascia attaches. Symptoms stay or even get worse at rest instead of easing with movement, and morning pain varies. Tests that press on or stretch the nerve reliably bring on the symptoms; loading the fascia does not.
- Tarsal Tunnel Syndrome
- Numbness, tingling or burning that spreads into the sole and toes along the path of the nerve behind the inner ankle (the posterior tibial nerve). Pain often worsens at night or with long periods of standing. Tapping over the nerve behind the inner ankle bone sets off tingling (a Tinel sign), and positions that stretch the nerve bring on the symptoms. Those findings separate it from plantar fasciitis.
- Plantar Fascia Rupture
- A sudden tearing sensation during a push-off or jump, often with an audible pop, immediate bruising in the arch over the following 24 to 48 hours, and difficulty bearing weight. This is an acute event rather than a gradual build, and it usually needs a period of protected loading before the typical loading program resumes.
- Posterior Tibial Tendinopathy
- Pain runs behind and below the inner ankle bone and up into the deep calf, rather than sitting at the heel. When you rise onto your toes on one leg, the heel does not tip inward as it should and the arch flattens. Pressing on the plantar fascia is usually comfortable, while the tendon behind the inner ankle (the posterior tibial tendon) is consistently tender.
Questions
What patients ask me most
I have a heel spur on my X-ray. Is that the cause, and does it need removing?
A heel spur is a bony change that can show up on an X-ray, including in many people who have no heel pain at all. It does not by itself identify the cause of your symptoms, and it does not usually need to be removed. Treatment usually focuses on the painful tissue under the heel and on how much walking and standing your foot tolerates, rather than on the spur. Physiotherapy does not remove a spur, and symptoms can settle while the spur stays exactly as it is.
Why does my heel hurt the most with my first steps in the morning?
That first-step pattern is a common feature of plantar fasciitis. Overnight the fascia sits in a shortened position with no load through it. The first steps suddenly load tissue that has not been warmed up, which brings on sharp pain. It usually eases within 10 to 15 minutes as the fascia warms up and gets used to the morning loading. Pain that stays sharp beyond that window, or that is accompanied by tingling or burning, pushes the picture toward other causes.
How long does plantar fasciitis take to get better?
Most people improve significantly within 3 to 6 months of structured rehab, and a substantial majority are much better within 12 months. However, it is a slow-moving condition and in a long-term study of people referred to a hospital clinic, close to half still had some symptoms years later (Hansen et al., 2018). The more reliable predictor than any one treatment is consistency with calf and fascia loading, managing daily standing and walking volume, and addressing training spikes rather than pushing through.
Does stretching actually work for plantar fasciitis?
Yes, particularly plantar fascia-specific stretching. DiGiovanni and colleagues (JBJS 2003) showed that a tissue-specific plantar fascia stretch, pulling the toes back into extension with the hand, produced better outcomes than calf stretching alone in chronic cases. I typically combine both: calf stretching to restore how far the ankle bends up toward the shin, and fascia-specific stretching done before your first steps in the morning and before long periods of standing.
Should I strengthen my foot or just rest?
Loading generally wins over rest. Rathleff and colleagues (Scandinavian Journal of Medicine and Science in Sports, 2015) compared high-load calf and fascia strengthening against stretching alone and found better results at 3 months with the loading program, with similar results by 6 and 12 months. The exercise is a slow single-leg heel raise with a towel bunched under the toes to put the fascia on tension. It is performed every second day, with a slow tempo and progressive load.
Do I need orthotics or new shoes?
Orthoses and supportive footwear can reduce symptoms, particularly in the short to medium term, and they are a reasonable addition to a loading program rather than a substitute for it. The 2023 JOSPT heel pain guideline (Koc et al.) supports foot orthoses as one part of a combined approach. I usually use them as a bridge while calf and fascia capacity rebuilds, rather than as a long-term dependency.
Are cortisone injections a good idea?
Short-term pain relief is often real, but the effect typically fades within weeks and injections carry a small but notable risk of thinning the heel's fat pad (fat pad atrophy) and of the fascia rupturing. I rarely recommend cortisone as a first step. When someone has genuinely plateaued after months of consistent loading, a single targeted injection can sometimes break the cycle, but it is not a substitute for loading, footwear, and load management.
Do night splints help?
They can reduce morning pain for some people, particularly in cases that have been present for several months. The mechanism is keeping the fascia on a gentle stretch overnight so the first steps are less painful. Evidence is modest and tolerance is mixed because they can disrupt sleep. I use them selectively rather than routinely.
Can I keep running with plantar fasciitis?
Often yes, with adjustments, once the heel has been assessed. One way to monitor it: pain during a run stays mild, settles within 24 hours, and does not rise week over week. These are example monitoring limits, not proof that running is safe for every cause of pain. Reducing volume, running on softer surfaces, and avoiding hard hill or speed work early on can keep things manageable. If the pain does not stay within those limits, a short pause with cross-training often gets a runner back to normal volume faster than pushing through.
The science
The Science of Plantar Fasciitis & Heel Spurs
Plantar fasciopathy (commonly called plantar ) is a condition affecting the origin at the heel bone, characterized by thickening and disorganized structure rather than acute inflammation. The plantar is a thick fibrous band that supports the foot's medial longitudinal arch and acts as a shock absorber during weight-bearing activities.
The condition develops when cumulative mechanical stress on the fascia exceeds its adaptive capacity, leading to a failed healing response. This results in small tears, tissue degeneration, and thickening at the insertion point. Despite the name "fasciitis," the is primarily degenerative (fasciopathy) rather than inflammatory, similar to other chronic tendon conditions.
Contributing factors include sudden increases in weight-bearing activity, biomechanical abnormalities such as limited ankle from calf tightness, abnormal foot postures (both flat feet and high arches), and weakness in the . The fascia is particularly vulnerable at its attachment to the heel bone, where mechanical stress concentrates during push-off activities. Plantar fasciopathy often coexists with other lower limb conditions including Achilles and chronic ankle , as they share common biomechanical risk factors.
Contributing factors
Several biomechanical factors can contribute to plantar development. Tight calf muscles (particularly the plantarflexors) limit ankle flexibility, which is the most commonly reported biomechanical impairment. This forces increased stress transmission through the during gait. Altered foot mechanics like excessive or high arches change how forces distribute through your foot.
Sudden increases in activity, changes in footwear, or prolonged standing on hard surfaces can overload the tissue. Body weight significantly influences the load on your feet, with higher BMI being the most common identified risk factor for plantar fasciitis in non-athletes. Ground reaction forces multiply during walking and running, particularly affecting the plantar during push-off phases.
Research
What the studies show
Physiotherapy treatments for plantar fasciitis: a review that pooled 21 trials
Across 21 trials with 1,196 people, physiotherapy treatments showed a small trend toward less pain at one month, but not a clear difference, and no clear effect on function. The authors rated the overall evidence as low quality and described shockwave therapy and kinesiology taping as the most promising options.
Shows how uncertain the evidence is for any single physiotherapy treatment, which is why care combines several approaches rather than relying on one.
Raj S, Sharma C, Sundus H. Effect of different physiotherapeutic interventions in plantar fasciitis: A systematic review and meta‐analysis of randomized controlled trials. Musculoskelet Care. 2025;23(3):e70151. PMID: 40596749.
Shockwave therapy for plantar fasciitis and tendon problems: a systematic review
For plantar fasciitis, shockwave therapy (extracorporeal shockwave therapy) made a clear difference to pain and function in the short and long term. In people with long-standing plantar fasciitis, focused shockwave therapy was linked with a higher success rate and more pain reduction than a fake (sham) treatment.
Supports shockwave as an option for persistent plantar heel pain; the same review found little benefit for kneecap (patellar) and Achilles tendon problems.
Charles R, Fang L, Zhu R, Wang J. The effectiveness of shockwave therapy on patellar tendinopathy, Achilles tendinopathy, and plantar fasciitis: a systematic review and meta-analysis. Front Immunol. 2023;14:1193835. PMID: 37662911.
Related Conditions
Conditions I commonly see alongside, or confused with, this one.
Achilles Tendinopathy / Tendinitis
Both involve posterior chain tightness; Achilles stiffness contributes to plantar fasciitis
Sever's Disease
Both involve heel pain; plantar fascia attaches near calcaneal apophysis
Shin Splints
Both are overuse injuries with shared biomechanical factors in runners
Diabetes-Related Musculoskeletal Conditions
Diabetes raises the risk of plantar fasciitis and slows fascia and tendon healing
Getting back to it
Physiotherapy for plantar fasciitis & heel spurs, built around the activity you want back.
