
Piriformis Syndrome
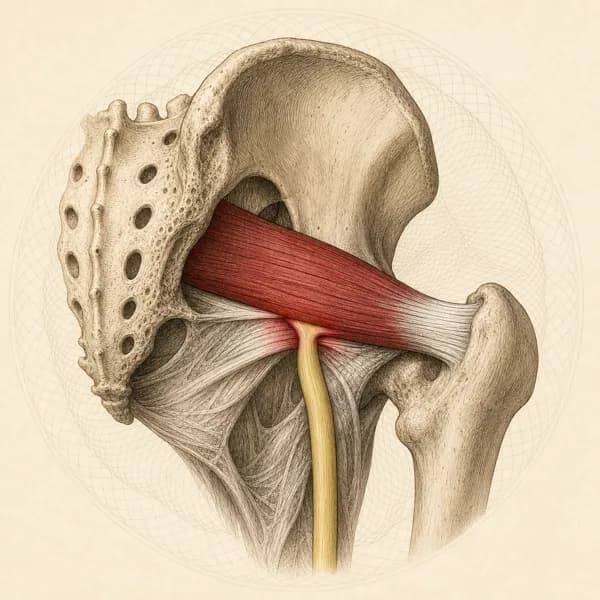
Piriformis syndrome describes irritation of the sciatic nerve associated with the piriformis muscle deep in the buttock. It is one possible form of deep gluteal syndrome, a broader group of nerve problems in this area. Pain may worsen with sitting or travel down the leg, and can resemble symptoms from the back.
Key points
- What usually helps
- Hip strengthening, gentle nerve gliding and changes to how you sit.
- What you can do now
- Empty your back pocket, check your seat. Sit on a firm cushion, legs uncrossed.
- How long it takes
- Many people improve over several weeks; some take longer.
- When to see a doctor first
- Some signs need emergency care. Check the list before you start treatment.
Symptoms
Does this sound like you?
- Deep buttock pain
- Pain that spreads down the leg
- Worse with sitting
- Tenderness in the buttock
- Pain with hip movements
Often alongside it
- Numbness in the leg
- Difficulty sitting on the painful side
- Pain with stairs
- Hip stiffness
- Low back discomfort
- An aching or burning feel
- Often one side only
- Eases with standing or changing position
Deep buttock pain that is worse with sitting. It may feel like sciatica, but without back pain.
Before using this comparison, check when these symptoms need a doctor first.
When to see a doctor first
Go to emergency
New trouble starting to pass urine or feeling it pass, new loss of bladder or bowel control, new numbness around the genitals, back passage, buttocks or inner thighs, new loss of sexual function, or severe or rapidly worsening weakness in both legs
Possible cauda equina syndrome (pressure on the nerves at the base of the spine). Go to emergency now
Sudden unexplained weakness or numbness in an arm or leg, even if it improves
Call 911 now. This can be a stroke. Do not wait for a physiotherapy appointment
Get seen today
Pain that suddenly starts down both legs, or spreads from one leg to both, even without the signs above
Contact a medical clinician today for a same-day assessment
A new foot drop (the foot catches or slaps when you walk), or weakness or numbness in one leg that is getting worse
Possible significant nerve compression. Get medical assessment today
Check with your doctor
Severe, constant pain that does not change with position
Not typical of piriformis syndrome. See your family doctor promptly to look for other causes
Treatment
How it is treated
Main approach. Hip strengthening built up step by step and gentle exercises that help the sciatic nerve glide, paired with changes to how you sit, can help many people with deep buttock (deep gluteal) or piriformis-related pain. The research on any single treatment is limited.
Alongside it. Changing activities and posture reduces what irritates the area, while gentle nerve gliding exercises (neural mobilization) improve how freely the sciatic nerve moves.
Managing it over time. Regular hip strengthening and avoiding long periods of sitting can reduce the chance of piriformis syndrome in people who sit for work and in athletes.
A typical rehabilitation progression
Three phases, from settling symptoms to returning to full activity.
Recovery from piriformis syndrome is usually staged: calm the symptoms first, then rebuild the strength and capacity of the area, then return to your full activities. The phases below show how that can progress.
Phase 1Foundation: Calm the Nerve and the Muscle
The early priority is making the less sensitive and easing the tension in the deep buttock muscles that drives symptoms, while keeping the hip moving. Sitting is the main aggravator, so managing how you sit is part of the exercise plan.
Example exercises
- Sciatic (gentle movements that slide the nerve back and forth), seated or lying on your back, 10 to 15 slow repetitions, stopping before leg symptoms come on
- Lying on your back with one ankle resting on the opposite knee (figure-4), held gently without forcing, 30 to 45 seconds, 2 to 3 times if pain-free
- Clamshells (lying on your side with knees bent, opening the top knee) and side-lying leg lifts (), 2 sets of 10 to 12 per side with a light band
- Slow belly breathing (diaphragmatic breathing) lying on your back with knees bent, and short, frequent walking breaks, 5 to 10 minutes several times a day
- Changes to sitting: a firm wedge cushion, taking weight off the affected side, and standing breaks every 20 to 30 minutes
Possible progression milestones
Symptoms staying at or above the middle of the thigh, sitting for 30 minutes manageable, and tenderness when the deep buttock is pressed down by roughly half.
Phase 2Progressive Loading: Build Hip Strength and Control
Deep buttock and symptoms often come with weakness in the main buttock muscles ( and maximus). The aim here is to share load across the hip muscles so the piriformis stops compensating, and to move the nerve exercises on from sliders to tensioners (gentle movements that put the nerve under light tension).
Example exercises
- Bridge and single-leg bridge (lying on your back, lifting the hips), 3 sets of 8 to 12
- Walking sideways and diagonally with a band around the legs (lateral walks and monster walks), 2 to 3 sets of 10 to 12 steps each direction
- Split squat and step-up variations, 3 sets of 6 to 10 per side
- Sciatic nerve tensioners lying on your back or sitting slumped (slump position), in small ranges, 8 to 10 controlled repetitions
- Hip hinge progressions (bending forward from the hips): kettlebell deadlift, then single-leg Romanian deadlift
Possible progression milestones
Single-leg bridges and step-ups without bringing on buttock or leg symptoms, sitting for an hour with any flare under 3 out of 10, and back to a light walking or cycling program.
Phase 3Return to Function: Load, Run, and Help Stop It Coming Back
The last phase rebuilds what the hips can handle for sport or physically demanding work, and gives you a minimum maintenance plan that keeps the hips loaded. Deep gluteal syndrome tends to come back when this loading drops off, which is why the plan for finishing matters.
Example exercises
- Lifting with a hip hinge under load (trap-bar or standard deadlift), 3 to 4 sets of 3 to 6
- Front squat or split squat with the back foot raised, at working loads
- Return to running with a walk-run plan built up gradually, flat ground first
- Jumping drills for the hips (): small bouncing hops (pogo hops), then sideways bounds, for the demands of your sport
- Hip and trunk maintenance twice a week that you can keep up on your own
Possible progression milestones
Back to full sport and work demands with minimal symptoms, managing flares on your own, and a written maintenance plan you will actually do.
What you can do now
- Empty your back pocket, check your seat. A thick wallet in the back pocket or a low, scooped car seat is a common contributor, especially if you drive a lot. Changing what you sit on can bring early relief and makes the exercises that follow easier.
- Sit on a firm cushion, legs uncrossed. Sitting squeezes the deep buttock space, and sitting with the hip bent, drawn across the body and turned inward also stretches the piriformis. A firm cushion that takes weight off the painful side, and not sitting cross-legged, both reduce that pressure.
- Stand or walk every 20 to 30 minutes. During a flare, regular standing or walking breaks give the area relief from sitting. How long you can sit before it bothers you is a good guide to progress, and it tends to improve over weeks rather than days.
- Keep stretches gentle and short. Hard stretching often irritates a nerve that is already sensitive. Gentle, brief stretches that do not bring on leg symptoms, combined with nerve gliding and strengthening, tend to help more than repeatedly pulling the knee to the opposite shoulder.Stop a stretch if it brings on symptoms down the leg.
- Run short and flat, build back gradually. Short, flat, gentle-paced runs are usually tolerated before long runs or hills, as long as running does not keep bringing on or worsening leg symptoms. Long sitting before or after a run, hard hill work and sudden jumps in distance tend to flare it.Leg weakness or numbness that is getting worse needs medical assessment today, as the warning signs on this page say.
What I use in clinic
- Hip Strengthening. Builds up weak hip muscles that contribute to overuse.
- Soft Tissue Work. Hands-on soft tissue work, alongside the gentle stretching above, reduces muscle tension and nerve irritation.
Recovery
How long it takes
Many people improve over several weeks once aggravating loads are changed, but research on recovery times is limited and some cases take longer.
It can become long-lasting if the underlying factors are not addressed.
What changes the timeline
- How long you have had symptoms
- What is contributing to it
- How well activities are adjusted
- Hip strength
How I track it. I track how much the pain gets in the way of the tasks that matter to you, how well you move when I test those tasks in clinic, and how confident you feel in daily activities
Similar conditions
Conditions that can feel similar
- Lumbar Radiculopathy (Disc or Foraminal)
- Back pain along with leg pain, pain following the strip of skin supplied by one nerve root (a dermatome), pain brought on by nerve tension tests (straight leg raise or slump), and sometimes weakness in the muscles that nerve supplies or a reflex change. When a disc is the cause, it is worse with bending the lower back forward and with sitting, rather than with direct pressure on the buttock.
- Sacroiliac Joint Dysfunction
- Pain the person can often point to with one finger, just below the belt line over the bony bump at the back of the pelvis (the PSIS). A group of tests that stress the SI joint brings it on (distraction, thigh thrust, compression, Gaenslen and sacral thrust tests). The pain rarely spreads below the knee and is not typically deep in the middle of the buttock.
- Proximal Hamstring Tendinopathy
- Pain over the sitting bone (ischial tuberosity), worse with sitting on firm surfaces, bending the hip deeply, and lunging. Loading the hamstring against resistance and pressing where it attaches bring it on, rather than pressure deep in the buttock.
- Hip Joint Pathology (FAI or Labral Tear)
- Pain is mainly at the front of the groin or the side of the hip, not the back of the buttock. Turning the hip inward is reduced and painful, and the FADIR test (bending, crossing and turning the hip inward) brings on pain. Walking and deep squatting tend to aggravate it, rather than sitting for a long time in one position.
- Ischiofemoral Impingement
- Deep buttock pain linked to walking with long strides and to the leg moving fully backward (end-range hip extension). MRI shows a narrowed gap between the thigh bone and the sitting bone (the lesser trochanter and ischium), with swelling in a small deep hip muscle (quadratus femoris oedema). Pressing on the piriformis is less likely to bring it on.
- Gluteal Tendinopathy (GTPS)
- Pain on the outer hip over the bony point (the greater trochanter), worse lying on that side, standing on one leg, and crossing the legs. Pain at the back of the buttock is not the main feature.
Commonly confused with
Side-by-side comparisons for patterns that often get mistaken for piriformis syndrome.
- Compare side by side
Is this piriformis syndrome or sciatica?
How I separate piriformis syndrome from sciatica by pattern, tests, and exam findings.
- Compare side by side
Is this piriformis syndrome or hamstring tendinopathy?
How I separate piriformis syndrome from hamstring tendinopathy by pattern, tests, and exam findings.
Questions
What patients ask me most
Is piriformis syndrome the same as sciatica?
Not quite. Sciatica usually means nerve pain that starts at the spine, typically from a disc pressing on a nerve root. What used to be called piriformis syndrome is now better understood as deep gluteal syndrome: irritation of the sciatic nerve as it travels through the deep buttock, by the piriformis or by other structures in that space (Martin et al., J Hip Preserv Surg 2015). The symptoms can feel like sciatica, but the cause and the treatment differ.
How do I know if it is my piriformis and not a disc?
The typical pattern with deep gluteal or piriformis pain is deep buttock tenderness when the area is pressed, worse with long sitting, and often without much low back pain. A disc pressing on a nerve root more commonly causes back pain plus leg pain, is brought on by nerve tension tests (straight leg raise or slump), and may include weakness in the muscles that nerve supplies or a reflex change, although leg pain from a nerve root can also occur without much back pain. The history and examination can suggest whether symptoms are more likely to come from the back, the deep buttock or another source. Sometimes the pattern stays uncertain and needs reassessment or medical investigation. Imaging is kept for cases with warning signs (red flags) or when non-surgical care has not worked.
How long does piriformis syndrome take to settle?
Many people improve over several weeks with a combination of load management, graded hip strengthening and sensible changes to sitting, but recovery times vary and the research on them is limited. Long-standing cases, or cases where fitness has dropped a lot, can take longer, which is one reason addressing it early helps.
Should I stretch my piriformis aggressively?
No. Hard stretching to the limit often irritates a nerve that is already sensitive and makes things worse. Gentle, brief stretches that do not bring on leg symptoms, combined with nerve gliding (gentle movements that slide the nerve) and strengthening of the muscles that turn the hip outward and the glutes, tend to help more than repeatedly pulling the knee to the opposite shoulder.
Why does sitting make it so much worse?
Sitting squeezes the deep buttock space between the sitting bone and the seat, and stretches the piriformis when the hip is bent, drawn across the body and turned inward, which is how many people sit. For sudden flares I recommend standing or walking breaks every 20 to 30 minutes, avoiding cross-legged sitting, and using a firm cushion that takes weight off the painful side.
Can I run with piriformis syndrome?
Often yes, with changes, provided running does not consistently bring on or worsen leg symptoms. Short, flat, gentle-paced runs are usually tolerated before long runs or hills. What tends to flare it is long sitting before or after a run, hard hill work, and sudden increases in distance. A gradual walk-run return usually works better than pushing through.
Do I need a cortisone injection or surgery?
Surgery for deep gluteal syndrome is uncommon and kept for a trapped nerve clearly shown on imaging that has not improved with sustained non-surgical care. Piriformis injections guided by imaging (local anaesthetic, with or without corticosteroid) are sometimes used when symptoms are severe or the diagnosis is unclear, but many people improve with non-surgical care without them.
Do I need an MRI?
Not for most cases. The diagnosis is made from your history and examination: the lower back examines normally, and specific tests that load the deep buttock bring on the pain. MRI is kept for warning signs (red flags), when non-surgical care is not progressing, or when it is still unclear what else it could be. Ultrasound with an experienced operator sometimes helps when planning a targeted injection.
What actually compresses the nerve if it is not always the piriformis?
The deep buttock space has several possible culprits: the piriformis in some people whose anatomy differs, fibrous bands, a group of small deep hip muscles (the gemelli and obturator internus), the top of the hamstring, and blood vessels. Hernando et al. (Skeletal Radiology 2015) mapped this thoroughly. Part of the assessment is working out which structure is most likely in your case so the loading plan targets the right one.
The science
The Science of Piriformis Syndrome
syndrome, as traditionally understood, involves irritation of the by the piriformis muscle deep in the buttock. However, this represents an outdated understanding of buttock and leg pain. For decades, "Piriformis Syndrome" was used as a catch-all term for buttock pain with leg symptoms. The piriformis muscle can be involved, but the picture is now understood to be more complex.
The more accurate and comprehensive term is "Deep Gluteal Syndrome" (DGS). This describes the entrapment or irritation of the sciatic nerve not just by the piriformis, but by a number of other structures in the deep buttock space, such as fibrous bands, the gemelli-obturator internus muscle group, or other anatomical variations. The deep gluteal space is a busy anatomical neighborhood where the sciatic nerve must navigate a narrow tunnel surrounded by several deep hip rotator muscles.
This diagnostic evolution is important because treatment approaches differ significantly. Rather than focusing solely on the piriformis muscle, effective management requires a comprehensive assessment of the entire deep gluteal space, movement patterns, and the function of all the muscles that could contribute to nerve compression. The concept of piriformis syndrome as an isolated condition is being replaced by the broader, more accurate understanding of Deep Gluteal Syndrome.
Contributing factors
The deep gluteal space represents an anatomically constrained tunnel through which the must pass. This space is bounded by the greater sciatic notch superiorly, the inferiorly, the hip joint capsule anteriorly, and the gluteus maximus muscle posteriorly. Within this relatively small space, the sciatic nerve travels alongside or through several deep hip rotator muscles including the , superior and inferior gemelli, obturator internus, and quadratus femoris. Any factor that reduces the available space or increases muscle volume within this tunnel can compress the nerve.
The of what was traditionally called "piriformis syndrome" mirror those of Deep Gluteal Syndrome, with the piriformis muscle being one of several potential compressive structures in the deep gluteal space. The piriformis runs from the sacrum to the and functions primarily as a hip external rotator when the hip is in neutral position. Understanding its anatomical relationship to the sciatic nerve is crucial: in approximately 85% of individuals, the sciatic nerve exits the pelvis beneath the piriformis muscle, while in about 15%, the nerve may pierce through the muscle or exit above it, anatomical variations that predispose certain individuals to nerve compression.
Hip positioning significantly influences the mechanical load on the piriformis and the available space for the sciatic nerve. When your hip moves into flexion combined with and internal rotation, positions common during sitting, particularly in low chairs or car seats, the piriformis muscle stretches and can compress the sciatic nerve against the bony boundaries of the deep gluteal space. This combined hip position reduces the available space for the sciatic nerve, increasing compression forces on the nerve. This explains why prolonged sitting, especially in vehicles or on low furniture, frequently triggers or exacerbates symptoms.
The piriformis muscle experiences variable mechanical demands based on hip position. When your hip is in neutral or slight extension, the piriformis functions primarily as an external rotator, with relatively modest force production. However, when the hip flexes beyond 60 degrees, the piriformis muscle's line of action shifts, transforming it into a rather than an external rotator. During active contraction in hip flexion positions, the piriformis can enlarge, reducing the space available for the sciatic nerve within the deep gluteal tunnel.
Some athletes whose sports demand repeated hip rotation, such as soccer, ballet, figure skating and hockey, may develop larger deep hip rotators over time, though how much this contributes to nerve irritation varies between individuals and is not well established.
Several structures in the deep buttock can irritate the sciatic nerve, and the precise source is not always clear. One common idea is that when the larger gluteal muscles are weak, the deep rotators work harder and become irritable; that is plausible, but it is not established as the cause in any one person. Hip strength, activity changes and sitting habits may all affect symptoms, so they guide the exercise plan.
Sitting mechanics create sustained compression similar to other deep gluteal space conditions. When you sit, body weight compresses the soft tissues of the buttock, including the piriformis muscle and sciatic nerve, between the ischial tuberosity and the seat surface. Sitting on hard surfaces keeps pressure on the deep gluteal tissues and the nerve, which is one likely reason symptoms often worsen with desk work, driving, or other long periods of sitting.
The relationship between pelvic positioning and piriformis length significantly influences symptoms. When your pelvis tilts posteriorly, as commonly occurs with slouched sitting postures, the origin of the piriformis on the sacrum moves away from its insertion on the greater trochanter, effectively lengthening and tensioning the muscle. This increased muscle length can compress the sciatic nerve against surrounding structures. Conversely, anterior pelvic tilt shortens the piriformis but may increase compression through other mechanisms. Pelvic tilt alters piriformis length and tension, highlighting how postural factors influence the mechanical environment of the sciatic nerve.
Research
What the studies show
How well examination tests detect a trapped sciatic nerve in the buttock (Martin et al., 2014)
In patients assessed before keyhole (endoscopic) surgery, combining two examination tests (the active piriformis test and the seated piriformis stretch test) picked up 91 percent of people whose sciatic nerve was trapped in the deep buttock, and gave a negative result in 80 percent of those whose nerve was not.
Supports making the diagnosis from the physical examination, without needing imaging for the first assessment and treatment plan.
Martin HD, Kivlan BR, Palmer IJ, et al. (2014). Diagnostic accuracy of clinical tests for sciatic nerve entrapment in the gluteal region. Knee Surg Sports Traumatol Arthrosc. PMID: 24217716.
Review of non-surgical and surgical treatments for deep gluteal syndrome (Hopayian et al., 2023)
This 2023 review of the research found the overall quality of the evidence was low, and no single non-surgical treatment could be recommended over another. The authors advised following general guidance for back pain and sciatica, with physiotherapy as the first treatment and surgery kept for long-standing cases.
Supports physiotherapy-led, non-surgical care as the first approach, with realistic expectations given how limited the evidence is.
Hopayian K, Mirzaei M, Shamsi M, et al. (2023). A systematic review of conservative and surgical treatments for deep gluteal syndrome. J Bodyw Mov Ther. PMID: 37949567.
Related Conditions
Conditions I commonly see alongside, or confused with, this one.
Getting back to it
Physiotherapy for piriformis syndrome, built around the activity you want back.
