
Wrist Sprains & Strains
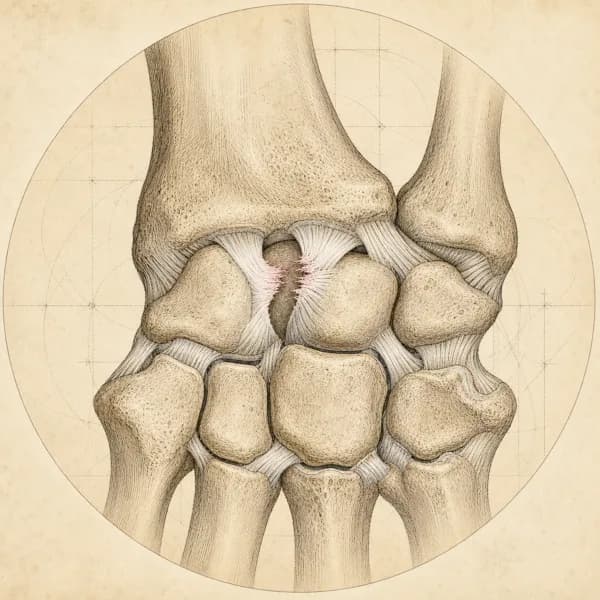
A wrist sprain is an injury to the ligaments that hold the small wrist bones together, often from a fall on an outstretched hand. It causes pain, swelling and a weaker grip, and some sprains leave the wrist feeling unstable. Pain at the base of the thumb after a fall should be assessed promptly, to rule out a scaphoid fracture.
Key points
- What usually helps
- Once a fracture is ruled out, a short spell in a brace, then early, protected movement.
- What you can do now
- Rule out a fracture first. Use the brace for the tasks that hurt.
- How long it takes
- Many sprains improve over several weeks; full recovery can take a few months.
- When to see a doctor first
- Some signs need emergency care. Check the list before you start treatment.
Symptoms
Does this sound like you?
- Pain in a particular part of the wrist, depending on which ligaments are hurt
- Swelling and tenderness over the injured ligaments
- Pain that gets worse with certain movements or ways of loading the wrist
- Sensation of instability or 'giving way' during gripping activities
- Stiffness, and less movement in certain directions
Often alongside it
- Weakness with gripping or pinching activities
- Clicking, popping, or clunking sensations during movement
- Pain with weight-bearing on the hands (push-ups, yoga poses)
- Difficulty with rotational activities (turning doorknobs, keys)
- Using the forearm or shoulder differently to protect the wrist
Two patterns are common: a sudden injury from a fall or sport, where people remember the exact moment, and a gradual onset from repeated stress. People frequently describe pain with specific activities such as push-ups, or difficulty gripping objects firmly.Book an assessment for wrist sprains & strains
When to see a doctor first
Go to emergency
A change in the shape of the wrist, severe swelling, or being unable to move the wrist after a fall
Go to emergency now to rule out a fracture or dislocation
Signs of infection including fever, red streaking, or severe swelling
Go to emergency now. This can be a joint infection
Get seen today
Tenderness in the hollow at the base of the thumb (the snuffbox), or pain when the thumb is pushed in toward the wrist, after a fall on an outstretched hand
Support the wrist in a splint, avoid lifting or putting weight through it, and get a prompt medical assessment and X-ray, the same day or next day, to rule out a scaphoid fracture before it is treated as a sprain. A normal first X-ray may need follow-up imaging
Numbness or tingling in the fingers that is getting worse, or fingers that turn pale or cold
Same-day medical assessment
Check with your doctor
No improvement after 6-8 weeks of appropriate conservative treatment
I refer you to your family doctor for imaging and, if needed, a hand surgeon's opinion
Treatment
How it is treated
Main approach. Once a fracture and significant ligament instability have been ruled out, a short spell of bracing followed by early protected movement can help many stable wrist sprains settle.
Alongside it. Strengthening and wrist control exercises can help restore grip and confidence and may lower the chance of the wrist giving way.
Managing it over time. Keeping up wrist and grip strength, and wrist guards for sports like snowboarding, may lower the risk of another sprain.
A typical rehabilitation progression
Three phases, from settling symptoms to returning to full activity.
Recovery from wrist sprains & strains is usually staged: calm the symptoms first, then rebuild the strength and capacity of the area, then return to your full activities. The phases below show how that can progress.
Phase 1Protect and settle (Weeks 0 to 3)
A new (acute) ligament sprain needs a short window to calm down. The point here is controlling pain, protecting the injured ligament from the movement that aggravates it, and keeping the nearby joints moving so the hand does not stiffen. Everything in this phase stays below the point where it hurts.
Example exercises
- A removable wrist brace during aggravating tasks and for sport, not worn all day and night unless symptoms are severe
- Moving the fingers, thumb, elbow and shoulder through their pain-free range yourself, several times per day
- Gentle pain-free wrist circles and turning the palm down and up ( and supination), 10 slow repetitions 2 to 3 times daily
- Ice over the painful area 10 to 15 minutes after aggravating activity in the first few days if it helps
- Deliberately cutting back on push-ups, heavy gripping and taking weight through the hand with the wrist bent back
Possible progression milestones
Pain at rest minimal, swelling settling, pain-free wrist movement returning, and no sharp catching or clunking with day-to-day tasks for at least a few days before increasing load.
Phase 2Controlled strengthening and movement (Weeks 3 to 8)
Once the early phase is over, the job is to rebuild the muscles that steady the wrist, particularly those supporting the joint between the scaphoid and lunate bones (scapholunate) and the joint between the two forearm bones at the wrist (distal radioulnar joint). A short, controlled dart-throwing arc (the path the wrist takes when throwing a dart) can be part of this if it suits the diagnosed ligament injury, kept to the range a clinician has set, because an injured may separate more at the ends of the movement. Grip strength gets its own focused attention.
Example exercises
- A short dart-throwing arc through the middle of the range, chosen by your clinician, at first without resistance, if it suits the diagnosed ligament injury, 3 sets of 10
- Holds without moving () for bending the wrist forward and back, progressing to slow lifting and lowering ( and ) with a 1 to 2 kg dumbbell, 3 sets of 10 to 15
- Turning the palm down and up (pronation and supination) with a light hammer or dumbbell, 3 sets of 10, through a pain-free range
- Grip work with soft putty or a stress ball, progressing to a hand trainer, 3 sets of 10 at less than full effort
- Wrist control work (): the hand resting on a small ball without leaning on it, rocking with control in safe directions, 2 to 3 minutes at a time
Possible progression milestones
Full pain-free wrist movement, grip strength recovering toward the uninjured side from one test to the next, no catching or clunking when moving under load, and the wrist tolerating light weight through the hand on a tabletop without a flare.
Phase 3Return to weight-bearing and sport (Weeks 8+)
Now the wrist has to cope with real demands: push-ups, carrying weights, gripping when tired, and the forces of your sport. The goal is full loading without symptoms and with confidence in the joint. Anyone returning to contact sport, or a sport with a high risk of falls, also needs a plan for how to fall.
Example exercises
- Graded weight-bearing progression: wall push-ups, tabletop push-ups, floor push-ups on fists or handles, then on flat palms
- Carrying gradually heavier dumbbells (farmer walks) for grip endurance and a steady wrist under load
- Drills for your sport: racquet swings, stickwork, throwing, climbing holds, at less than full effort first
- Reaction work (perturbation training): tossing and catching a weighted ball, and taking weight through the hand on an unsteady surface, to rebuild the wrist's automatic steadiness
- Practising how to fall, for contact sports or sports with a high fall risk, taking the force through a bent elbow rather than a locked, bent-back wrist
Possible progression milestones
Possible milestones, adapted to the person rather than treated as fixed cut-offs: full training or full work demands sustained without a flare, grip strength close to the uninjured side, confident weight-bearing through the palm, and no recurrence of catching, clunking, or giving-way.
What you can do now
- Rule out a fracture first. After a fall on an outstretched hand, tenderness in the hollow at the base of the thumb (the snuffbox), or pain when the thumb is pushed in toward the wrist, needs a prompt medical assessment and X-ray, the same day or next day, before it is treated as a sprain. Until then, support the wrist in a splint and avoid lifting or putting weight through it.A normal first X-ray may need follow-up imaging if that pain continues. Pain that is not steadily improving after a week also needs a medical review.
- Use the brace for the tasks that hurt. Once a fracture and significant ligament instability have been ruled out, a removable brace for one to three weeks protects the sprained ligament while pain and swelling settle. Wear it during aggravating tasks and sport rather than all day and night, unless symptoms are severe.A significant ligament tear may need longer protection, set by a hand surgeon. Otherwise, wearing it for longer than the ligament needs tends to stiffen the wrist and slow your return to sport.
- Keep the hand and arm moving. Move the fingers, thumb, elbow and shoulder through their pain-free range several times a day, and add gentle wrist circles and palm up and down turns, 10 slow repetitions 2 to 3 times a day. This keeps the hand from stiffening while the ligament settles.Keep every movement below the point where it hurts in these first weeks.
- Keep weight off the bent-back wrist. Taking weight through the hand with the wrist bent back is the loading pattern most sprains dislike early on, so cut back on push-ups, yoga poses on the hands and heavy gripping for now. Forcing through sharp pain tends to drag the recovery out.A painful click or clunk with a particular movement, or a wrist that is still catching or will not take weight through the palm at about eight weeks, needs reassessment rather than more loading.
- Keep the dart-throw arc within your set range. If a clinician has given you a short movement through the middle of the range, such as the dart thrower's arc (the path the wrist takes when throwing a dart), it can help keep the wrist moving comfortably while the ligament heals.After an injury to the ligament between the scaphoid and lunate bones (scapholunate), avoid the ends of the arc. Stop if the pain increases significantly.
What I use in clinic
- Short-Term Bracing. A brace for one to three weeks protects a sprained ligament while pain and swelling settle. Longer immobilisation is only used for specific ligament tears, under a surgeon's guidance.
- Dart-throwing motion. After an injury to the ligament between the scaphoid and lunate bones (scapholunate), studies suggest limiting the ends of the arc, because a torn or repaired ligament may separate more there; the evidence is preliminary (Bergner et al., 2020).
- Targeted Muscle Strengthening. Strengthening the forearm muscles thought to steady the joint between the scaphoid and lunate bones (the scapholunate joint) may help stability, though the evidence is still limited.
- Wrist control training (proprioception). Exercises that train the wrist's sense of position and control improve its stability during movement and may help prevent re-injury.
- TFCC rehabilitation. Graded strength and control work for the muscles that rotate the forearm may help a stable tear of the TFCC (the cartilage and ligament cushion on the little-finger side of the wrist) settle.
Recovery
How long it takes
Many acute sprains improve over several weeks with appropriate treatment, and complete recovery can take a few months depending on severity. Significant ligament tears follow a timeline set with a hand surgeon.
Partial ligament injuries often heal well with non-surgical treatment. A complete tear of a ligament may leave the wrist unstable in the long term if it is not properly managed.
What changes the timeline
- How badly the ligament is damaged affects healing time
- Getting a fracture ruled out early matters
- Keeping up the exercise program affects recovery
- Injury to several structures at once may make recovery longer
- Age and general health affect how well you heal
How I track it. I monitor your pain during specific activities, gains in grip strength and wrist movement, and how well you manage daily tasks that need a steady wrist
Similar conditions
Conditions that can feel similar
- Scaphoid Fracture
- A fall on an outstretched hand with sharp pain in the small hollow at the base of the thumb (the anatomical snuffbox), tenderness over the scaphoid's bump on the palm side of the wrist (the scaphoid tubercle), pain when the thumb is pushed in toward the wrist, and swelling in the snuffbox. These tests pick up most fractures but are also positive in many wrists that are not broken (sensitive but not specific). The threshold for imaging should stay low, because a missed scaphoid fracture risks the bone not healing (non-union) or losing its blood supply (avascular necrosis).
- Distal Radius Fracture
- Obvious deformity, marked swelling, and being unable to take weight through the wrist straight after a fall. Pain tends to sit more centrally, over the end of the forearm bone (the distal radius), rather than over one group of ligaments. An X-ray confirms the diagnosis.
- Scapholunate Ligament Injury
- Pain on the back of the wrist toward the thumb side, a painful click or clunk when the wrist bends from side to side, tenderness just past the small bony bump on the back of the wrist, toward the fingers (Lister's tubercle), and a painful clunk when the clinician presses on the scaphoid while moving the wrist (Watson scaphoid shift test). How reliably the Watson test picks up the injury varies widely in studies, so a hard fall on an outstretched hand with pain on the back of the wrist still warrants imaging review even when the test is unclear.
- Triangular Fibrocartilage Complex (TFCC) Injury
- Pain on the little-finger side of the wrist, pain when turning the forearm under load (opening jars, turning a door handle), tenderness in the small soft spot between the bony bump on the little-finger side of the wrist and the tendon beside it (the fovea), and pain when the wrist is pressed and turned toward the little-finger side (ulnar grind test). Sander and colleagues' work supports a trial of non-surgical care for stable TFCC tears before considering keyhole surgery (arthroscopy).
- De Quervain's Tenosynovitis
- Sharp pain over the tendon tunnel on the thumb side of the wrist (the first dorsal compartment), rather than spread-out wrist pain after an injury. A thumb-and-wrist stretch test is painful (Finkelstein's test), and symptoms come from repeated thumb loading rather than one injury. It often occurs alongside a wrist sprain in new parents who have also had a fall.
- Extensor Carpi Ulnaris (ECU) Subluxation or Tendinopathy
- Pain on the little-finger side of the wrist, with a snap you can feel as the forearm turns palm down and palm up under load, and tenderness along the groove where the ECU tendon runs. With the palm up, lifting the back of the hand and bending it toward the little finger against resistance brings on the pain. Commonly seen in racquet sports and after the forearm is forcibly twisted palm up.
Questions
What patients ask me most
I fell on my hand last week, how do I know if it is broken versus sprained?
You probably cannot tell from the outside, and that is why a fall on an outstretched hand with persistent wrist pain deserves an X-ray. A scaphoid fracture in particular can look and feel like a bad sprain, and Rhemrev and colleagues' 2011 review in the International Journal of Emergency Medicine is clear that the bedside tests pick up most fractures but are also positive in many wrists that are not broken (sensitive but not specific). If there is tenderness in the small hollow at the base of the thumb (the anatomical snuffbox) or pain when the thumb is pushed in toward the wrist, the wrist should be supported in a splint, kept from lifting and weight-bearing, and assessed promptly for an X-ray, the same day or next day, before it is treated as a sprain. I refer you for that through your family doctor or urgent care. An early X-ray can be normal, so continued suspicion needs follow-up imaging and protection. Pain that is not steadily improving after a week also needs a medical review.
Does a wrist sprain always need a brace?
A short course of bracing, usually one to three weeks, can help a stable sprain settle once a fracture and significant ligament instability have been ruled out. A significant scapholunate or TFCC tear may need longer protection, set by a hand surgeon. The point is to protect the ligament while pain and swelling come down, not to immobilise you for months. For TFCC problems on the little-finger side, and mild scapholunate irritation, I tend to use a brace for pain control and protect it during sport, then transition into progressive loading quickly. Immobilisation beyond what the ligament needs tends to stiffen the wrist and slow the return to sport.
Why does my wrist click or clunk even after the pain has settled?
Clicking on its own, without pain and without feeling unstable, is usually not a problem. A click that comes with a clear painful moment during a specific movement, particularly bending the wrist side to side or turning the forearm under load, is more interesting. In those cases I am thinking about the ligament between the scaphoid and lunate bones, or the TFCC, and I will often refer you through your family doctor for imaging or an orthopaedic opinion rather than keep loading blind.
Can I still lift or do push-ups with a wrist sprain?
Not while it is hot. Taking weight through the wrist while it is bent back is the one loading pattern most sprains really dislike early on. I will take you through pain-free loading alternatives first, things like dumbbell work with a neutral grip, push-up variations on fists or on handles, and then rebuild full weight-bearing through the palm once the tissue can tolerate it. Forcing through the sharp pain buys nothing and tends to drag the recovery out.
What is the dart throwing motion and why does everyone keep mentioning it?
It is the path your wrist takes when you throw a dart, from bent back toward the thumb side to bent forward toward the little-finger side. In an intact wrist, that arc puts less strain on the ligament joining the scaphoid and lunate bones (the scapholunate interosseous ligament) than bending straight forward or back. A short, controlled dart-throwing arc can sometimes help maintain movement. It is not stress-free: a torn or repaired scapholunate ligament may separate more at the ends of the movement (Bergner et al., Journal of Hand Therapy 2020). The safe range, brace and timing need to be set for the specific injury, and the research on it is still preliminary.
How long should a wrist sprain take to heal?
A mild ligament strain usually quietens down over two to four weeks, with return to full loading by six to eight. A clear partial tear of the scapholunate or a TFCC lesion runs longer, often two to three months of graded rehab, and a small subset end up at imaging or a hand surgeon if symptoms plateau. If you are at the eight-week mark and your wrist is still catching, still sore with grip, or still refusing to take weight through the palm, it is time to reassess rather than push.
When should I see a surgeon?
Any deformity, inability to use the hand, or severe pain after a fall should be seen that day. Beyond that, I refer when clinical signs point to a significant scapholunate or TFCC tear with instability of the joint between the two forearm bones at the wrist (the distal radioulnar joint), when pain has not shifted after a proper six to eight week course of rehab, or when imaging findings do not match what the clinical exam shows. Most wrist sprains do not need a surgeon, but a small number clearly do.
The science
The Science of Wrist Sprains & Strains
Wrist sprains involve damage to the ligaments that connect the bones of your wrist, most commonly affecting the complex or the (TFCC). These structures are crucial for maintaining proper carpal bone alignment and allowing coordinated wrist movement.
The scapholunate interosseous ligament is particularly vulnerable to injury during falls on an outstretched hand or rotational movements under load. When this ligament is damaged, it can lead to abnormal movement patterns between the scaphoid and lunate bones, potentially causing long-term if not properly managed.
TFCC injuries affect the complex of ligaments and cartilage on the pinky side of your wrist. This structure acts as a shock absorber and stabilizer for the distal radioulnar joint, allowing smooth rotation of your forearm while maintaining wrist stability.
The healing potential of wrist ligaments varies significantly depending on their blood supply. Some areas have excellent healing capacity, while others, particularly the central portions of certain ligaments, have limited blood flow and may heal slowly or incompletely without proper treatment.
Contributing factors
Your wrist functions as a complex joint system where eight small carpal bones must work together to provide both stability and mobility. The acts as a critical link that maintains the relationship between the scaphoid and lunate during all wrist movements.
During normal wrist extension, the scaphoid tends to flex while the lunate extends, creating a complex motion that requires intact ligamentous restraints. When the scapholunate ligament is injured, this coordinated movement is disrupted, leading to altered mechanics and potential for progressive .
The dart throwing motion (DTM) represents a path of movement where the wrist moves from radial extension to ulnar flexion, following the natural alignment of the carpal bones. In an intact wrist this path places less stress on the scapholunate interval, and a short, controlled arc of it is often used in rehabilitation. It is not stress-free after an injury: in a torn or repaired scapholunate ligament, the gap between the two bones can widen toward the ends of the movement, so the safe range is set for the specific injury (Bergner et al., Journal of Hand Therapy 2020).
injuries affect the of forearm rotation and ulnar-sided wrist stability. The complex must maintain proper relationship between the radius, ulna, and carpal bones during activities that involve gripping combined with rotation, such as using a screwdriver or opening jars.
Research
What the studies show
In a small study, TFCC tears did about as well without surgery as with keyhole surgery when the forearm joint was stable
A small study of 33 people with a tear of the TFCC (the cartilage and ligament cushion on the little-finger side of the wrist) and a stable joint between the two forearm bones at the wrist compared 16 treated without surgery with 17 who had keyhole surgery to clean up the tear (arthroscopic debridement), followed for an average of 22 months. Pain, movement, grip strength (88% of the other side in the non-surgical group) and function scores were similar between the groups.
Supports trying rehab first for a stable TFCC tear. The study was small, so I watch for signs that a surgical opinion is needed.
Sander AL, Sommer K, Kaiser AK, et al. Outcome of conservative treatment for triangular fibrocartilage complex lesions with stable distal radioulnar joint. Eur J Trauma Emerg Surg. 2021;47(5):1621-1625. PMID: 32036393.
Related Conditions
Conditions I commonly see alongside, or confused with, this one.
Carpal Tunnel Syndrome
Wrist trauma can lead to swelling and median nerve compression
De Quervain's Tenosynovitis
Wrist injuries can predispose to De Quervains tendinopathy
Repetitive Strain Injuries
Acute wrist injury can lead to chronic overuse patterns
Tennis Elbow
Wrist dysfunction can alter forearm mechanics contributing to elbow problems
Golfer's Elbow
Getting back to it
Physiotherapy for wrist sprains & strains, built around the activity you want back.
